Related Experiment Video
Updated: Jul 18, 2026
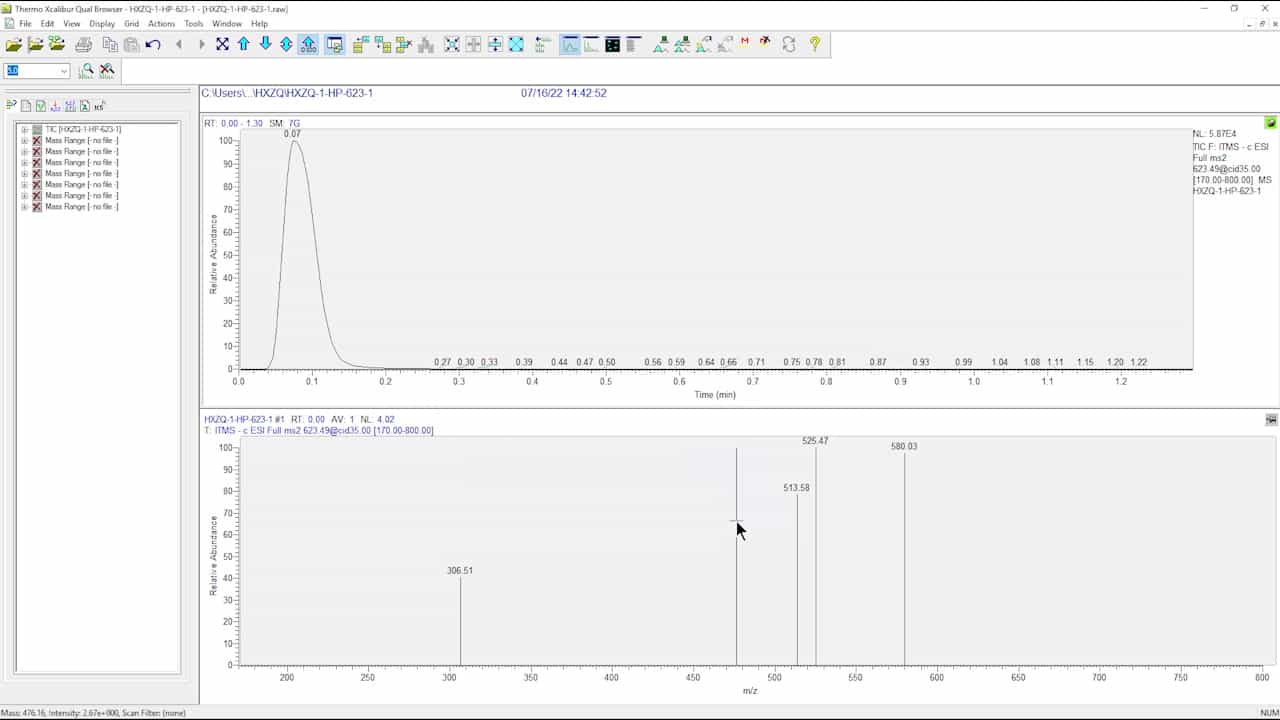

Technical Approach for Structural Analysis of an Unknown Compound in Huoxiang Zhengqi Oral Liquid based on Linear Ion Trap Mass Spectrometry
Published on: April 3, 2026
Oral anticoagulant therapy in patients with coronary artery disease: a meta-analysis
1Program of Preventive Cardiology and Therapeutics, Hamilton Civic Hospitals Research Centre, McMaster University, Ontario, Canada. anands@fhs.mcmaster.ca

Context:
Despite years of use in coronary artery disease (CAD) and several studies of its effectiveness, the role of oral anticoagulants (OAs) remains controversial.
Objective:
To determine the effects of long-term OA therapy, stratified by the intensities of anticoagulation and aspirin therapy, on outcomes in patients with CAD.
Data Sources:
Studies were identified by MEDLINE, EMBASE, and CURRENT CONTENTS searches (1960-July 1999) and by reviewing reference lists and inquiring with experts and pharmaceutical companies.
Study Selection:
Studies were included if they were published between 1960 and July 1999, were randomized, had recruited patients with CAD, who had used OA therapy for at least 3 months. Of 43 articles identified, 30 articles (31 trials) were analyzed.
Data Extraction:
Information on type, duration, and method of monitoring OA therapy, as well as rates of death, myocardial infarction (MI), thromboembolic complications, stroke, and bleeding were abstracted by 2 independent observers.
Data Synthesis:
With high-intensity (international normalized ratio [INR], 2.8-4.8) OAs vs control (16 trials, 10056 patients), clear reductions in mortality (odds reduction [ORed], 22%; 95% confidence interval [CI], 13%-31%), MIs (ORed, 42%; 95% CI, 34%-48%), and thromboembolic complications including stroke (ORed, 63%; 95% CI, 53-71%) were observed, but were associated with a 6.0-fold (95% CI, 4.4- to 8.2-fold) increase in major bleeding. For moderate OAs (INR, 2-3) vs control (4 trials, 1365 patients) the ORed for death was 18% (95% CI, -6% to 37%); for MI, 52% (95% CI, 37%-64%); and for stroke, 53% (95% CI, 19%-73%), but it increased bleeding by 7.7-fold (95% CI, 3.3- to 18-fold). For moderate- to high-intensity OAs (INR, > or =2) vs aspirin (7 trials, 3457 patients), no reduction in death, MI, or stroke was observed, and it was associated with a 2.4-fold (95% CI, 1.6- to 3.6-fold) increase in major bleeding. For moderate- to high-intensity OAs and aspirin vs aspirin alone (3 trials, 480 patients), the ORed for death, MI, or stroke was 56% (95% CI, 17%-77%) and major bleeding increased by 1.9-fold (0.6- to 6.0-fold). For low-intensity OAs (INR, <2.0) and aspirin vs aspirin alone (3 trials, 8435 patients), no significant reduction in death, MI, or stroke was observed, and major bleeding increased by 1.3-fold (95% CI, 1.0- to 1.8-fold).
Conclusions:
Among patients with CAD, high-intensity and moderate-intensity OA are effective in reducing MI and stroke but increase the risk of bleeding. In the presence of aspirin, low-intensity OA does not appear to be superior to aspirin alone, while moderate- to high-intensity OA and aspirin vs aspirin alone appears promising and the bleeding risk is modest, but this requires confirmation from ongoing trials.
Related Concept Videos
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 01:23
Treatment for Pulmonary Arterial Hypertension: Prostacyclin Receptor Agonists
These agonists bind to the IPR receptor situated on the plasma membrane of the pulmonary artery smooth muscle cells. This binding triggers a cascade of reactions known as the GS-AC-cAMP-PKA pathway. This pathway results in the relaxation of smooth muscle...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:26
Angina IV: Management
 01:26
Atherosclerosis III: Management