Related Experiment Video
Updated: Oct 18, 2026

A Protocol for Constructing a Rat Wound Model of Type 1 Diabetes
Published on: February 17, 2023
Streptozotocin-diabetes impairs prolactin binding to Leydig cells in prepubertal and pubertal rats
1Department of Endocrinology, Dr. A.L.M. Post Graduate Institute of Basic Medical Sciences, University of Madras, Taramani, Chennai, India.

Abstract:
Prolactin (PRL) binding to Leydig cells in prepubertal and pubertal streptozotocin (STZ)-diabetic and insulin-treated rats was studied. Prepubertal (30-day-old) and pubertal (50-day-old) rats were made diabetic by single injection of STZ (120 and 100 mg/kg b.wt, respectively). After 3 days of STZ administration, a group of rats was given insulin injections subcutaneously (3 U/100 g b.wt/day in 2 equally divided doses). Animals of prepubertal and pubertal groups were killed on postnatal days 51 and 71, respectively. Age-dependent increase in serum testosterone, PRL levels and PRL receptors on Leydig cells were prevented by STZ-diabetes. Insulin administration partly or completely prevented these changes. These results suggest that steroidogenic defects in Leydig cells of prepubertal and pubertal diabetic rats may be associated with decrease in serum PRL levels and its receptors on Leydig cells. Insulin probably has a role in the maintenance of PRL receptor numbers on Leydig cells during pubertal maturation.

Related Concept Videos
 01:24
Type II Diabetes II: Pathophysiology
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by the...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
 01:25
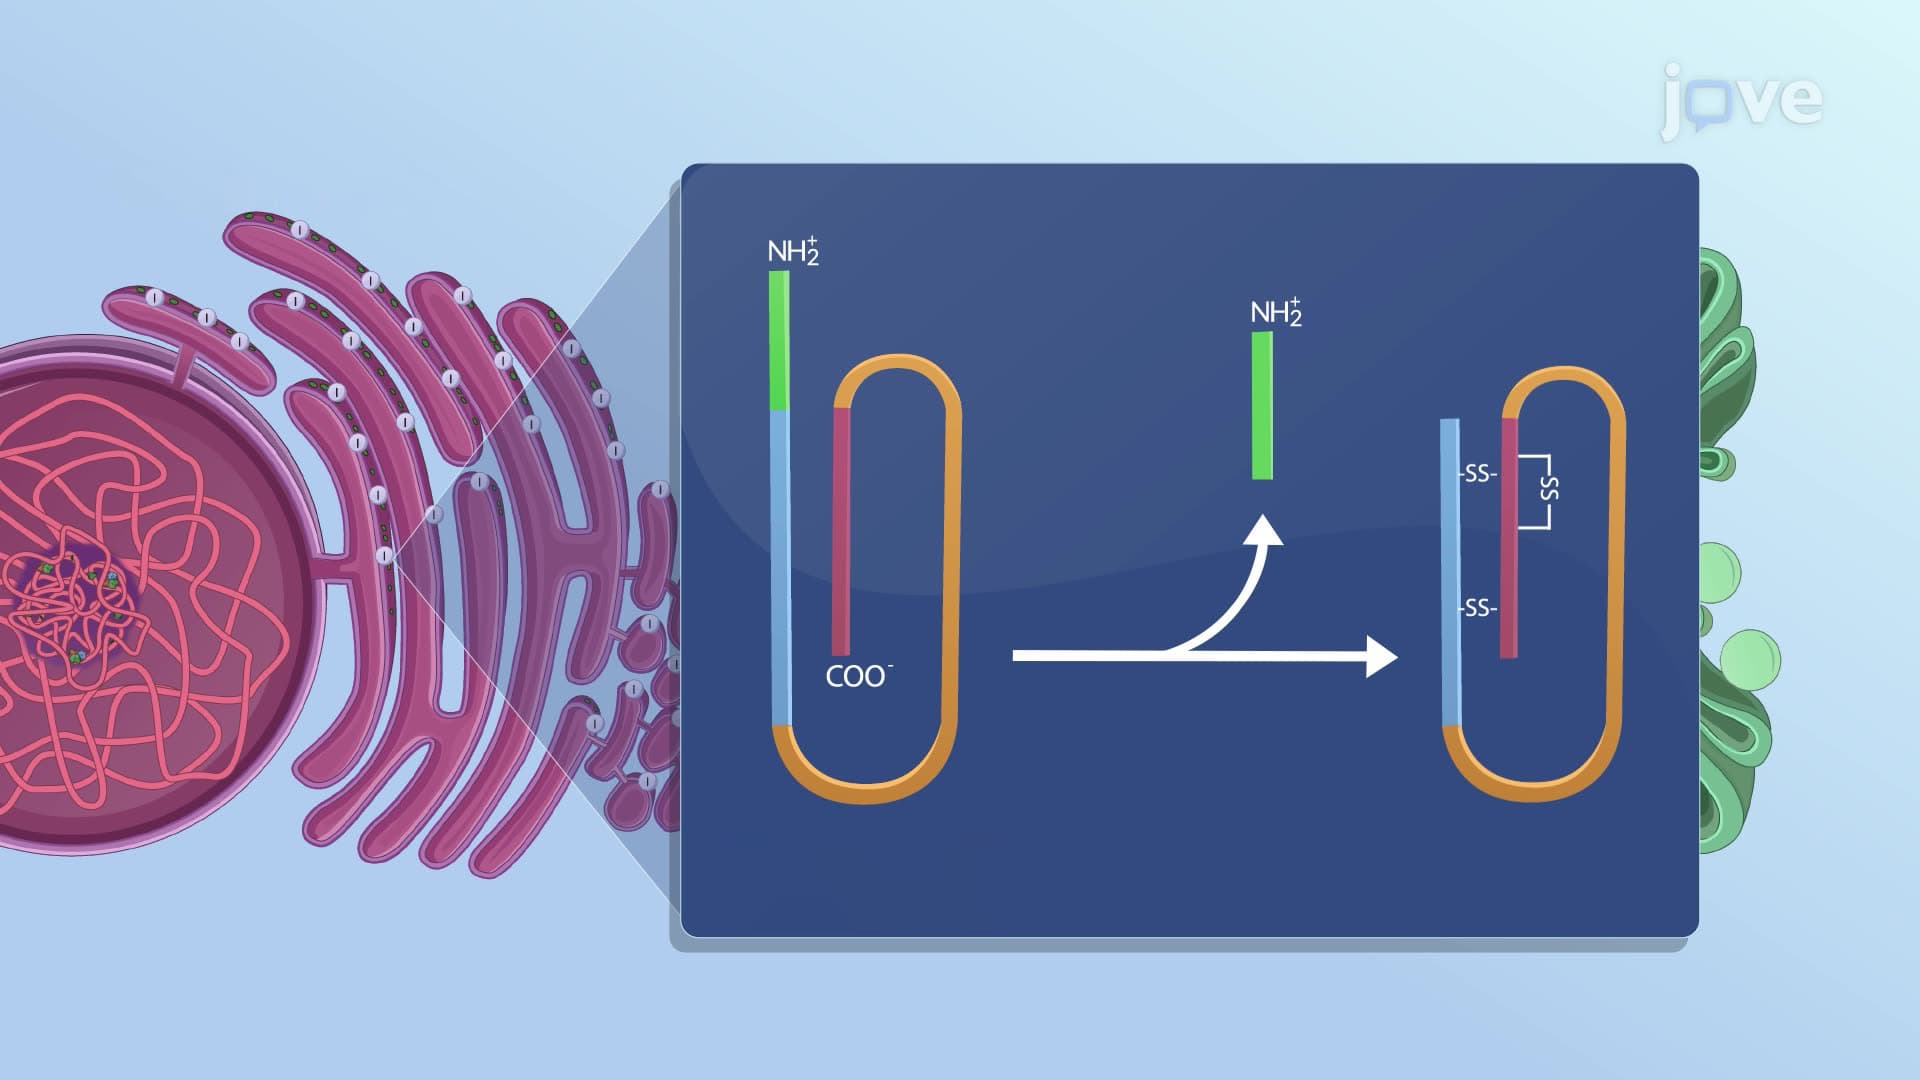
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment primarily uses...
 01:23
Dipeptidyl Peptidase 4 Inhibitors
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...