Related Experiment Video
Updated: Aug 14, 2026
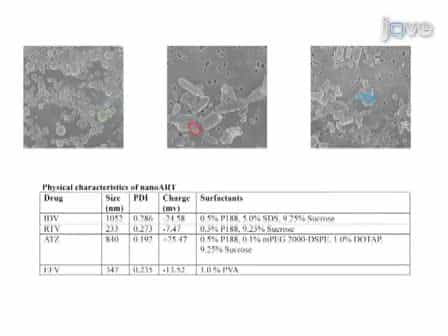

Methods Development for Blood Borne Macrophage Carriage of Nanoformulated Antiretroviral Drugs
Published on: December 9, 2010
Atovaquone suspension in HIV-infected volunteers: pharmacokinetics, pharmacodynamics, and TMP-SMX interaction study
J Falloon1, S Sargent, S C Piscitelli
1National Institute of Allergy and Infectious Diseases and the Warren G. Magnuson Clinical Center, National Institutes of Health, Bethesda, Maryland 20892-1880, USA.

Study Objective:
To evaluate the pharmacokinetics and safety of atovaquone suspension in volunteers infected with the human immunodeficiency virus ((HIV).
Design:
Open-label, nonrandomized study.
Setting:
Two clinical research centers.
Patients:
Twenty-two HIV-infected volunteers with a median CD4 cell count of 37 cells/mm3.
Interventions:
Patients received atovaquone suspension fasting or fed for 2-week periods with crossover at dosages of 500 mg/day, and randomization to fasting or fed at dosages of 750 and 1000 mg/day. A subset of patients also received 750 mg twice/day with food, and a subset of those who received 1000 mg/day fasting also received 1000 mg with food. During a long-term dosing phase, a subset of subjects were evaluated for an interaction between atovaquone and trimethoprim-sulfamethoxazole (TMP-SMX).
Measurements And Main Results:
Average steady-state atovaquone concentrations at 500 mg were 6.7 +/- 3.2 microg/ml fasted and 11.3 +/- 5.0 microg/ml with food; at 750 mg, 9.9 +/- 7.1 microg/ml fasted and 12.5 +/- 5.9 microg/ml with food; at 1000 mg, 9.7 +/- 4.3 microg/ml fasted and 13.6 +/- 5.0 microg/ml with food; and at 1500 mg, 21.1 +/- 5.0 microg/ml with food. Thus, plasma concentrations were not proportional to dose. Concomitant food ingestion resulted in a 1.3- to 1.7-fold increase in values. Average steady-state concentrations were less than 10 microg/ml in 21% and more than 15 microg/ml in 36% of patients at 1000 mg/day with food; at 750 mg twice/day, all five patients had levels above 15 microg/ml. Atovaquone suspension was well tolerated; diarrhea, nausea, fatigue, and rash were the most common adverse events. Concomitant administration of TMP-SMX did not change atovaquone concentrations and resulted in small decreases in concentrations of TMP (16%) and SMX (10%).
Conclusion:
Plasma concentrations are significantly higher when atovaquone suspension is administered with food compared with fasting. Total doses of 1500 mg/day are likely to achieve concentrations effective for prophylaxis of Pneumocystis carinii pneumonia.


Related Concept Videos
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:21
Antiprotozoal Agents