Related Experiment Video
Updated: Oct 18, 2026

A Model of Self-limited Acute Lung Injury by Unilateral Intra-bronchial Acid Instillation
Published on: August 30, 2019
Unilateral pulmonary interstitial emphysema following pneumonia in a preterm infant successfully treated with
D O'Donovan1, M Wearden, J Adams
1Department of Pediatrics, Baylor College of Medicine, Houston, Texas 77030, USA.

Insights
A preterm infant with Staphylococcus aureus pneumonia experienced severe pulmonary interstitial emphysema. Prolonged selective bronchial intubation for 10 days led to clinical improvement and emphysema resolution, suggesting longer intubation may be needed.
Area of Science:
- Neonatal Medicine
- Pediatric Pulmonology
- Critical Care
Background:
- Premature infants, particularly those with respiratory distress, are susceptible to lung injuries.
- Pulmonary interstitial emphysema (PIE) is a serious complication in ventilated neonates.
- Staphylococcus aureus pneumonia can exacerbate respiratory compromise in preterm infants.
Observation:
- A 26-week's gestation preterm infant developed severe unilateral (right-sided) pulmonary interstitial emphysema.
- The infant's condition followed a diagnosis of Staphylococcus aureus pneumonia.
- The infant required mechanical ventilation and selective bronchial intubation.
Findings:
- Prolonged selective bronchial intubation, lasting 10 days, was implemented.
- This intervention resulted in significant clinical improvement for the infant.
- Resolution of the unilateral pulmonary interstitial emphysema was observed following the prolonged intubation.
Implications:
- Current recommendations for selective bronchial intubation duration for PIE may be insufficient.
- Extended selective bronchial intubation could be a crucial therapeutic strategy for unilateral PIE in preterm neonates.
- This case highlights the need for reassessing treatment protocols for severe PIE in premature infants.
Abstract:
We describe a ventilated preterm infant (26 week's gestation) who developed severe right-sided pulmonary interstitial emphysema following Staphylococcus aureus pneumonia. Prolonged selective bronchial intubation (10 days) resulted in a marked clinical improvement and resolution of the emphysema. Resolution of unilateral pulmonary interstitial emphysema may require a longer course of selective bronchial intubation than currently recommended.
Related Concept Videos
 01:17
Pulmonary Cycle: Exhalation
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia I: Introduction
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:23
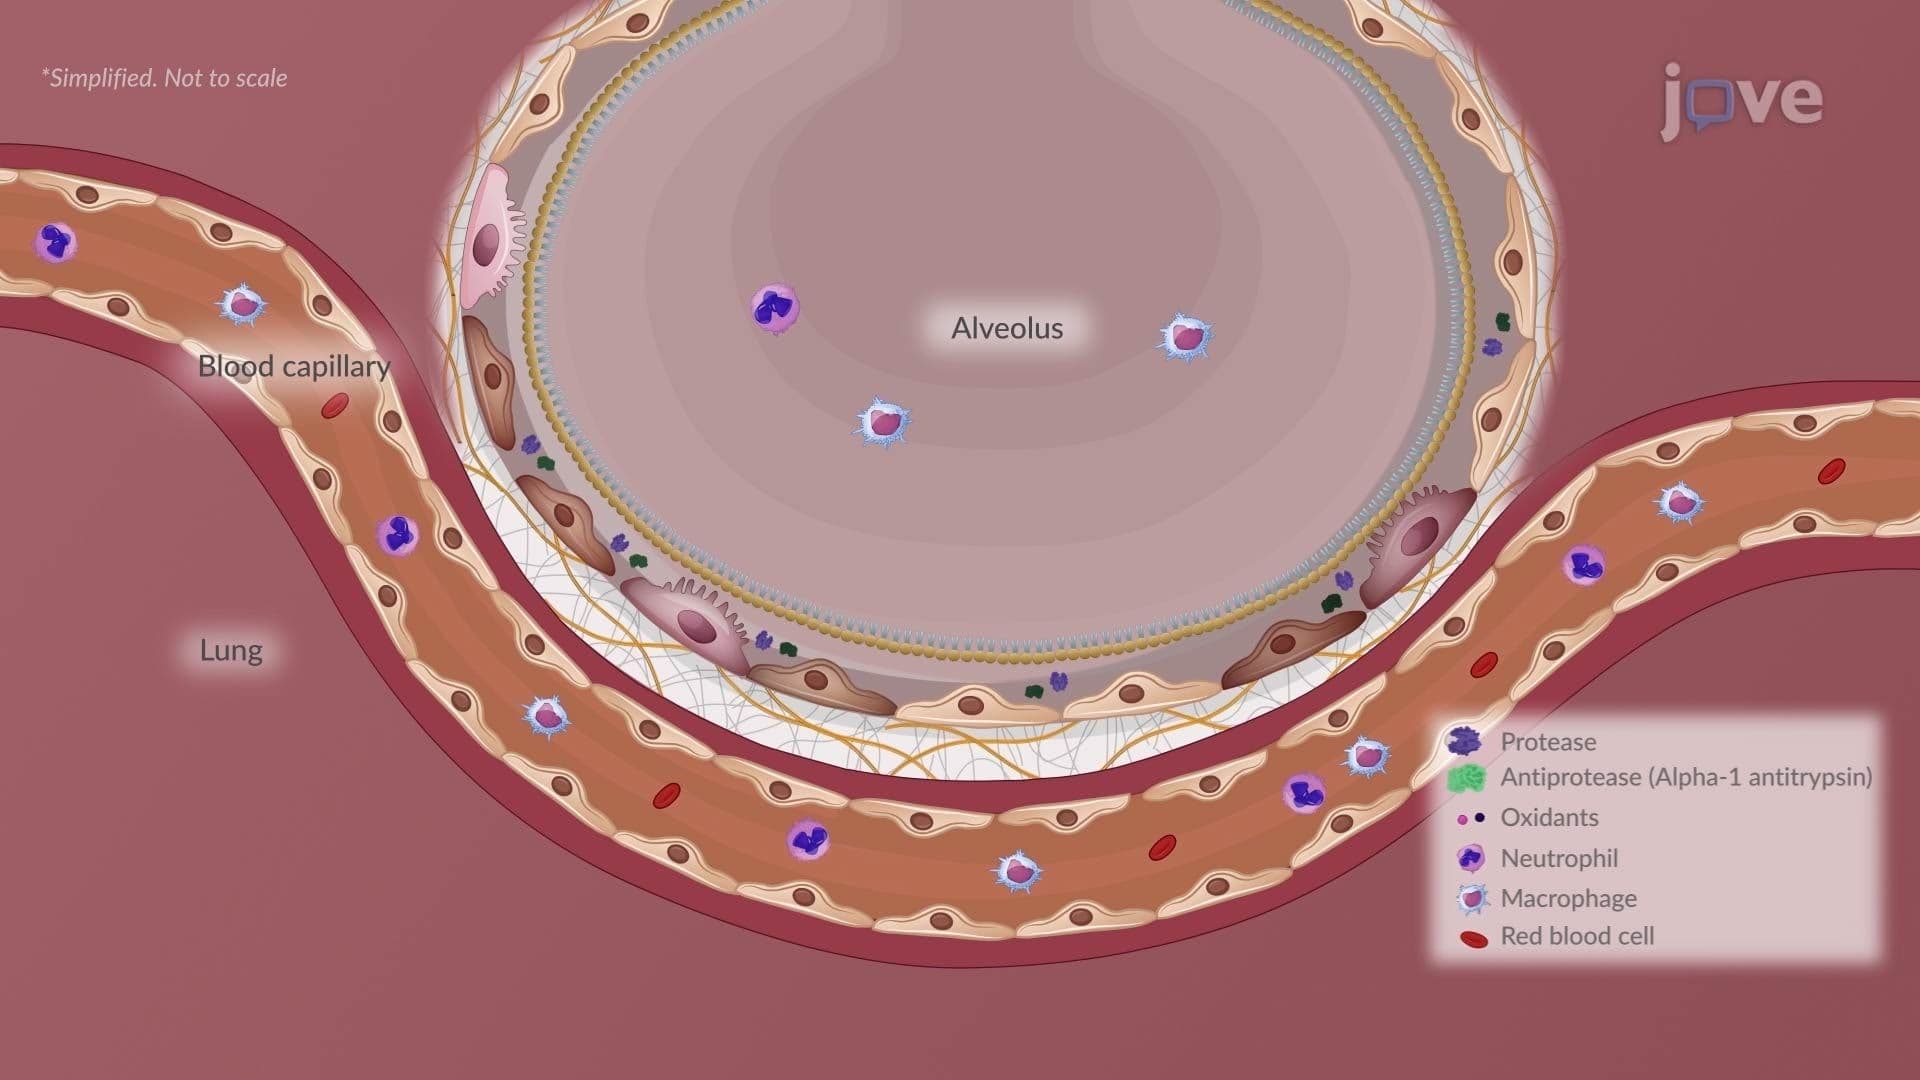
Chronic Obstructive Pulmonary Disease II: Emphysema