Phytate (IP6) is a powerful agent for preventing calcifications in biological fluids: usefulness in renal lithiasis

F Grases1, A Costa-Bauzá

  • 1Laboratory of Investigation into Renal Lithiasis, Faculty of Sciences, University of Illes Balears, Palma de Mallorca, Spain.

Anticancer Research
|January 8, 2000
PubMed

Related Concept Videos

Drug Distribution: Tissue Binding01:21

Drug Distribution: Tissue Binding

Upon entering the systemic circulation, drugs can distribute into the interstitial and intracellular fluid of various tissue cells. This distribution is facilitated by the binding of drugs to different cellular components within tissues, which may lead to drug accumulation in specific areas. Drugs bound to tissue components serve as reservoirs that release free drugs back into the system, prolonging the drug's overall action. However, this accumulation can also result in local toxicity.
For...
Drug Elimination by Renal Route: Tubular Reabsorption01:22

Drug Elimination by Renal Route: Tubular Reabsorption

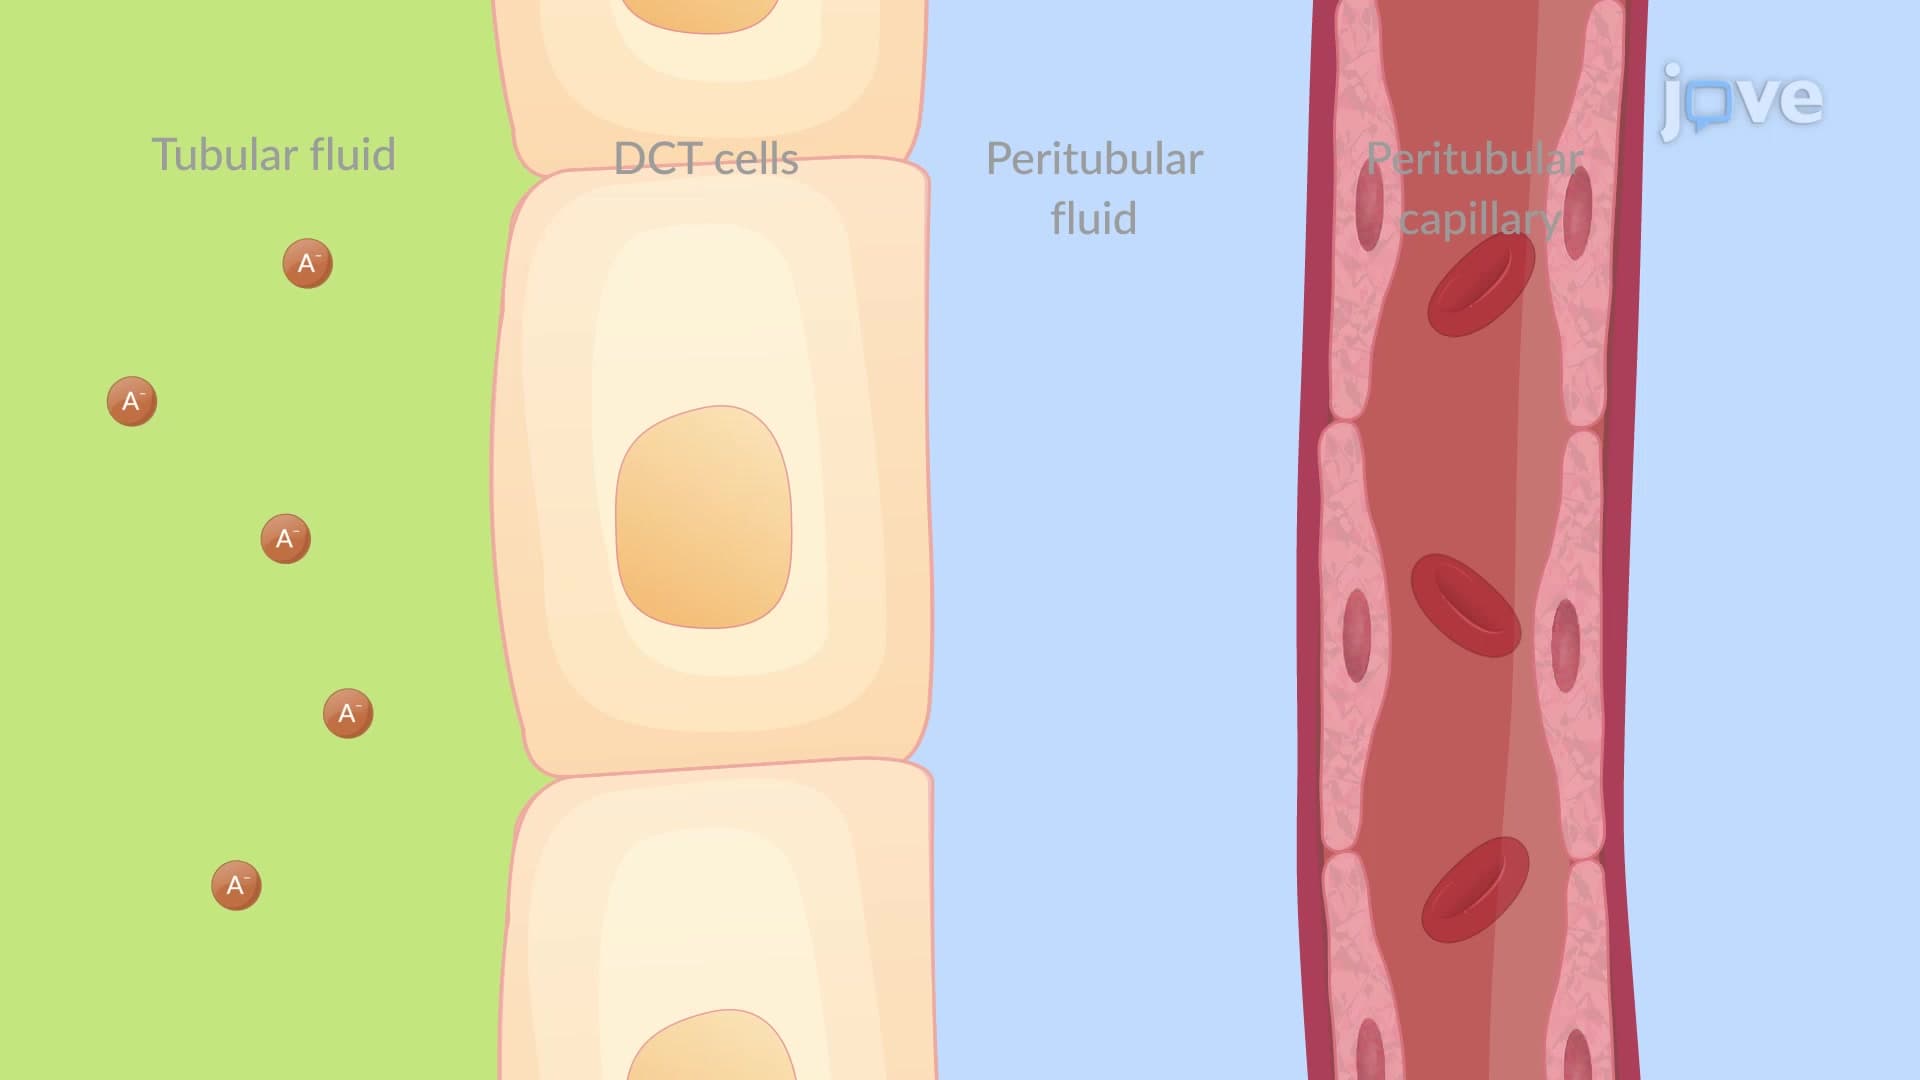
During the process of renal excretion, as the glomerular filtrate progresses to the distal convoluted tubule (DCT), drugs that are highly permeable, lipophilic, and nonionized undergo passive reabsorption from the tubular fluid into the surrounding peritubular capillaries. This reabsorption process restricts their elimination through the kidneys. However, the majority of drugs are either weak acids or weak bases, and their ionization level is dependent on pH. By altering the pH of urine, the...
Renal Drug Excretion: Tubular Secretion01:28

Renal Drug Excretion: Tubular Secretion

Active tubular secretion is a robust, energy-demanding process that utilizes carrier systems to transport drugs into renal tubules. The active renal secretion systems include the organic anion transporter (OAT) for weak acids and the organic cation transporter (OCT) for weak bases. Structurally similar drugs can compete for the same transporter, potentially leading to drug accumulation and toxicity. However, this principle can be exploited therapeutically. One example is probenecid (Probalan),...
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations01:26

Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations

Renal calculi, commonly termed kidney stones, are crystalline solid masses that form in the kidneys but can occur at any point within the urinary system, encompassing the kidneys, ureters, bladder, and urethra.The pathophysiology of renal stones involves several key factors: supersaturation of the urine with stone-forming constituents, changes in urine pH, a decrease in urine volume, and the presence of substances that promote or inhibit stone formation.Supersaturation of Urine: This is the...
Urinary Tract Calculi III: Medical Management01:30

Urinary Tract Calculi III: Medical Management

The diagnosis of renal calculi involves several imaging techniques, including non-contrast CT scans and ultrasound. These methods help visualize kidney stones, assess their size and location, and detect possible obstructions. Additionally, Measuring urine pH is useful for diagnosing specific stone types, such as struvite (alkaline pH) and uric acid stones (acidic pH). Cystine stones are primarily linked to cystinuria, a genetic condition. A urinalysis helps detect blood in the urine (hematuria)...
Urinary Tract Calculi IV: Nutrition Therapy and Prevention01:27

Urinary Tract Calculi IV: Nutrition Therapy and Prevention

Management of renal calculi focuses on effective strategies like tailored nutrition and hydration therapy. Adjusting diet and fluid intake reduces stone formation and recurrence, making these interventions simple yet powerful in kidney stone prevention and management.Understanding Kidney StonesKidney stones form when calcium, oxalate, uric acid, and cystine concentrate and crystallize in urine. Factors contributing to their formation include genetic predisposition, certain medical conditions,...