Related Experiment Video
Updated: Oct 18, 2026
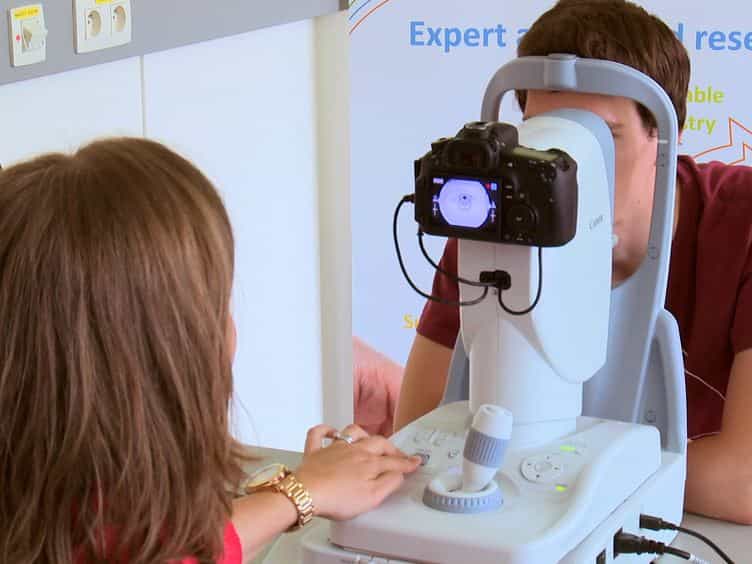
Fundus Photography as a Convenient Tool to Study Microvascular Responses to Cardiovascular Disease Risk Factors in Epidemiological Studies
Published on: October 22, 2014
[Cardiovascular manifestations of Behçet's disease]
B Wechsler1, L T Du, E Kieffer
1Service de Médecine Interne, CHU Pitié-Salpêtrière, Paris.

Vascular involvement in Behçet's disease, recognized since 1946, is peculiar since it occurs in young subjects with no vascular risk factor. Recurrent phlebitis, sometimes associated with fever and biological signs of inflammation, commonly involve the large vessels (superior and inferior vena cava, hepatic veins) and cerebral veins. Arterial involvement was more recently identified and is expressed by thrombosis, stenosis and/or aneurysms diversely associated. Aneurysms, true "arterial aphthae", may be multifocal and can involve all arterial territories with a clear preference for the abdominal aorta and the pulmonary arteries (Hughes-Stovin syndrome). Mortality is significant due to rupture and the risk of recurrence. Cardiac involvement includes coronary artery disease which merits attention since it affects young subjects and is often expressed by myocardial infarction or angina; all three tunics can be involved; mortality is high: 20% in the months or years following diagnosis. A few cases of recurrent pericarditis have been reported. Myocardiopathy can be of inflammatory nature or secondary to coronary artery disease. Endocardiac involvement may be limited to valve disease or spread to the ventricular wall. Endomyocardial fibrosis is exceptional and usually associated with intracavitary thrombus formation. Coagulation disorders have been reported but they cannot explain the different thrombotic manifestations which are probably the consequence of an abnormal response of the vascular endothelial cells.
Vascular involvement in Behçet's disease, recognized since 1946, is peculiar since it occurs in young subjects with no vascular risk factor. Recurrent phlebitis, sometimes associated with fever and biological signs of inflammation, commonly involve the large vessels (superior and inferior vena cava, hepatic veins) and cerebral veins. Arterial involvement was more recently identified and is expressed by thrombosis, stenosis and/or aneurysms diversely associated. Aneurysms, true "arterial aphthae", may be multifocal and can involve all arterial territories with a clear preference for the abdominal aorta and the pulmonary arteries (Hughes-Stovin syndrome). Mortality is significant due to rupture and the risk of recurrence. Cardiac involvement includes coronary artery disease which merits attention since it affects young subjects and is often expressed by myocardial infarction or angina; all three tunics can be involved; mortality is high: 20% in the months or years following diagnosis. A few cases of recurrent pericarditis have been reported. Myocardiopathy can be of inflammatory nature or secondary to coronary artery disease. Endocardiac involvement may be limited to valve disease or spread to the ventricular wall. Endomyocardial fibrosis is exceptional and usually associated with intracavitary thrombus formation. Coagulation disorders have been reported but they cannot explain the different thrombotic manifestations which are probably the consequence of an abnormal response of the vascular endothelial cells.
Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection