Related Experiment Video
Updated: Aug 17, 2026


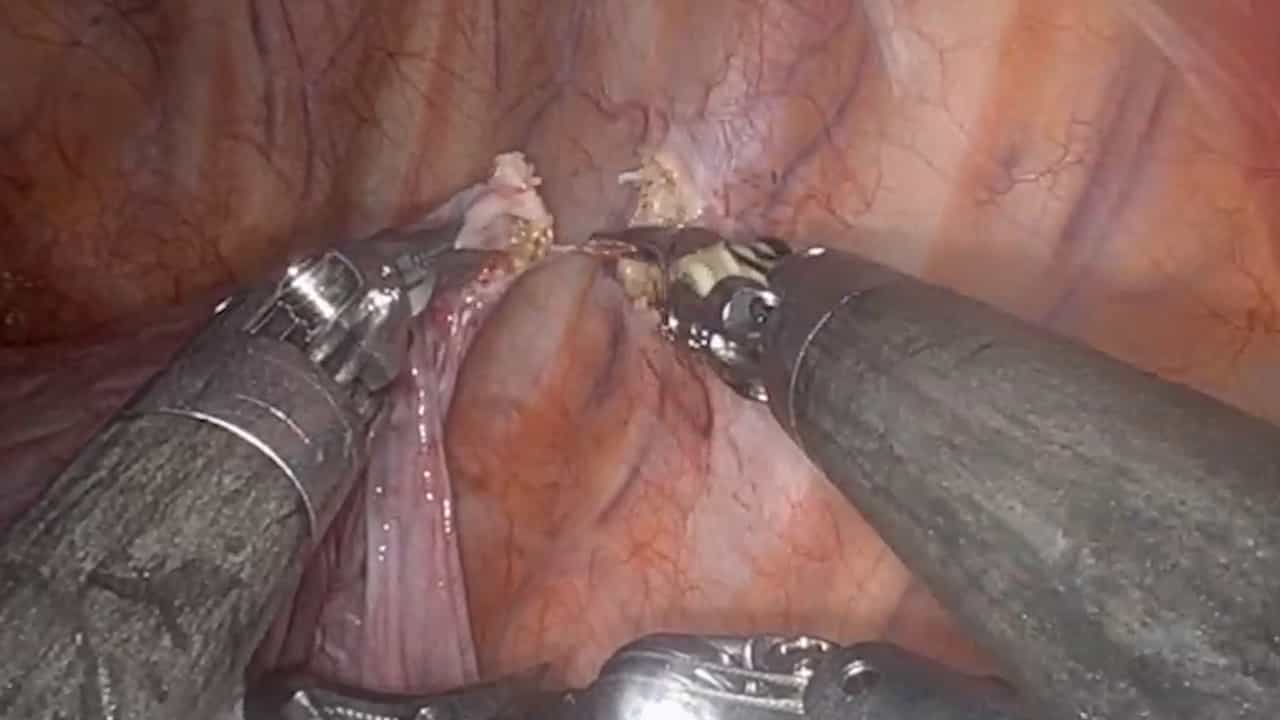
Non-Intubated Video-Assisted Thoracoscopic Surgery
Published on: May 26, 2023
Efficacy of primary and secondary video-assisted thoracic surgery in children
F J Rescorla1, K W West, C A Gingalewski
1Department of Surgery, Indiana University School of Medicine, Indianapolis, USA.

Insights
Video-assisted thoracic surgery (VATS) is safe and effective for pediatric patients, offering short recovery times. However, outcomes may be impacted by complex conditions like empyema with bronchopleural fistula.
Area of Science:
- Pediatric surgery
- Thoracic surgery
- Minimally invasive procedures
Background:
- Video-assisted thoracic surgery (VATS) is a common diagnostic and therapeutic approach in pediatric care.
- Assessing the accuracy, efficacy, and safety of VATS in children is crucial.
Purpose of the Study:
- To evaluate the accuracy and efficacy of primary and secondary VATS in pediatric patients.
- To identify complications associated with VATS in children.
Main Methods:
- 104 VATS procedures were analyzed in 87 pediatric patients (6 months to 19 years) between 1993 and 1999.
- Procedures included pulmonary nodule excision, infiltrate biopsy, mediastinal mass management, empyema decortication, and pneumothorax treatment.
- Secondary VATS was performed in 20 patients with prior thoracic interventions.
Main Results:
- VATS demonstrated efficacy in 93 cases for diagnosis or therapy.
- Conversion to open thoracotomy occurred in 11% of cases.
- Average thoracostomy tube drainage was 2.2 days, and average length of stay was 3.7 days, with no bleeding complications or VATS-related deaths.
Conclusions:
- VATS is a safe and effective primary and secondary procedure in children, associated with short chest tube drainage and hospital stays.
- Prolonged drainage and stay may occur with empyema and bronchopleural fistula, where VATS might be less beneficial.
Background/Purpose:
Video-assisted thoracic surgery (VATS) is used commonly for diagnostic and therapeutic procedures in children. The purpose of this study was to determine the accuracy, efficacy, and complications associated with primary and secondary VATS in children.
Methods:
Eighty-seven infants, children, and adolescents underwent 104 VATS procedures between March 1993 and April 1999. There were 47 boys and 40 girls with an age range of 6 months to 19 years. VATS was performed for excision of pulmonary nodule (n = 51), biopsy of infiltrate (n = 14), excision or biopsy mediastinal mass (n = 12), decortication of empyema (n = 16), pleurodesis and bleb excision for pneumothorax (n = 5), pleurolysis for P32 administration (n = 3), esophageal myotomy (n = 2), and thymectomy (n = 1). In 6 children a contralateral thoracic procedure was performed along with VATS (3 VATS, 3 thoracotomies). Secondary VATS was performed in 20 after prior thoracic procedures.
Results:
VATS was efficacious for diagnostic or therapeutic purposes in 93 cases. Overall, 11 (11%) VATS required conversion to open thoracotomy. Average length of thoracostomy tube drainage (CTD) was 2.2 days, and average length of stay (LOS) was 3.7 days. Complications included prolonged air leak (> 7 days) in 3 (2 empyema, 1 nodule). Two children with malignancy and pulmonary infiltrates died within 30 days of progressive respiratory failure. There were no bleeding complications or deaths related to VATS.
Conclusions:
VATS is a safe and effective primary and secondary procedure in children resulting in a short length of CTD and LOS. Duration of CTD and LOS are prolonged if empyema is associated with a bronchopleural fistula, and VATS may not be of value in this setting.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques