Related Experiment Video
Updated: Jun 29, 2026


Detection of MicroRNA Expression in the Kidneys of Immunoglobulin A Nephropathic Mice
Published on: July 8, 2020
Administration of IgG Fc fragments prevents glomerular injury in experimental immune complex nephritis
C Gómez-Guerrero1, N Duque, M T Casado
1Renal Research Laboratory, Department of Immunology, Fundación Jiménez Díaz, Autonoma University, Hospital Clínico San Carlos, Madrid, Spain.

Most human nephritis is due to glomerular deposition and/or formation of immune complexes (IC). In cultured mesangial cells, Fc receptor stimulation induces proliferation, matrix synthesis, and release of several mediators implicated in the initiation and progression of glomerular injury. Since Ig Fc fragments in vitro modified these phenomena, we studied the effects of systemic administration of IgG Fc fragments on the evolution of experimental IC nephritis. Fc fragment injection (1 mg/day i.p.) to rats with ongoing nephritis (proteinuria 20-50 mg/24 h vs 9 +/- 0.2 mg/24 h in controls) markedly ameliorates proteinuria, renal function, and morphological renal lesions. This was accompanied by a reduction in the renal synthesis of chemokines (monocyte chemoattractant protein-1, IFN-inducible protein-10, and cytokine-induced neutrophil chemoattractant-1), matrix proteins, and growth factors (platelet-derived growth factor, and TGF-beta), and in the activity of transcription factors. The treatment did not affect the glomerular deposition of IgG IC and complement C1q. In contrast, a decrease in the renal expression and production of C3 was observed without changes in serum complement levels. In vitro, very low complement consumption and no C3b covalent interaction were observed with Fc fragments, confirming that they did not modify systemic complement activity. These results indicate that the administration of Fc fragments prevents the development of glomerular damage in an aggressive model of proliferative glomerulonephritis through mechanisms involving a reduced local generation of complement, chemokines and growth factors. Modulation of IC-mesangial cell interaction by Fc fragment administration could represent a new approach to the treatment of severe immune nephritis.
Most human nephritis is due to glomerular deposition and/or formation of immune complexes (IC). In cultured mesangial cells, Fc receptor stimulation induces proliferation, matrix synthesis, and release of several mediators implicated in the initiation and progression of glomerular injury. Since Ig Fc fragments in vitro modified these phenomena, we studied the effects of systemic administration of IgG Fc fragments on the evolution of experimental IC nephritis. Fc fragment injection (1 mg/day i.p.) to rats with ongoing nephritis (proteinuria 20-50 mg/24 h vs 9 +/- 0.2 mg/24 h in controls) markedly ameliorates proteinuria, renal function, and morphological renal lesions. This was accompanied by a reduction in the renal synthesis of chemokines (monocyte chemoattractant protein-1, IFN-inducible protein-10, and cytokine-induced neutrophil chemoattractant-1), matrix proteins, and growth factors (platelet-derived growth factor, and TGF-beta), and in the activity of transcription factors. The treatment did not affect the glomerular deposition of IgG IC and complement C1q. In contrast, a decrease in the renal expression and production of C3 was observed without changes in serum complement levels. In vitro, very low complement consumption and no C3b covalent interaction were observed with Fc fragments, confirming that they did not modify systemic complement activity. These results indicate that the administration of Fc fragments prevents the development of glomerular damage in an aggressive model of proliferative glomerulonephritis through mechanisms involving a reduced local generation of complement, chemokines and growth factors. Modulation of IC-mesangial cell interaction by Fc fragment administration could represent a new approach to the treatment of severe immune nephritis.
More Related Videos
 09:43
Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
 14:18
Dioscin Mediated IgA Nephropathy Alleviation by Inhibiting B Cell Activation In Vivo and Decreasing Galactose-Deficient IgA1 Production In Vitro
Published on: October 13, 2023
Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:19
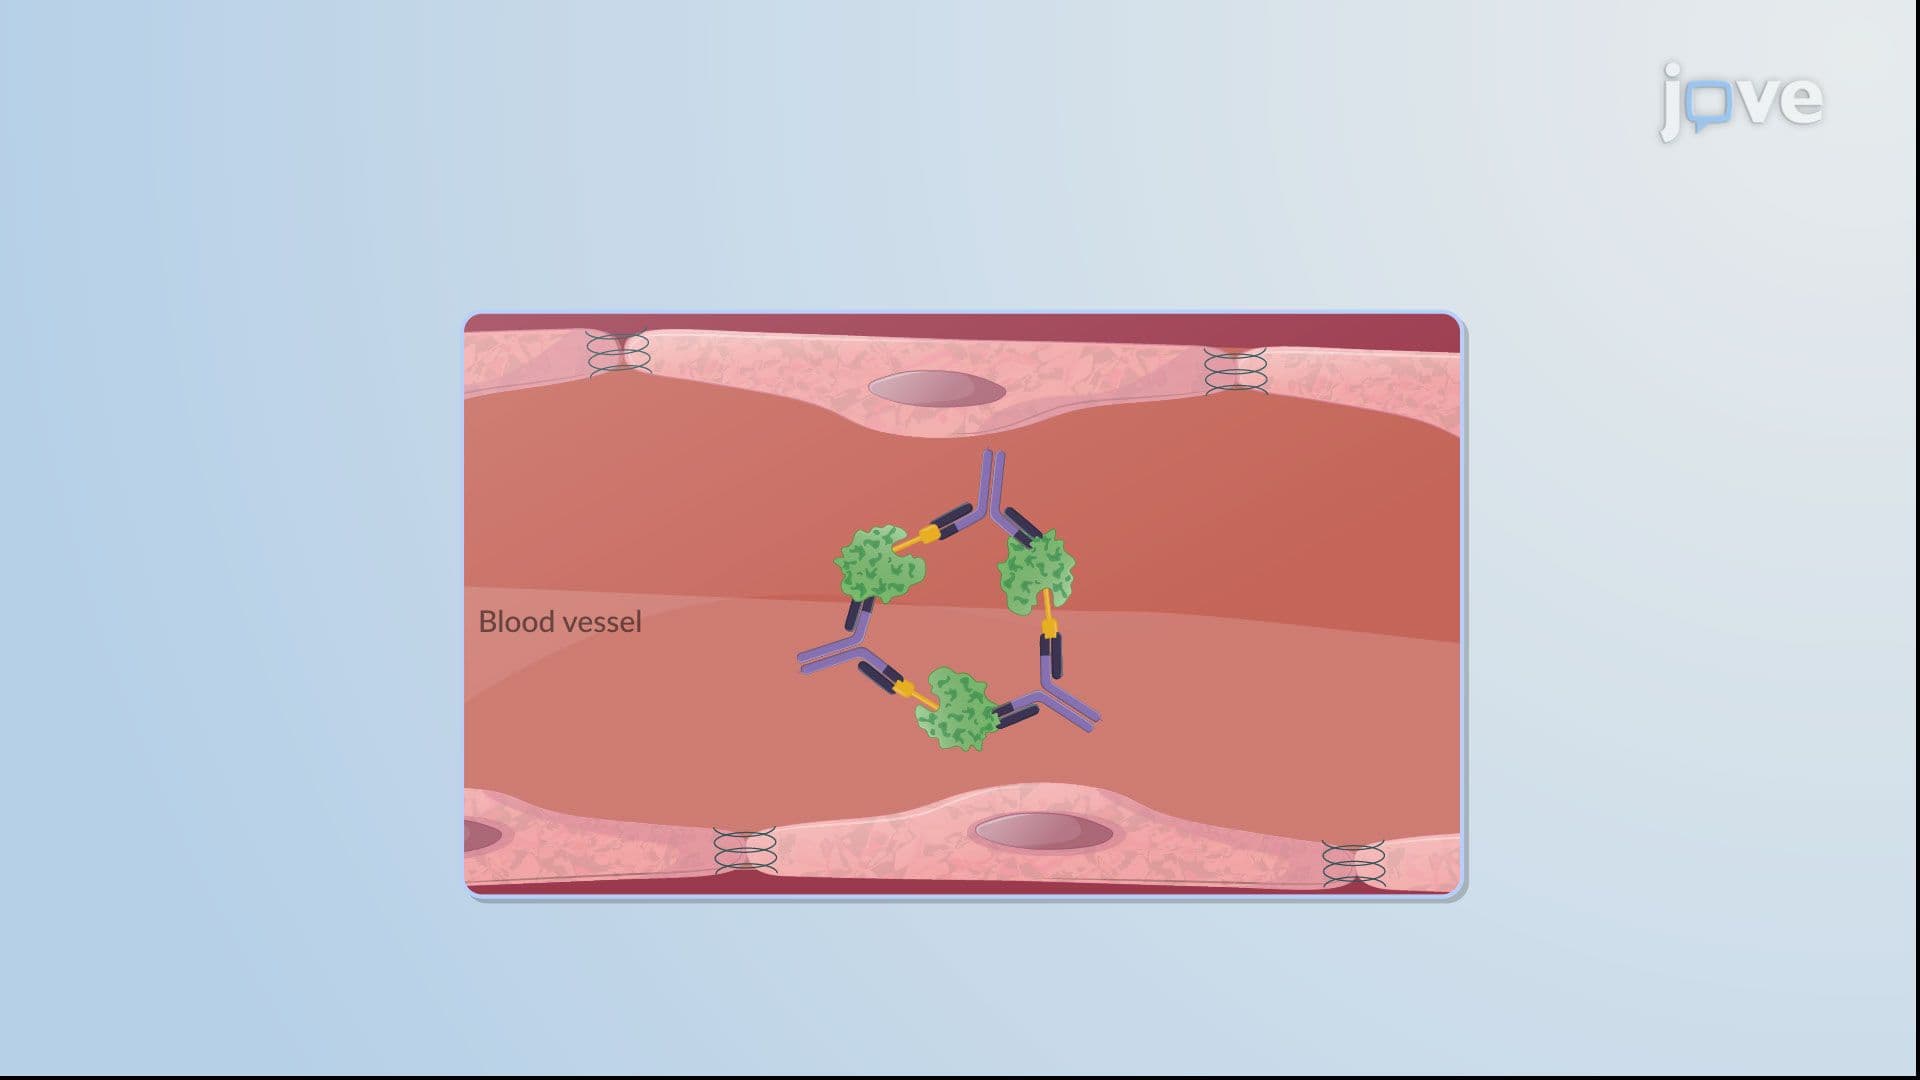
Hypersensitivity Reactions: Immune-Complex Reactions