Related Experiment Video
Updated: Oct 17, 2026
A Novel Method: Super-selective Adrenal Venous Sampling
Published on: September 15, 2017
Baseline and stimulated catecholamine secretion in normotensive patients with active acromegaly: acute effects of
G D Rio1, A Velardo, C Mascadri
1Department of Internal Medicine, Section of Endocrinology and Metabolism, University of Modena, Italy. delrio@unimo.it

Objective:
Alterations in catecholamine plasma levels may contribute to the cardiovascular complications of acromegaly. Since few data are available on the catecholamine secretory dynamics in active acromegaly and no evidence exists on catecholamine variations during GH decrease, we studied acromegalic patients before and during octreotide administration.
Methods:
We evaluated the catecholamine responses to upright posture and a cold pressure test (CPT) in 11 acromegalic (A) patients before and during continuous administration of octreotide (500 microgram/24h by s.c. pump) compared with 11 normal (N) subjects.
Results:
All the acromegalic patients showed left ventricular cardiac hypertrophy. The cardiovascular responses to upright posture were similar between normal subjects and acromegalics both before and during octreotide treatment. The basal levels of norepinephrine (NE) were significantly higher in A patients compared with N subjects (423+/-45 vs 264+/-32pg/ml, P<0. 05) and decreased during therapy (291+/-32pg/ml; P<0.01). The increase in plasma NE during upright posture was significantly lower in A than in N subjects (P<0.01), but was restored to normal during octreotide treatment. CPT increased systolic and diastolic blood pressure, pulse rate and NE plasma levels in N (P<0.05) but not in A subjects both before and during octreotide treatment.
Conclusions:
Our data demonstrate the presence of increased basal NE levels in acromegalic patients with a defective sympathetic response to stimuli. Short-term octreotide infusion is able to induce a reduction in the basal levels of NE and a normalization of the catecholamine response to posture.

Related Concept Videos
 01:19
Cushing Syndrome II: Pathophysiology
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...
 01:25
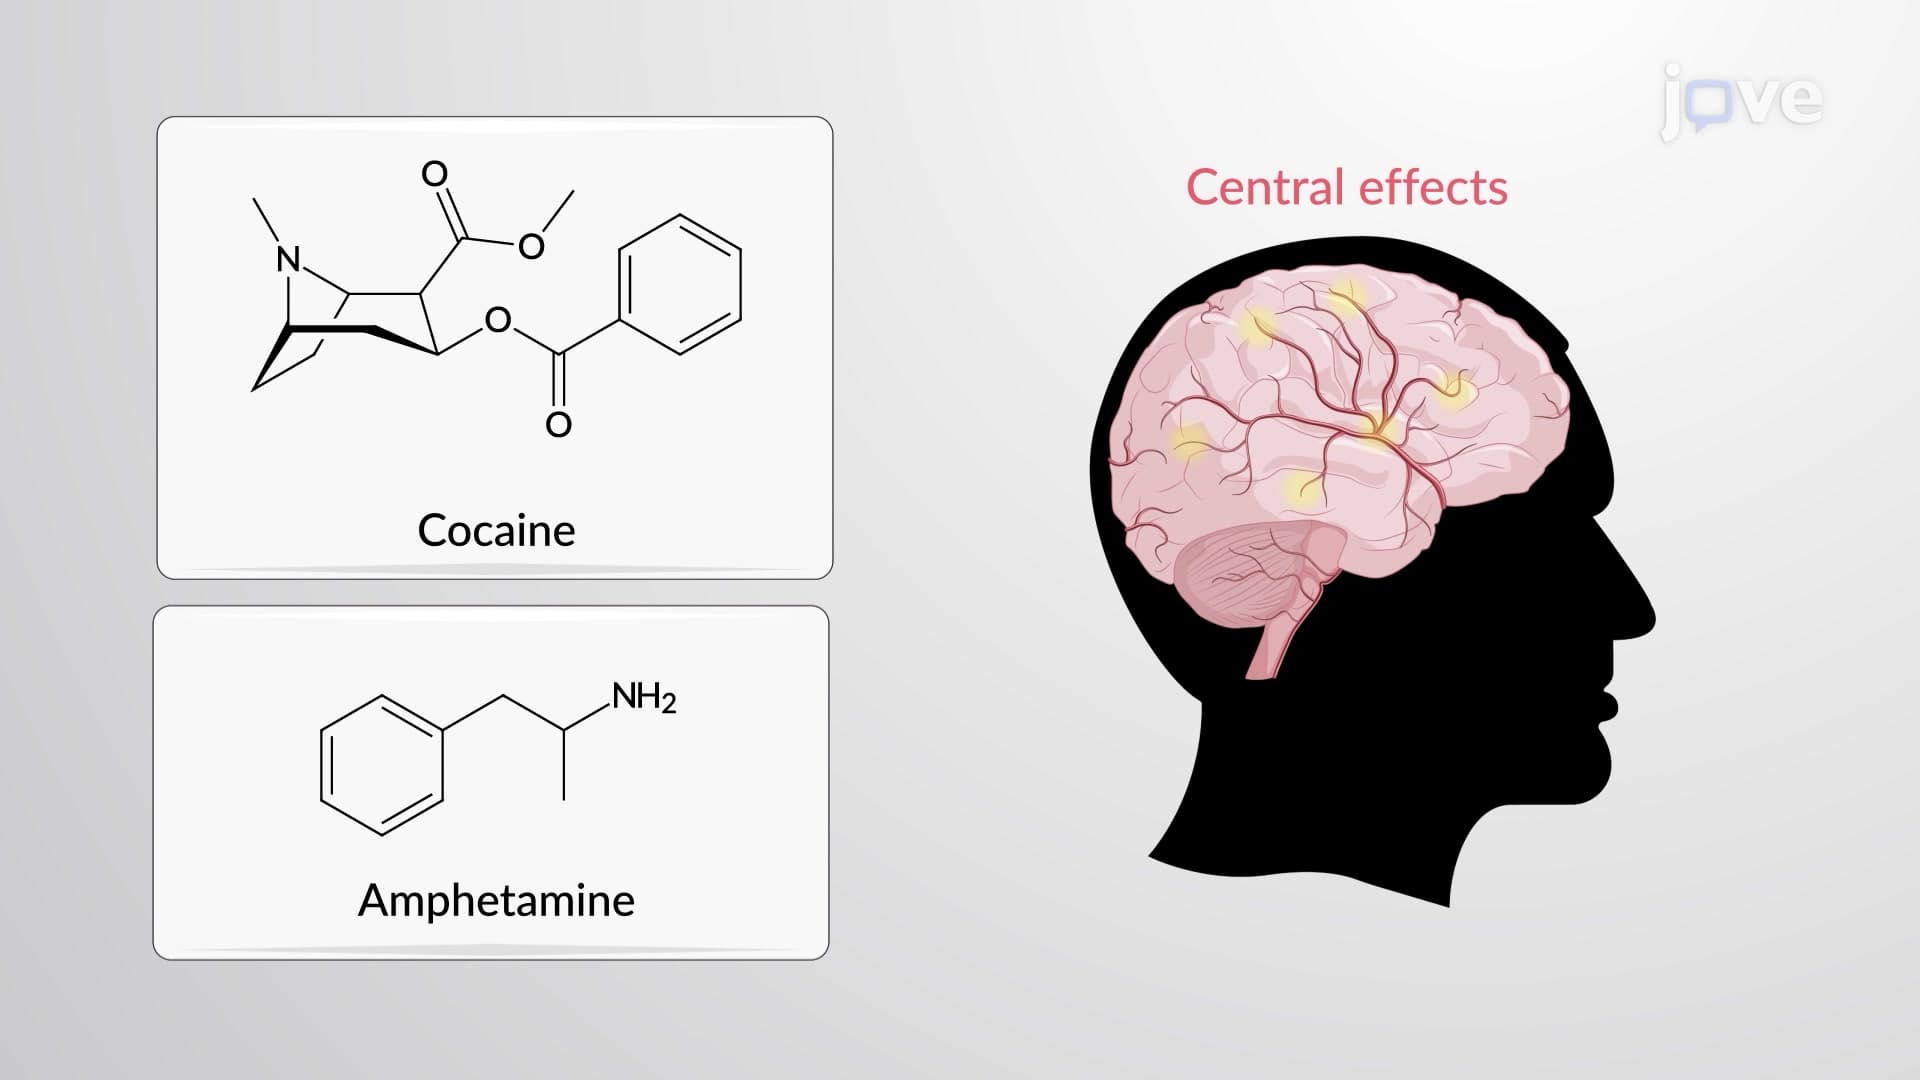
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:26
Cushing Syndrome I: Introduction
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:15
Hypoglycemia and Glucagon