Related Experiment Video
Updated: Oct 17, 2026
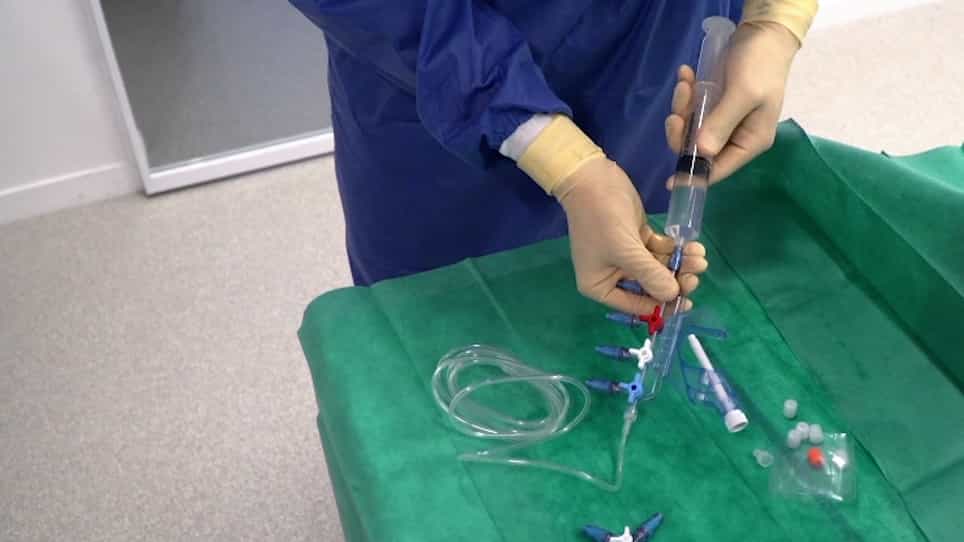
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Bacterial contamination of ready-to-use 1-L feeding bottles and administration sets in severely compromised intensive
L M Mathus-Vliegen1, J M Binnekade, R J de Haan
1Department of Gastroenterology and Hepatology, the Academic Medical Center, University of Amsterdam, The Netherlands.

Insights
Enteral feeding bottles showed a low 4% contamination rate, but administration sets were highly contaminated. Manipulation of feeding systems, not hanging time, correlated with bacterial growth, posing a risk in intensive care units.
Area of Science:
- Critical Care Medicine
- Infectious Diseases
- Microbiology
Background:
- Enteral feeding in intensive care units (ICUs) requires sterile formula to prevent infectious complications.
- Prepacked, large-volume formula containers have shown bacterial contamination rates between 4% and 15%.
Purpose of the Study:
- To investigate the microbial contamination rate of 1-L feeding bottles and newly designed administration sets.
- To assess contamination over hanging times up to 24 hours in the ICU.
Main Methods:
- Prospective observational cohort study in a university hospital ICU.
- Consecutive patients receiving nasojejunal tube feeding for at least 4 days.
- Cultures of feeding bottles, administration sets, and gastric/tracheobronchial aspirates at specified intervals.
Main Results:
- 4% of feeding bottles and 74% of administration sets exceeded 10(2) CFU/mL.
- Gastric and bronchial aspirates showed high positive rates (90% and 92%).
- Contamination was linked to system manipulation and retrograde bacterial growth, not solely hanging time.
Conclusions:
- Despite system design, a 4% contamination rate of sterile feedings with clinically relevant bacteria is concerning.
- Bacterial growth primarily occurred in manipulated systems, indicating potential for contamination during handling.
- Enterobacteriaceae family was prevalent, contributing to nosocomial infections.
Objective:
In intensive care patients, enteral feeding requires sterile feedings because of infectious complications and adequate supplements to meet nutritional needs. Heretofore, prepacked, large-volume formula containers were developed, but bacterial contamination occurred in 4% to 15%. Our objective was to investigate the microbial contamination rate of 1-L feeding bottles and newly designed administration sets over hanging times of 24 hrs in the intensive care unit (ICU).
Design And Setting:
A prospective observational cohort study of patients admitted to the ICU of a university hospital.
Patients:
All consecutive patients fed via a nasojejunal tube for at least 4 days.
Measurements:
Cultures of feeding bottles, administration sets, and gastric and tracheobronchial aspirates at day 0, 1, 2, 4, and 7.
Results:
A total of 4% of feeding bottles and 74% of infusion sets contained >10(2) colony forming units (CFU)/mL. Gastric and bronchial aspirates were positive in 90% and 92%, respectively. Bacterial counts of feeding bottles were 10(2)-10(5) CFU/mL, and the main bacteria isolated included Enterobacter cloacae, Klebsiella oxytoca, and enterococci. One third of all cultured bacteria in feeding bottles, administration sets, stomach, and lungs belonged to the Enterobacteriaceae family, which was held responsible for the nosocomial infections in the ICU. None of the 1-L feeding bottles with a hanging time of 19-24 hrs was contaminated. Only bottles that had to be exchanged because of need for a faster rate of infusion proved to be contaminated, apparently without clinical consequences. With time and the increasing severity of disease, the administration sets became contaminated at an increasingly faster rate and with higher bacterial counts mainly through retrograde growth of endogenous bacteria. The final step of bottle contamination might have been the bacterial transfer by nurses' hands.
Conclusion:
Despite an almost ideal design of the enteral nutrition delivery system, a 4% contamination rate of initially sterile feedings with clinically relevant bacteria and the fact that only manipulated systems showed bacterial growth are of concern.


Related Concept Videos
 01:30
Cleaning, Sterilization, and Disinfection
Cleaning
The cleaning process usually involves using water with detergents or enzymatic cleaner and removing foreign material from objects and surfaces, including organic material such as body fluids or inorganic material like soil. Cleaning is performed before high-level disinfection and sterilization because foreign materials on the cover of the devices interfere with process...
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:14
Scale-Up Processes
 01:17
Transmission-based Precautions I: Contact, Enteric, and Droplets
Contact Precautions:
Contact precautions are the measures taken to prevent the transmission of infectious agents, especially epidemiologically important microorganisms such as MRSA or influenza, primarily transmitted through direct or indirect contact with an...
 01:30
Reservoir of Infection
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...