Related Experiment Video
Updated: Sep 12, 2026
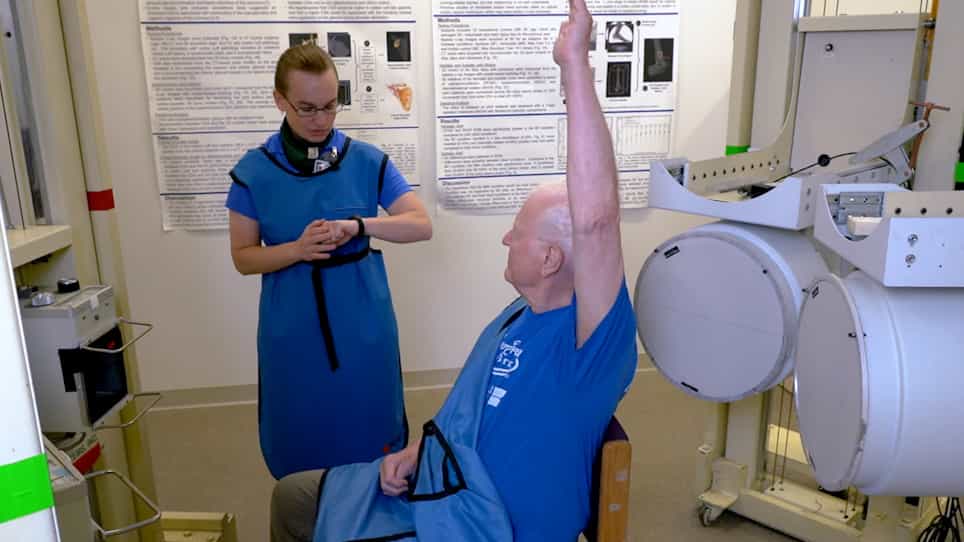

Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
[Acute acromioclavicular dislocations]
N Riand1, C Sadowski, P Hoffmeyer
1Clinique et policlinique d'orthopédie et de l'appareil moteur, Hôpital Universitaire de Genève.

Abstract:
Acromioclavicular dislocations represent over 10% of acute traumatic injuries to the shoulder girdle. The mechanism is usually a direct impact on the shoulder with the arm in adduction, producing rupture of the acromioclavicular (AC) ligaments, then of the coracoclavicular (CC) ligament, with displacement of the lateral end of the clavicle. Rockwood described 6 grades of injury. Physical examination usually provides the diagnosis, which is confirmed by radiological examination. X-rays centered on the AC joint, if necessary with forceful adduction of both shoulders or under traction, are useful to evaluate the severity of the lesion. Grade I and II lesions are usually treated conservatively by simply immobilizing the arm for 3 to 4 weeks. Surgical treatment is usually advocated for grade IV, V and VI lesions: AC or CC fixation, sometimes associated with ligament repair, depending on the surgeons. AC pinning or C-C screw fixation are the techniques most often used. Management of grade III lesions remains controversial. Some authors advocate immediate surgical treatment in young, active patients, in heavy laborers and even in slender individuals. The choice of the operative technique is controversial, as no single technique has clearly proved to be superior to others. Other authors advocate conservative treatment, which gives functional results which patients consider quite acceptable, with faster recovery; patients should be informed that results are essentially similar, whatever the treatment. The possibility of performing secondary operations with good results in cases with failure of conservative management is a further argument in favor of applying conservative therapy first in acute injuries.
More Related Videos
 07:10
Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
 04:01
The Modified Single-working Portal Technique Using Lasso-loop Stitch with Needle for Arthroscopic Subscapularis Repair
Published on: August 8, 2025
Related Concept Videos
 01:28
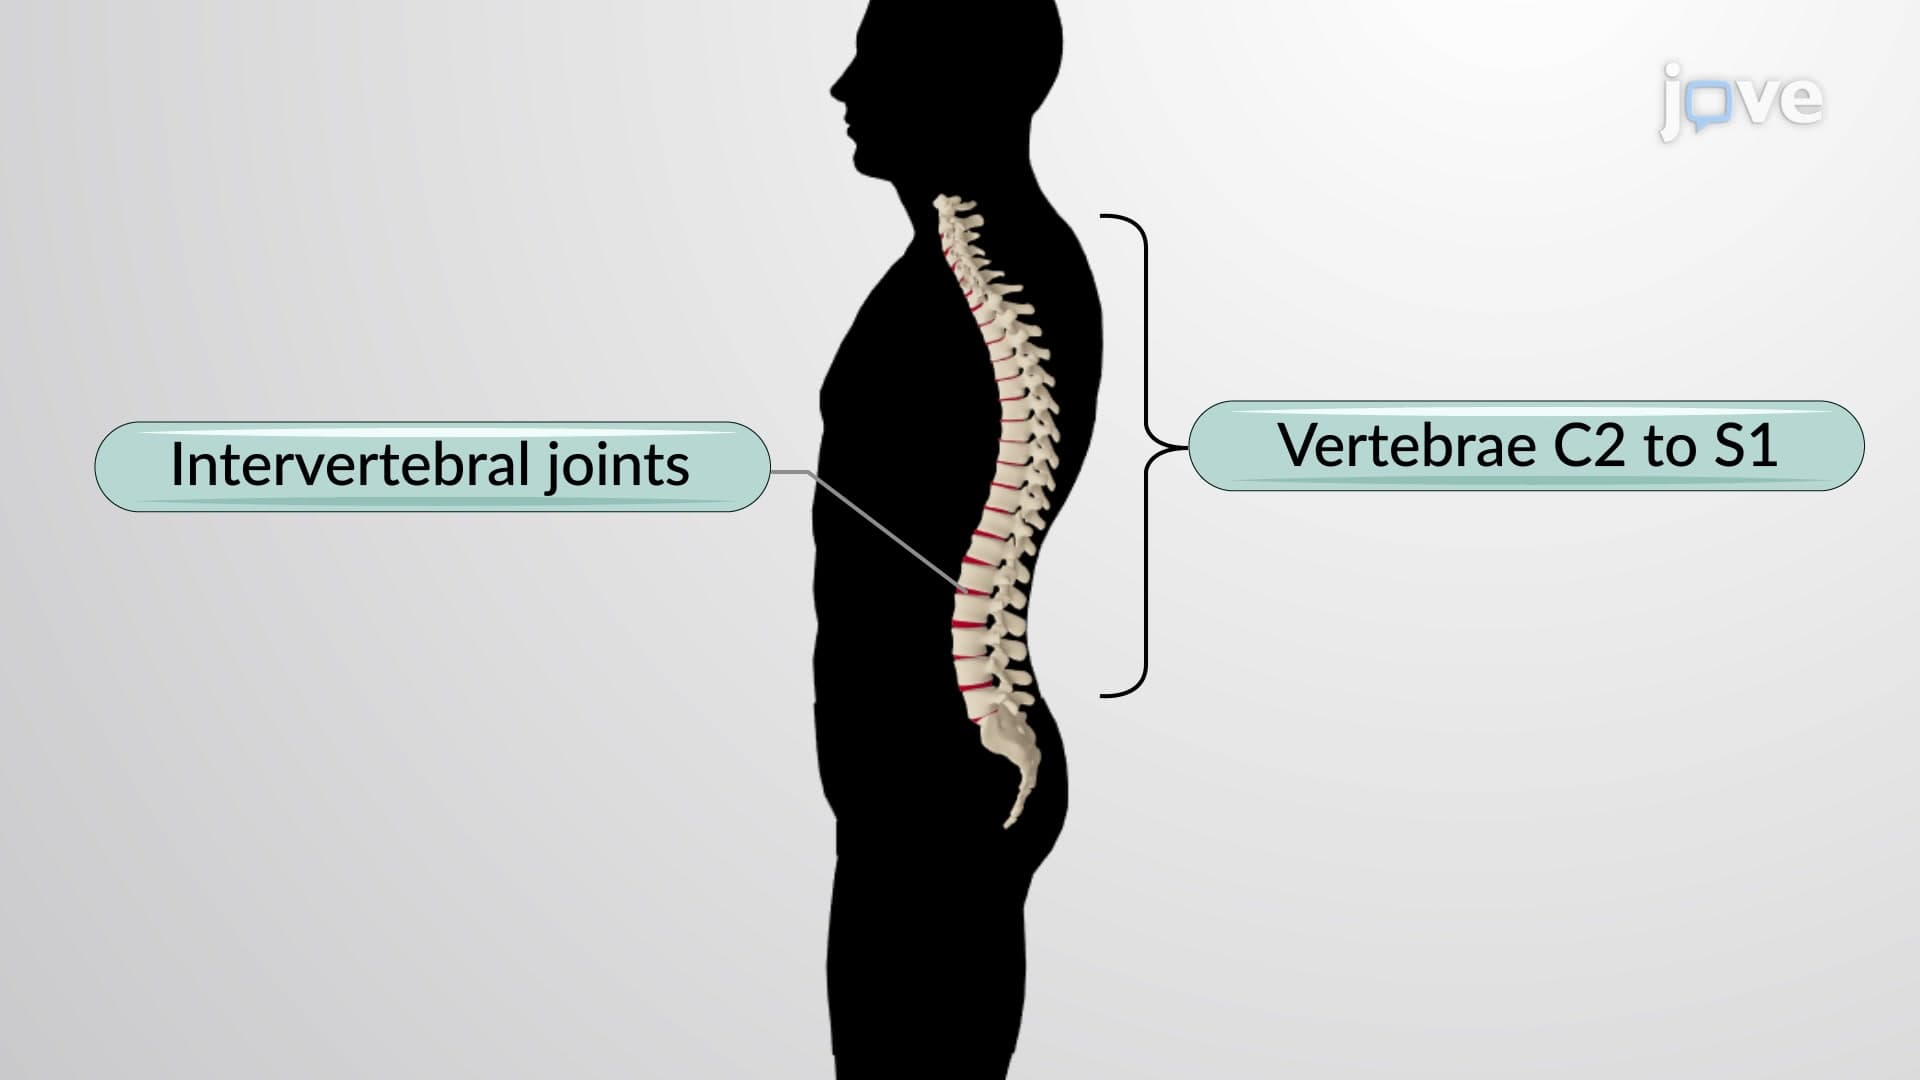
Articulations of the Vertebral Column
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...
 01:30
Acute Pharyngitis
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: