Pain and inflammatory hyperalgesia induced by intradermal injections of human platelets and leukocytes
Related Experiment Video
Updated: Oct 17, 2026
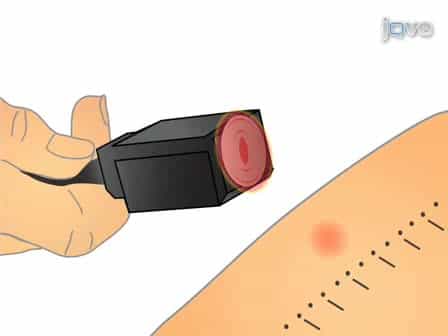
Determining heat and mechanical pain threshold in inflamed skin of human subjects
Published on: January 14, 2009
1Department of Physiology and Experimental Physiology, University of Erlangen/Nürnberg, Germany

Acute and prolonged inflammatory processes, induced by intradermal injections of autologous platelet preparations, leukocytes, platelet-leukocyte mixtures and vehicle solutions, were monitored in 20 human subjects for up to 48 h. Psychophysical methods were employed to assess the time course of pain response, and the development of hyperalgesia. Time course of the axon reflex erythema was analysed by computer based videography. Injections of functionally intact platelets [4.4 x 10(7)+/- 0.6 x 10(7)in 50 µl (mean +/- SEM)] caused distinct pain sensations [median pain rating 7.25 (25-75%: 6.5-7.5) on a scale form 0-10]. Both platelets injected through a microfilter (0.2 µm) and heat-inactivated platelets induced similar initial pain response; however, pain duration was significantly shorter than for intact platelets. Control injections of leukocytes (5.4 x 10(6)+/- 3.7 x 10(6)in 50 µl) and of vehicle solutions only caused minute pain sensations.Although platelet concentration in the mixture was only 50%, platelet/leukocyte mixtures produced axon reflex erythema that were significantly larger than those seen with naive platelets alone (11.1 +/- 2.3 vs 8.3 +/- 0.8 cm(2)). Intact platelets and heat-inactivated platelets both induced mechanical hyperalgesia and skin indurations at the injection site. Both reactions peaked between 6 and 24 h after the injection and disappeared within 48 h. Neither hyperalgesia, nor the development of indurations was noted at the injection sites of filtered platelets and vehicle solutions. Leukocyte injections induced hyperalgesia and indurations only in samples with a platelet contamination of more than 50 000 cells/µl. We conclude that platelets induce acute pain responses due to a soluble factor, whereas the development of hyperalgesia and the formation of indurations depends on a membrane-bound factor. Moreover, platelets and leukocytes act synergistically in nociceptor activation. Copyright 1999 European Federation of Chapters of the International Association for the Study of Pain.
Acute and prolonged inflammatory processes, induced by intradermal injections of autologous platelet preparations, leukocytes, platelet-leukocyte mixtures and vehicle solutions, were monitored in 20 human subjects for up to 48 h. Psychophysical methods were employed to assess the time course of pain response, and the development of hyperalgesia. Time course of the axon reflex erythema was analysed by computer based videography. Injections of functionally intact platelets [4.4 x 10(7)+/- 0.6 x 10(7)in 50 µl (mean +/- SEM)] caused distinct pain sensations [median pain rating 7.25 (25-75%: 6.5-7.5) on a scale form 0-10]. Both platelets injected through a microfilter (0.2 µm) and heat-inactivated platelets induced similar initial pain response; however, pain duration was significantly shorter than for intact platelets. Control injections of leukocytes (5.4 x 10(6)+/- 3.7 x 10(6)in 50 µl) and of vehicle solutions only caused minute pain sensations.Although platelet concentration in the mixture was only 50%, platelet/leukocyte mixtures produced axon reflex erythema that were significantly larger than those seen with naive platelets alone (11.1 +/- 2.3 vs 8.3 +/- 0.8 cm(2)). Intact platelets and heat-inactivated platelets both induced mechanical hyperalgesia and skin indurations at the injection site. Both reactions peaked between 6 and 24 h after the injection and disappeared within 48 h. Neither hyperalgesia, nor the development of indurations was noted at the injection sites of filtered platelets and vehicle solutions. Leukocyte injections induced hyperalgesia and indurations only in samples with a platelet contamination of more than 50 000 cells/µl. We conclude that platelets induce acute pain responses due to a soluble factor, whereas the development of hyperalgesia and the formation of indurations depends on a membrane-bound factor. Moreover, platelets and leukocytes act synergistically in nociceptor activation. Copyright 1999 European Federation of Chapters of the International Association for the Study of Pain.


Related Concept Videos
 01:25
Acute Inflammation III: Local and Systemic Effects
 01:22
Formation of the Platelet Plug
As the injured blood vessel contracts, endothelial cells undergo contraction, revealing collagen fibers in the basement membrane and underlying connective tissue. Furthermore, the plasma membrane of endothelial cells becomes adhesive, preparing the site for platelet adhesion. Platelets...
 01:26
Acute Inflammation I: Inflammatory Response
 01:26
Acute Inflammation II: Cellular Phase
 01:44
Nociception
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions