Related Experiment Video
Updated: Oct 17, 2026

A Versatile, Behavioral Method to Investigate Thyroid Hormone Effects on Cerebellar Function
Published on: October 6, 2023
Influence of timing and dose of thyroid hormone replacement on development in infants with congenital hypothyroidism
J J Bongers-Schokking1, H M Koot, D Wiersma
1Department of Endocrinology, the Department of Child and Adolescent Psychiatry, the Academic Hospital Sophia Children's Hospital, Rotterdam, The Netherlands.

Insights
Early, high-dose levothyroxine treatment for congenital hypothyroidism (CH) is crucial for optimal neurodevelopment. Prompt initiation of therapy before 13 days with adequate dosage ensures normal mental and psychomotor development in infants with CH.
Area of Science:
- Pediatric Endocrinology
- Neonatal Care
- Neurodevelopmental Pediatrics
Background:
- Congenital hypothyroidism (CH) can lead to suboptimal mental development if not treated promptly.
- Early diagnosis and intervention are critical for long-term neurodevelopmental outcomes in infants with CH.
Purpose of the Study:
- To evaluate the efficacy of early, high-dose levothyroxine treatment in preventing suboptimal mental development in neonates with CH.
- To determine the optimal treatment parameters for achieving normal neurodevelopmental outcomes in CH patients.
Main Methods:
- A study involving 61 neonates with CH (27 severe, 34 mild) was conducted, comparing early (<13 days) vs. late (>=13 days) and high (> or =9.5 microg/kg/d) vs. low (<9.5 microg/kg/d) initial levothyroxine doses.
- Neurodevelopment was assessed using the Bayley Scales of Infant Development (mental developmental index [MDI] and psychomotor developmental index [PDI]) between 10 and 30 months of age.
- Factors analyzed included socioeconomic status, treatment group, initial free thyroxine (FT(4)), and FT(4) levels during the first and subsequent nine months of treatment.
Main Results:
- In severe CH cases, only early, high-dose treatment resulted in normal MDI scores (124 +/- 16), while other groups scored between 97-103.
- Mild CH patients generally achieved normal scores (122-125), except for those treated late with a low dose (110 +/- 10).
- Treatment factors explained 43% of the variance in MDI and PDI scores, highlighting the impact of early and adequate levothyroxine therapy.
Conclusions:
- Optimal CH management involves achieving euthyroidism before the third week of life.
- Initiating levothyroxine therapy before 13 days with doses exceeding 9.5 microg/kg/d is recommended.
- Maintaining FT(4) concentrations in the upper normal range during the first year ensures normal psychomotor development in CH patients, regardless of disease severity.
Objectives:
To test whether early treatment with a high initial dose of levothyroxine can prevent suboptimal mental development in all neonates with congenital hypothyroidism (CH).
Study Design:
Sixty-one patients, 27 with severe CH and 34 with mild CH, were treated either early (<13 days) or late (> or =13 days) with either a high initial dose of levothyroxine (> or =9.5 microg/kg/d) or a low initial dose (<9.5 microg/kg/d). With these criteria, 4 treatment groups were formed. The results of the Bayley test, performed at the age of 10 to 30 months and expressed as mental developmental index (MDI) and psychomotor developmental index (PDI), were related to socioeconomic status, treatment group, initial free thyroxine (FT(4)) concentration, and mean FT(4) concentration during the first 3 months of treatment (FT(4)-A) and the ensuing 9 months (FT(4)-B).
Results:
Mean (+/- SD) MDI was 113 +/- 14, and mean PDI was 114 +/- 12. In the severe CH group, only the patients treated early with a high initial dose had normal MDI scores (124 +/- 16), whereas the scores of the other groups ranged from 97 to 103. In contrast, all patients in the mild CH group had normal scores (range, 122-125), except those in the group treated late with a low initial dose, whose score was 110 +/- 10. Forty-three percent of the variance in MDI and PDI scores was explained by treatment factors, such as the treatment group, initial FT(4) concentration, FT(4)-A, and FT(4)-B.
Conclusions:
Our data suggest that optimal treatment includes achievement of euthyroidism before the third week of life by initiation of therapy before 13 days with a levothyroxine dose above 9.5 microg/kg/d and maintenance of FT(4) concentrations in the upper normal range during the first year. Thus treated, patients with CH can achieve normal psychomotor development at 10 to 30 months, irrespective of the severity of the disease.
Related Concept Videos
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:20
Synthesis and Regulation of Thyroid Hormones
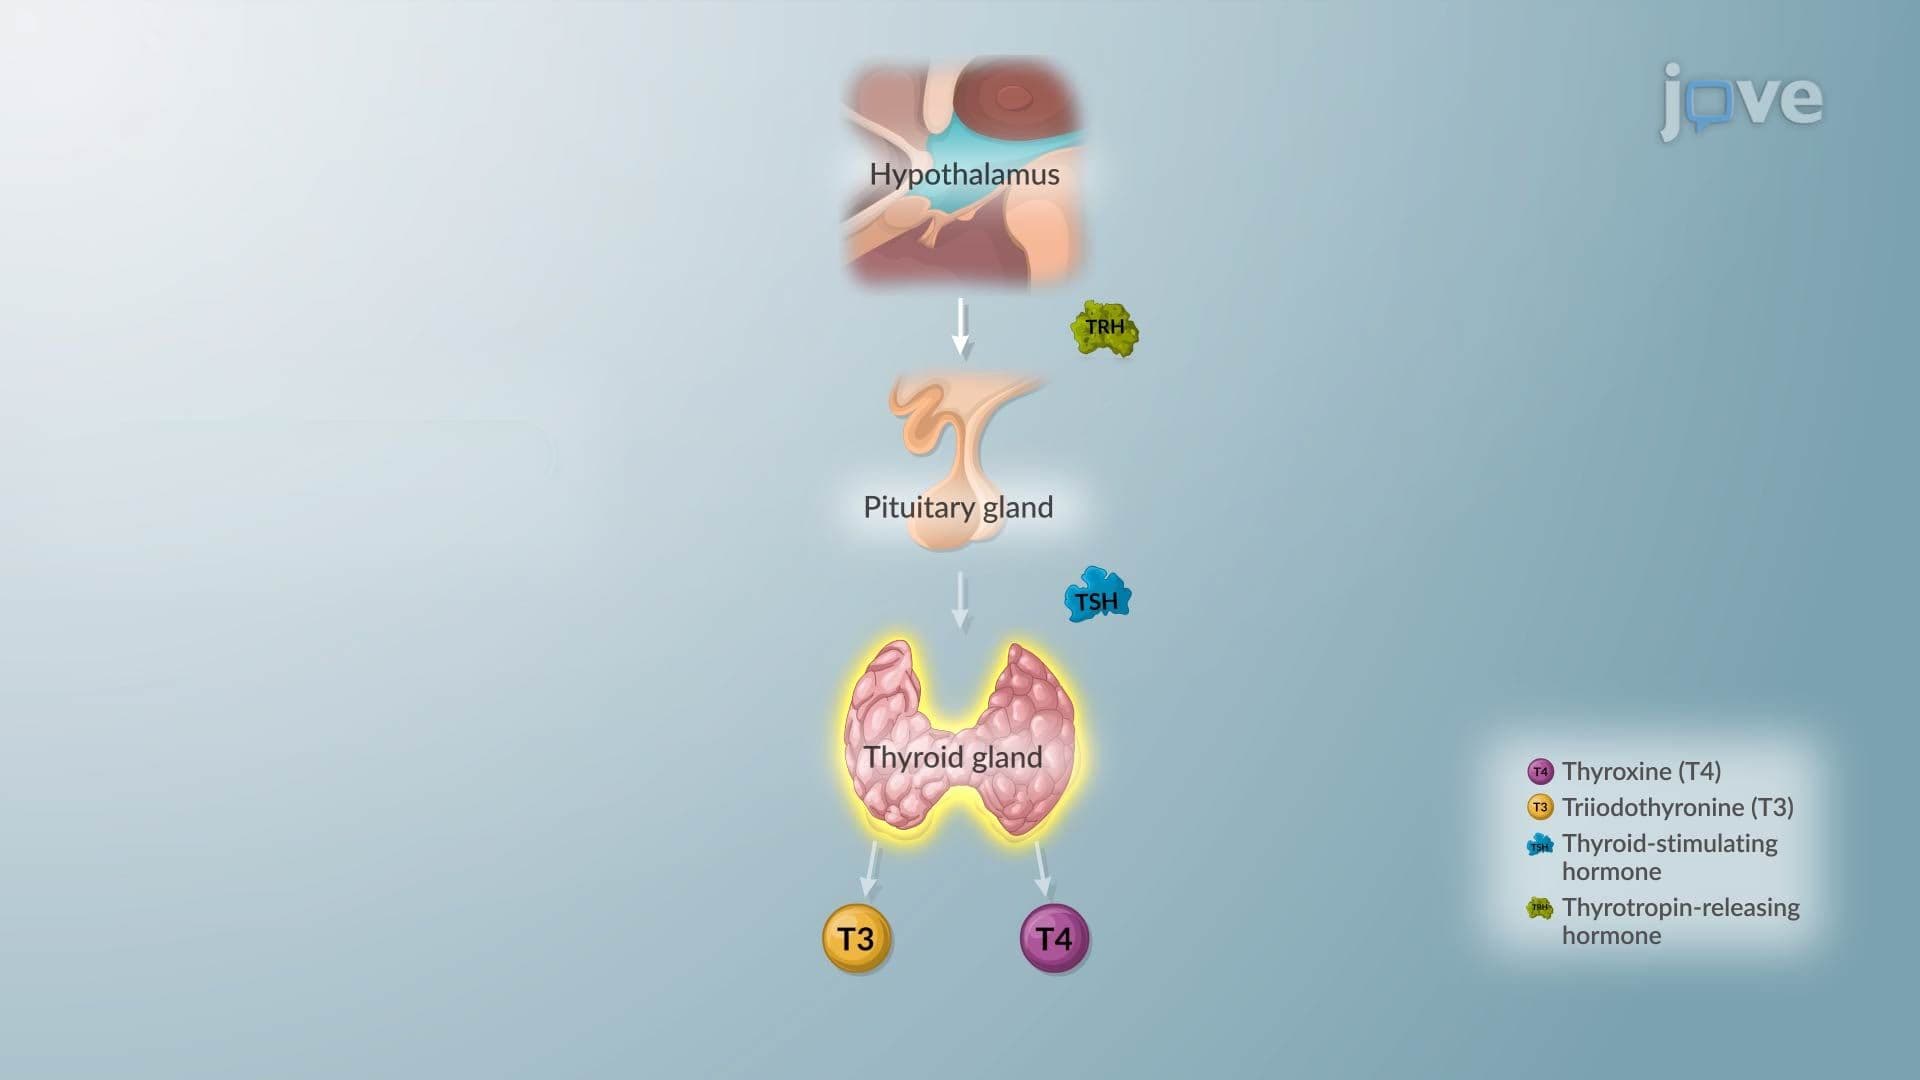
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:23
Hypothyroidism II: Pathophysiology
 01:21
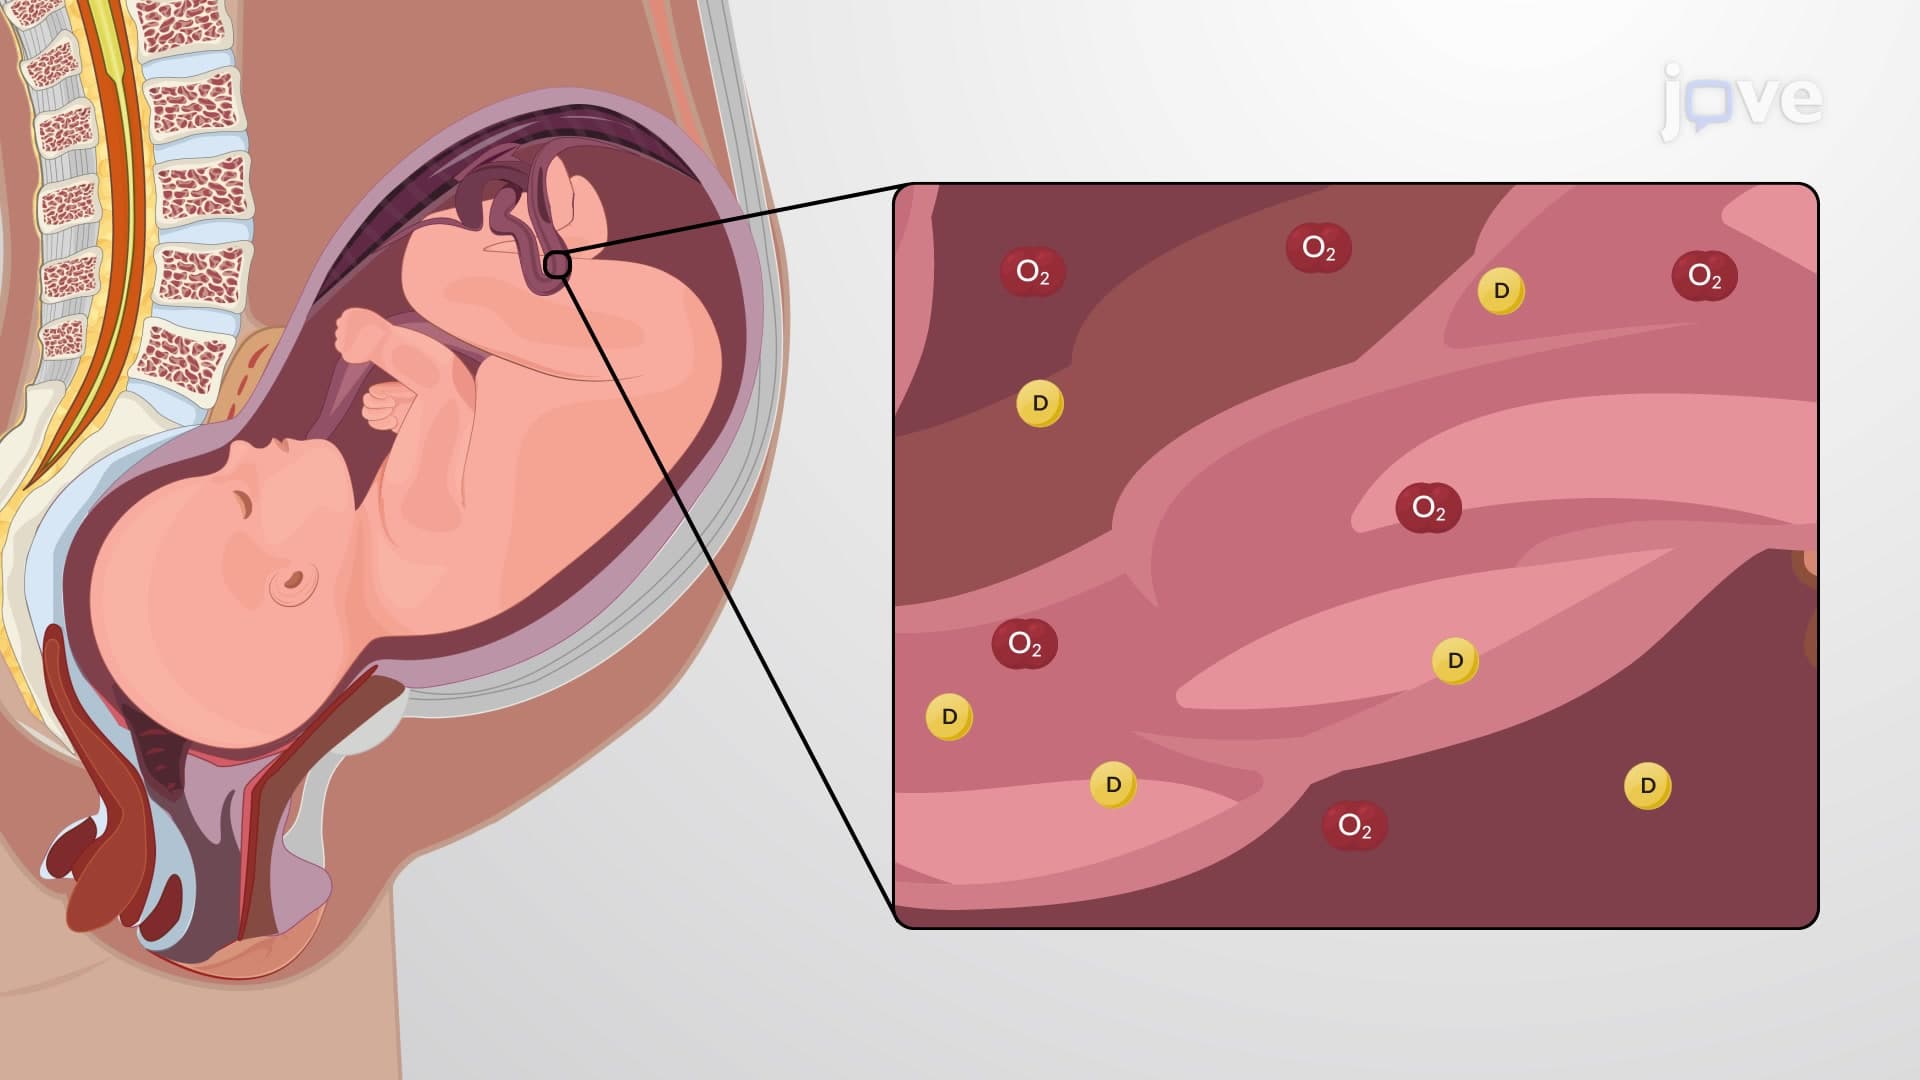
Factors Affecting Drug Response: Overview
 01:07
Teratogenicity
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism