A normal gastrointestinal motility excludes chronic intestinal pseudoobstruction in children
Related Experiment Video
Updated: Oct 17, 2026

A Mouse Model of Intestinal Partial Obstruction
Published on: March 5, 2018
S Cucchiara1, O Borrelli, G Salvia
1Department of Pediatrics, University of Naples Federico II, Italy.

Insights
Gastrointestinal manometry in children with suspected pseudoobstruction is useful only after excluding other conditions. Normal manometry findings, including migrating motor complexes, suggest reassessing the diagnosis.
Area of Science:
- Pediatric Gastroenterology
- Gastrointestinal Motility Disorders
- Diagnostic Imaging
Background:
- Gastrointestinal manometry is used for suspected enteric neuromuscular disorders.
- Performing manometry without prior extensive evaluation is not recommended.
Purpose of the Study:
- To evaluate the utility of gastrointestinal manometry in children with suspected chronic intestinal pseudoobstruction.
- To determine if manometric findings can exclude enteric neuromuscular disorders.
Main Methods:
- Gastrointestinal manometry performed using a perfused catheter for 5 hours fasting and 90 minutes post-feeding.
- Compared manometric data from 12 children with suspected pseudoobstruction to 8 age-matched controls.
Main Results:
- All patients and controls exhibited normal interdigestive and postprandial motor activity.
- No significant differences were found in motility indexes or coordination between patients and controls.
- Manometric findings did not support intestinal pseudoobstruction, leading to reassessment and alternative diagnoses.
Conclusions:
- Normal gastrointestinal manometry (migrating motor complexes, fed activity) in children excludes enteric neuromuscular disorders.
- Manometry findings suggesting pseudoobstruction should prompt reassessment of the diagnostic work-up.
- Extensive prior investigations are crucial to rule out mimic disorders before manometry.
Abstract:
Gastrointestinal manometry has gained wide acceptance in the approach to patients with suspected enteric neuromuscular disorders. However, performing gastrointestinal manometry in these subjects without a previous exhaustive diagnostic evaluation is unjustified. Twelve children (median age: 7.0 years; range: 8 months-13 years), with clinical and x-ray features suggesting chronic intestinal pseudoobstruction, were referred to our unit for gastrointestinal manometry. The latter was performed with a perfused catheter for 5 hr in the fasting state and for 90 min after feeding. Data were compared with those recorded in eight age-matched controls. In all patients and controls, interdigestive motor complexes with propagated phases III were detected; a regular postprandial antroduodenal motor activity was also recorded. Patients and controls did not differ for fed antral and duodenal motility indexes, fed antroduodenal coordination, and length of duodenal phase III. Most of the patients showed short or prolonged bursts of nonpropagated activity in the fasting and/or fed states; in four cases fasting and/or fed sustained phasic activity was recorded. Manometric evidence of migrating motor complexes and postfeeding activity did not support the diagnosis of intestinal pseudoobstruction and suggested redirecting the diagnostic evaluation. Final diagnoses were: Munchausen syndrome-by-proxy (four cases), celiac disease (two cases), intestinal malrotation (two cases), Crohn's disease (two cases), multiple food intolerance (one case), and congenital chloride-losing diarrhea (one case). It is concluded that in children with suspected chronic intestinal pseudoobstruction manometric evidence of migrating motor complexes and fed motor activity excludes an enteric neuromuscular disorder and suggests a reassessment of the diagnostic work-up. Furthermore, if gastrointestinal manometry shows migrating motor complexes and postfeeding motor activity, qualitative abnormalities of the manometric tracings do not indicate an underlying enteric neuromuscular disorder and must not be overemphasized. Patients referred for gastrointestinal manometry should previously undergo an extensive diagnostic investigation to exclude disorders mimicking chronic intestinal pseudoobstruction.
Related Concept Videos
 01:20
Gastrointestinal Motility Disorders
 01:29
Intestinal Obstruction I: Introduction
 01:07
Intestinal Obstruction II: Pathophysiology
 01:11
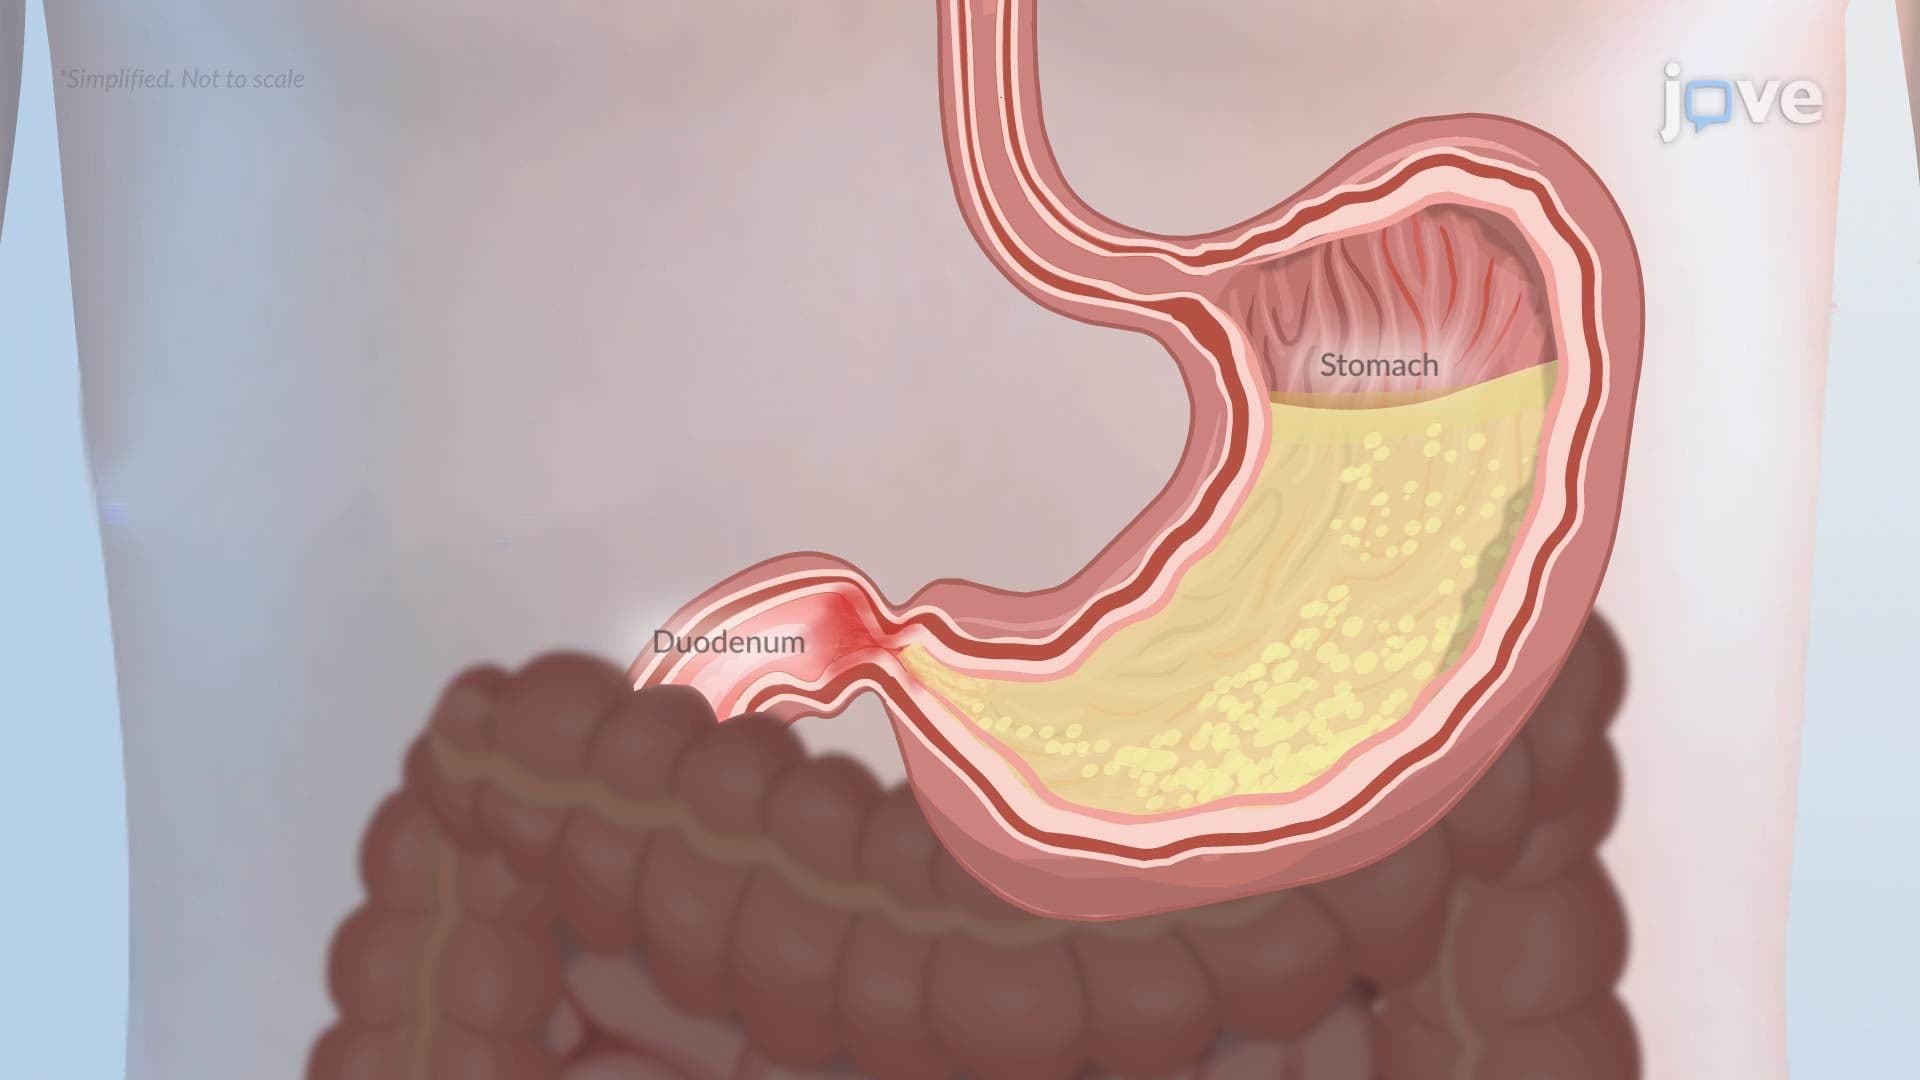
Pyloric Obstruction
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and solid...
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...