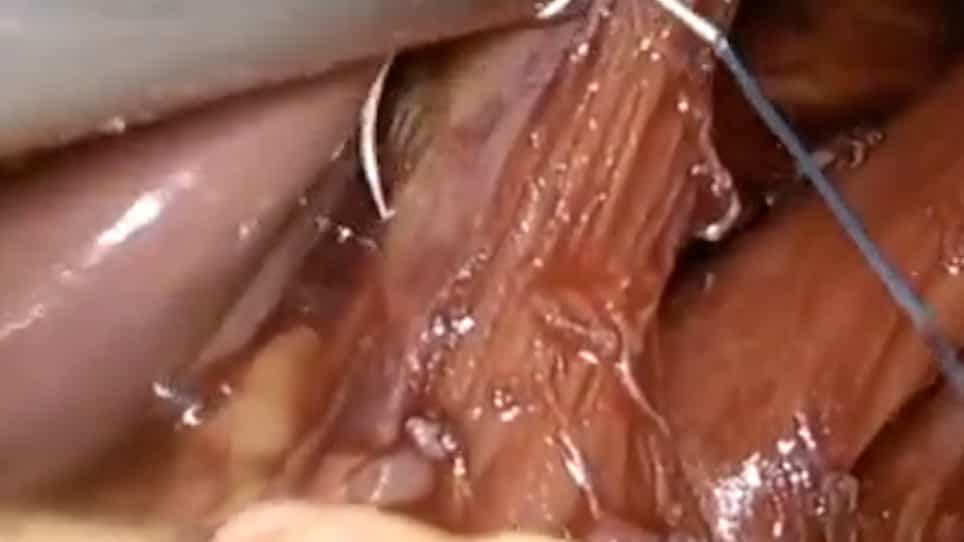
Perforation of gastric ulcer associated with paraesophageal hernia causing diffuse peritonitis

S Rakic1, R J Hissink, B W Schiff

  • 1Department of Surgery, Twenteborg Hospital, Almelo, The Netherlands.

Digestive Surgery
|March 18, 2000
PubMed
Abstract

Related Concept Videos

Esophageal Perforation-I: Introduction01:22

Esophageal Perforation-I: Introduction

Esophageal perforation is a severe medical condition characterized by a breach in the integrity of the esophageal wall. This breach can occur due to various factors such as trauma, medical procedures, or underlying diseases. When the esophageal wall is compromised, it allows food, fluids, and digestive juices into the chest cavity or adjacent structures, leading to potential complications and health risks.
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
Esophageal Perforation-II: Clinical Manifestations and Management01:28

Esophageal Perforation-II: Clinical Manifestations and Management

Esophageal perforations manifest in various clinical forms, influenced by factors such as the perforation's cause and location (cervical, intrathoracic, or intra-abdominal), the extent of contamination, and potential injury to adjacent mediastinal structures. The timing between the perforation occurrence and treatment initiation also affects the clinical presentation.
Clinical Manifestations:
Peptic Ulcer01:27

Peptic Ulcer

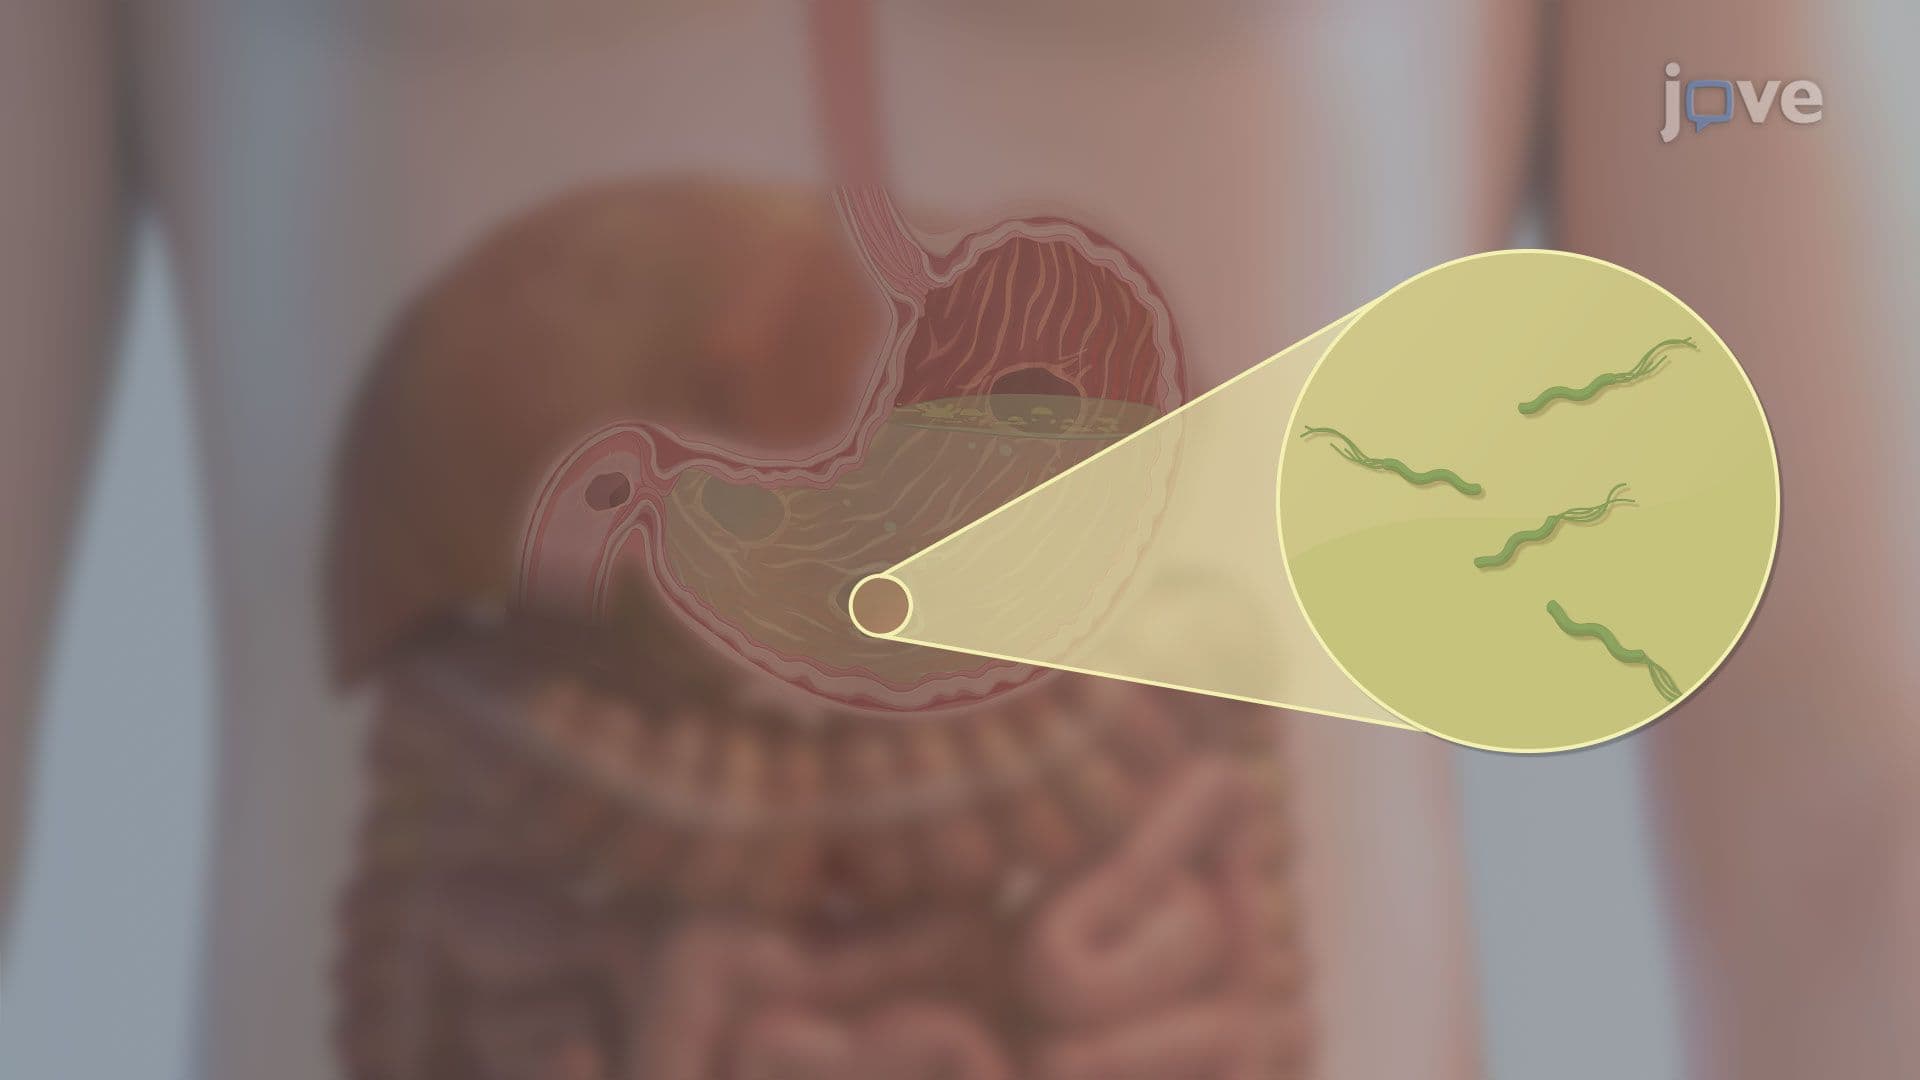
Peptic ulcers are erosive lesions of the gastric or duodenal lining, most commonly caused by Helicobacter pylori infection. This Gram-negative, helical bacterium has adapted to survive the stomach’s acidic environment by producing urease, which converts urea into ammonia and carbon dioxide. The ammonia neutralizes gastric acid in the bacterium’s immediate environment, allowing colonization of the gastric mucosa. H. pylori attaches to mucus-secreting epithelial cells, penetrates the mucus...
Hiatal Hernia01:25

Hiatal Hernia

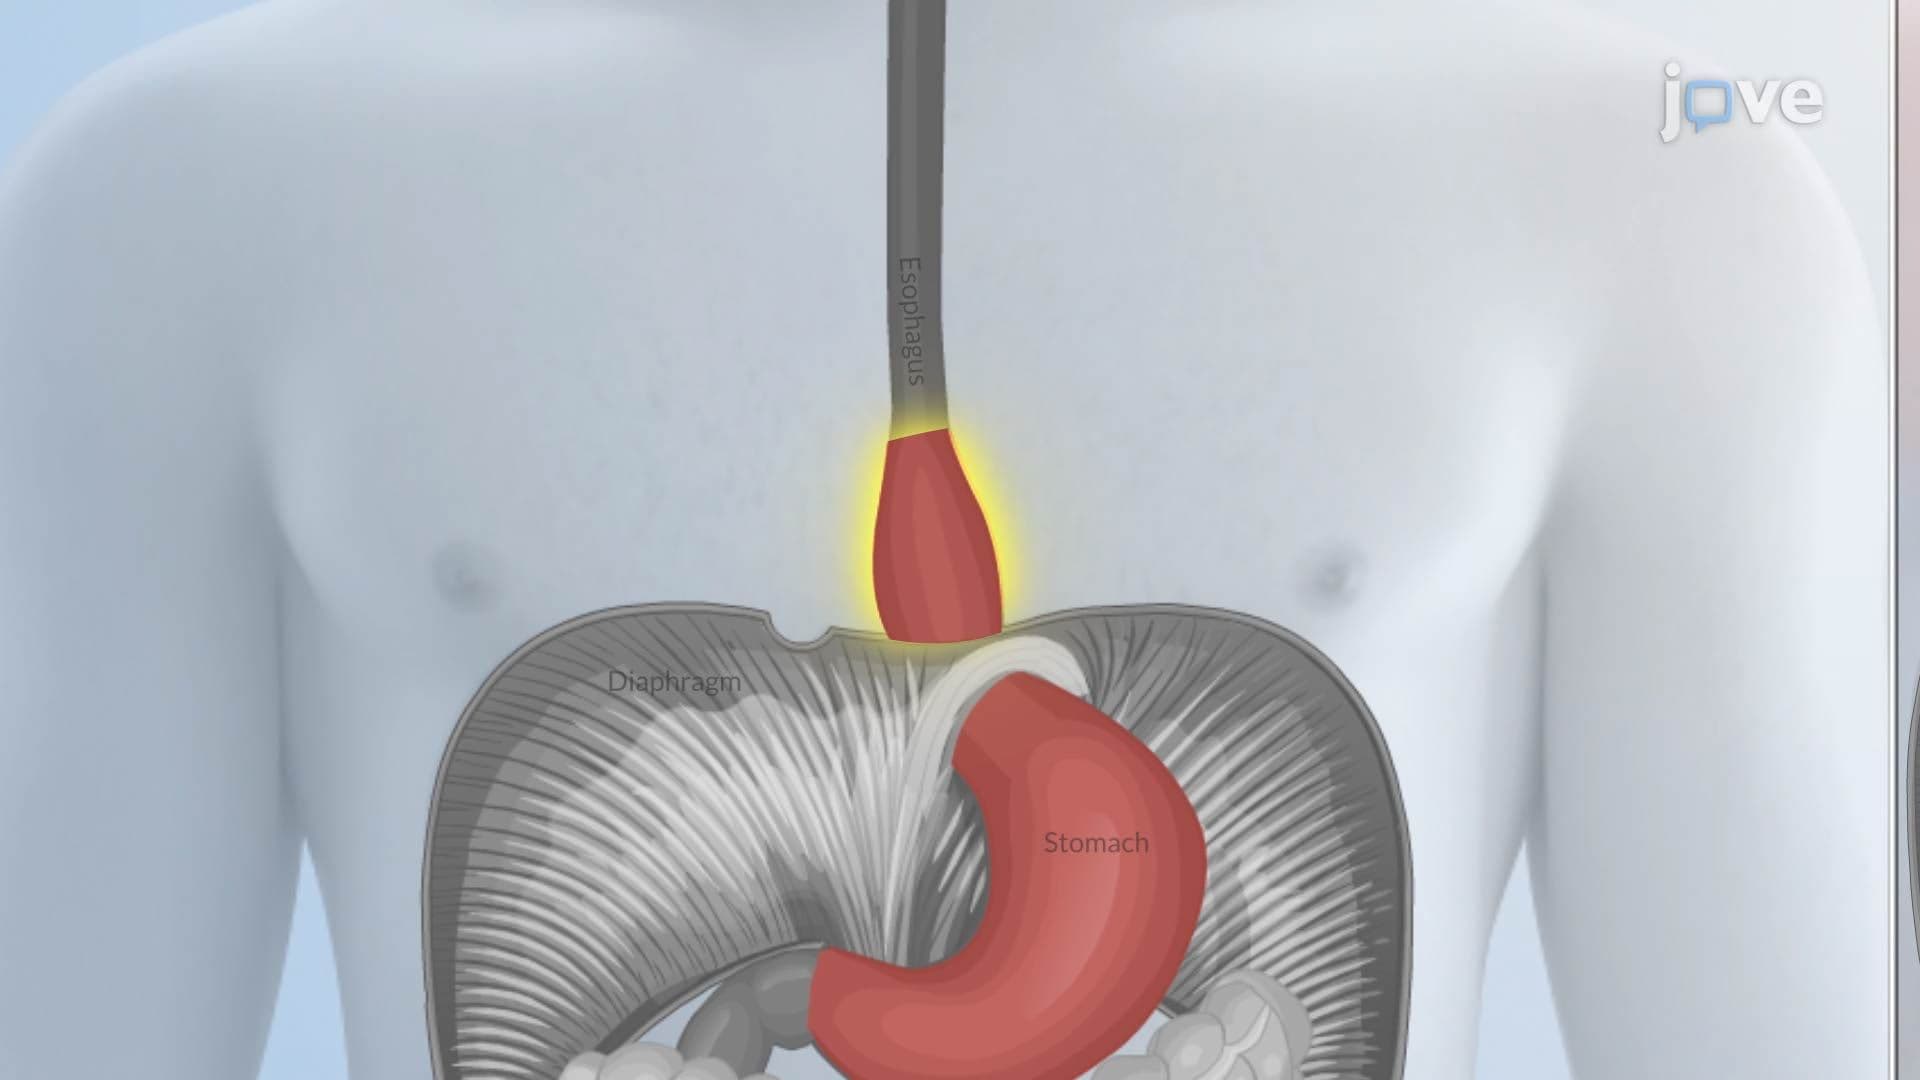
A hiatal hernia is the abnormal protrusion of the stomach or other abdominal organs through the esophageal hiatus of the diaphragm into the thoracic cavity.Normally, the gastroesophageal junction (GEJ) lies below the diaphragm and is supported by the phrenoesophageal membrane, the diaphragmatic crura, and connective tissues. Weakening of these structures—due to aging, congenital defects like a short esophagus, or increased intra-abdominal pressure from coughing, obesity, pregnancy, or heavy...
Gastritis II: Pathophysiology01:26

Gastritis II: Pathophysiology

The pathophysiology of gastritis begins with the colonization of the stomach lining by Helicobacter pylori (H. pylori). This bacterium spreads mainly via the oral-oral route through saliva or shared utensils, and can also be transmitted in overcrowded or unhygienic environments through contaminated water, despite its brief survival outside the body.ColonizationOnce ingested, H. pylori enters the stomach and begins colonization by navigating through the mucus layer lining the stomach wall. It...
Peptic Ulcer Disease I: Introduction01:25

Peptic Ulcer Disease I: Introduction

Peptic ulcer disease (PUD) involves breaks in the gastrointestinal tract's mucosal lining, primarily in the stomach and duodenum, with less frequent occurrences in the lower esophagus or near the pylorus.Ulcers can be acute or chronic. Acute ulcers are short-lived with minimal inflammation and heal quickly after the irritant is removed. Chronic ulcers persist, may recur, and often cause scarring due to ongoing tissue damage. Superficial erosions affect only the mucosal layer and are called...