Related Experiment Video
Updated: Aug 11, 2026
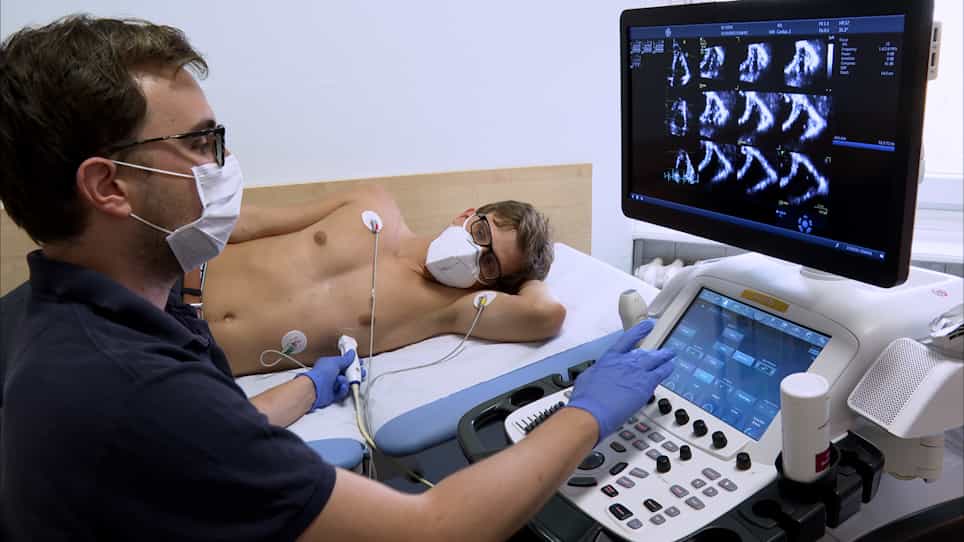

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Follow-up of patients with arrhythmogenic right ventricular cardiomyopathy dysplasia
M J Munclinger1, J J Patel, A S Mitha
1Cardiac Unit, Wentworth Hospital, Durban.

Insights
Arrhythmogenic right ventricular cardiomyopathy/dysplasia (ARVC/D) affects all races and can be familial. Early diagnosis is crucial as it is often missed, impacting patient outcomes and management strategies.
Area of Science:
- Cardiology
- Genetics
- Electrophysiology
Background:
- Arrhythmogenic right ventricular cardiomyopathy/dysplasia (ARVC/D) is a significant cause of ventricular arrhythmias.
- Accurate diagnosis and timely management are critical for improving patient prognosis.
Purpose of the Study:
- To enlarge data on the natural course and management of patients diagnosed with ARVC/D.
- To highlight the diagnostic challenges and outcomes associated with ARVC/D.
Main Methods:
- A retrospective and partly prospective observational study was conducted.
- Included patients with ARVC/D diagnosed by multiple criteria and their family members.
- Analyzed diagnosis, management, morbidity, and mortality over a 6-year period.
Main Results:
- Twelve patients were diagnosed with ARVC/D.
- Follow-up revealed 7 patients well on medication, 2 asymptomatic, and 3 deaths (25% mortality rate).
- ARVC/D occurred in all racial groups and was familial in 42%; diagnosis was often missed by referring physicians.
Conclusions:
- ARVC/D should be considered in the differential diagnosis for unexplained syncope, palpitations, or ventricular tachycardia.
- Management of ARVC/D presents complex challenges with variable outcomes.
Objective:
The enlargement of data on the natural course and management of patients with arrhythmogenic right ventricular cardiomyopathy/dysplasia (ARVC/D).
Design:
Retrospective and partly prospective observational study.
Setting:
Cardiac Unit, Wentworth Hospital, Durban--the only unit in KwaZulu-Natal providing an arrhythmia and electrophysiology service.
Study Population:
Those included were: (i) patients referred for palpitations, unexplained syncope, or ventricular tachycardia and in whom ARVC/D was diagnosed according to multiple criteria; and (ii) family members of patients with ARVC/D in whom the disease was documented using the same criteria.
Main Outcome And Measurements:
Diagnosis, management, morbidity and mortality were analysed.
Results:
Twelve patients were diagnosed with ARVC/D over a period or 6 years. At the end of follow-up for 3.4 +/- 3.2 years, 7 of them were well and alive on anti-arrhythmic medication, 2 were asymptomatic, and 3 had died. One death was sudden, 1 patient died due to left ventricular failure, and 1 patient died due to a low cardiac output syndrome 3 months after right ventricular isolation, i.e. the mortality rate was 25%. ARVC/D was found in all racial groups and was familial in 5 patients (42%). In all but one patient the correct diagnosis was not suspected by the referring institution, physician or cardiologist.
Conclusions:
ARVC/D needs to be included into a differential diagnosis of unexplained syncope, palpitations, or ventricular tachycardia by all health service providers. Its management remains a complex challenge with varying results.
More Related Videos
 08:42
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
 09:36
Dual-Dye Optical Mapping of Hearts from RyR2R2474S Knock-In Mice of Catecholaminergic Polymorphic Ventricular Tachycardia
Published on: December 22, 2023
Related Concept Videos
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:25
Cardiomyopathy I: Introduction and Classification
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care