Related Experiment Video
Updated: Oct 17, 2026
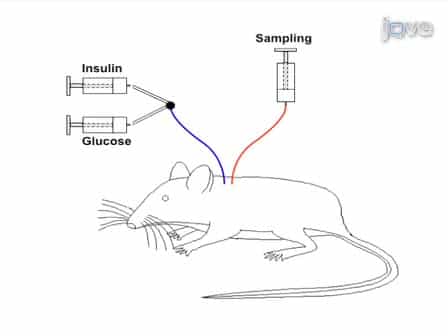
Hyperinsulinemic-Euglycemic Clamp in the Conscious Rat
Published on: February 7, 2011
Less of insulin desensitization in sympathetic nerve terminals from wistar rats with insulin resistance
1Department of Pharmacology, College of Medicine, National Cheng Kung University, 138 Sheng-Li Road, Tainan City, Taiwan.

Abstract:
In an attempt to determine the effect of hyperinsulinemia on sympathetic function, release of norepinephrine (NE) from isolated aorta by insulin was measured in Wistar rats with insulin resistance. Insulin resistance was produced when the hypoglycemic action of glibenclamide at a dose of 10 mg/kg was almost abolished in rats that received daily injections of long-acting insulin for 15 days. Moreover, the stimulatory effect of insulin on glucose uptake was markedly reduced in both skeletal muscle strips and white adipocytes obtained from these rats with insulin resistance. However, the stimulatory effects of insulin at concentrations from 5 to 15 U/l on the release of NE from the aortic strip of insulin-resistant rats were not modified in the same manner but only slightly reduced compared with that of normal rats. These results suggest that insulin desensitization was produced later in sympathetic nerve terminals than in other organs in insulin-resistant rats and this may be helpful to explain the sympathetic hyperactivity associated with diabetes in clinics.
More Related Videos

Related Concept Videos
 01:24
Type II Diabetes II: Pathophysiology
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are co-secreted in...
 01:26
Type II Diabetes I: Introduction
 01:26
Type I Diabetes II: Pathophysiology
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones