Related Experiment Video
Updated: Oct 17, 2026
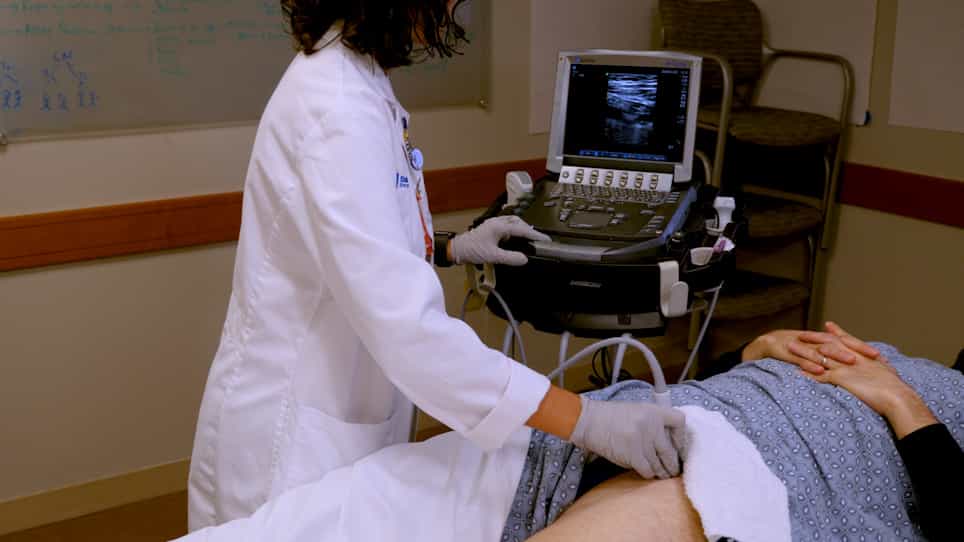
Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Deep venous thrombosis in the pediatric trauma population: an unusual event: report of three cases
O H Grandas1, M Klar, M H Goldman
1Department of Surgery, University of Tennessee Graduate School of Medicine, Knoxville, USA.

Insights
Deep venous thrombosis (DVT) is rare in pediatric trauma patients. Routine screening is not recommended unless patients have prolonged immobility, venous interventions, or symptoms, with hematologic evaluation for diagnosed cases.
Area of Science:
- Pediatric Medicine
- Trauma Surgery
- Hematology
Background:
- Deep venous thrombosis (DVT) incidence is lower in children than adults.
- Pediatric trauma patients share risk factors with adult trauma patients.
- Understanding DVT risk in pediatric trauma is crucial for appropriate management.
Observation:
- A review of 2746 pediatric trauma patients (1989-1997) identified only three cases of DVT.
- DVT occurred in adolescents, affecting upper and lower extremities.
- One patient had pulmonary embolism without confirmed DVT.
Findings:
- Identified risk factors included venous system manipulations (shunts, central lines, medical antishock trousers).
- Therapies involved anticoagulation (heparin, warfarin) and a vena cava filter in one case.
- No DVT was observed in patients with closed head or spinal cord injuries without additional risk factors.
Implications:
- The thrombotic risk in pediatric trauma patients is generally low.
- Routine DVT screening or prophylaxis is not indicated for all pediatric trauma patients.
- Targeted screening and hematologic evaluation are recommended for high-risk individuals and diagnosed cases.
Abstract:
The incidence of deep venous thrombosis (DVT) in the pediatric population has been reported to be lower than in adults. Pediatric trauma patients have predisposing risk factors for DVT similar to those in the general trauma population. We reviewed the records of 2746 children under 16 years of age admitted to our Level I pediatric trauma service from 1989 to 1997. Only three cases of DVT were documented, all adolescents. DVT was located in the upper (n = 1) and lower (n = 1) extremity venous system. One patient presented with pulmonary embolism alone without identifiable DVT. Risk factors found were venous system manipulations, including atriocaval shunt, subclavian central line, and hyperinflated medical antishock trousers garment. Therapy consisted of heparin followed by warfarin anticoagulation. A vena cava filter was inserted in one patient for whom systemic anticoagulation was contraindicated. No DVT was seen in 1123 closed head injury patients or 29 spinal cord injury patients without associated risk factors. The thrombotic risk in pediatric trauma patients is low. Routine screening or prophylaxis is not indicated except for patients who are likely to remain immobile for an extended period of time and require prolonged rehabilitation, have venous manipulations, or present with clinical symptoms. Hematologic evaluation in patients with diagnosed DVT is necessary to identify individual risk factors.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:30
Venous Thrombosis IV: Nursing Management
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:27
Pulmonary Embolism III: Nursing Management
 01:19
Pulmonary Embolism I: Introduction