Bile acids and progesterone metabolites in intrahepatic cholestasis of pregnancy
Related Experiment Video
Updated: Oct 17, 2026

The Use of Gas Chromatography to Analyze Compositional Changes of Fatty Acids in Rat Liver Tissue during Pregnancy
Published on: March 13, 2014
1Department of Medicine (Eastern Campus), and Institute of Biomedical Sciences, University of Chile, Hospital del Salvador, Santiago. htoreyes@reuna.cl

Abstract:
The pathogenesis of intrahepatic cholestasis of pregnancy (ICP) can be related to abnormalities in the metabolism and disposition of sex hormones and/or bile acids, determined by a genetic predisposition interacting with environmental factors. The total amount of oestrogens and progesterone circulating in the blood or excreted in the urine of ICP patients is similar to normal pregnancies. Thus, the search for the cause has been focused on abnormal hormone metabolites. The cholestatic potential of some D-ring oestrogen metabolites is supported by experimental and clinical data. Similar observations with regard to bile acids and progesterone metabolites are still scarce. This article reviews current knowledge in this field, including our own data. Bile acid synthesis appears to be reduced in patients with ICP, in whom primary conjugated bile acids are retained in blood. The major bile acid in blood and urine of these patients is cholic acid instead of chenodeoxycholic acid present in normal pregnancies. Hydroxylation and sulfation of bile acids are enhanced, while glucuronidation appears to be of lesser importance. The synthesis of progesterone appears unimpaired, while the profiles of progesterone metabolites in plasma and urine are different from normal pregnancies, with a larger proportion of mono- and disulfated metabolites, mainly 3alpha,5alpha isomers. Glucuronidated metabolites, however, are unchanged. With the administration of ursodeoxycholic acid (UDCA) to patients with ICP, pruritus and serum liver values are improved, the concentration of bile acids in blood is diminished and the proportion of their conjugated metabolites returned to normal. Simultaneously, the concentration of sulfated progesterone metabolites in blood and their urinary excretion are reduced. The serum levels of bile acids and progesterone metabolites before UDCA administration and their decrease during treatment do not correlate with each other. We propose that patients with ICP have a selective defect in the secretion of sulfated progesterone metabolites into bile and speculate that this may be caused by genetic polymorphism of canalicular transporter(s) for steroid sulfates or their regulation. Interaction with oestrogen metabolites and/or some exogenous compounds may further enhance the process triggering ICP in genetically predisposed individuals.

Related Concept Videos
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:28
Overview of Fatty Acid Metabolism
Fatty acids are catabolized in a process called beta-oxidation, which takes place in the matrix of the mitochondria and converts their fatty acid chains into two-carbon units of acetyl groups. The acetyl...
 01:19
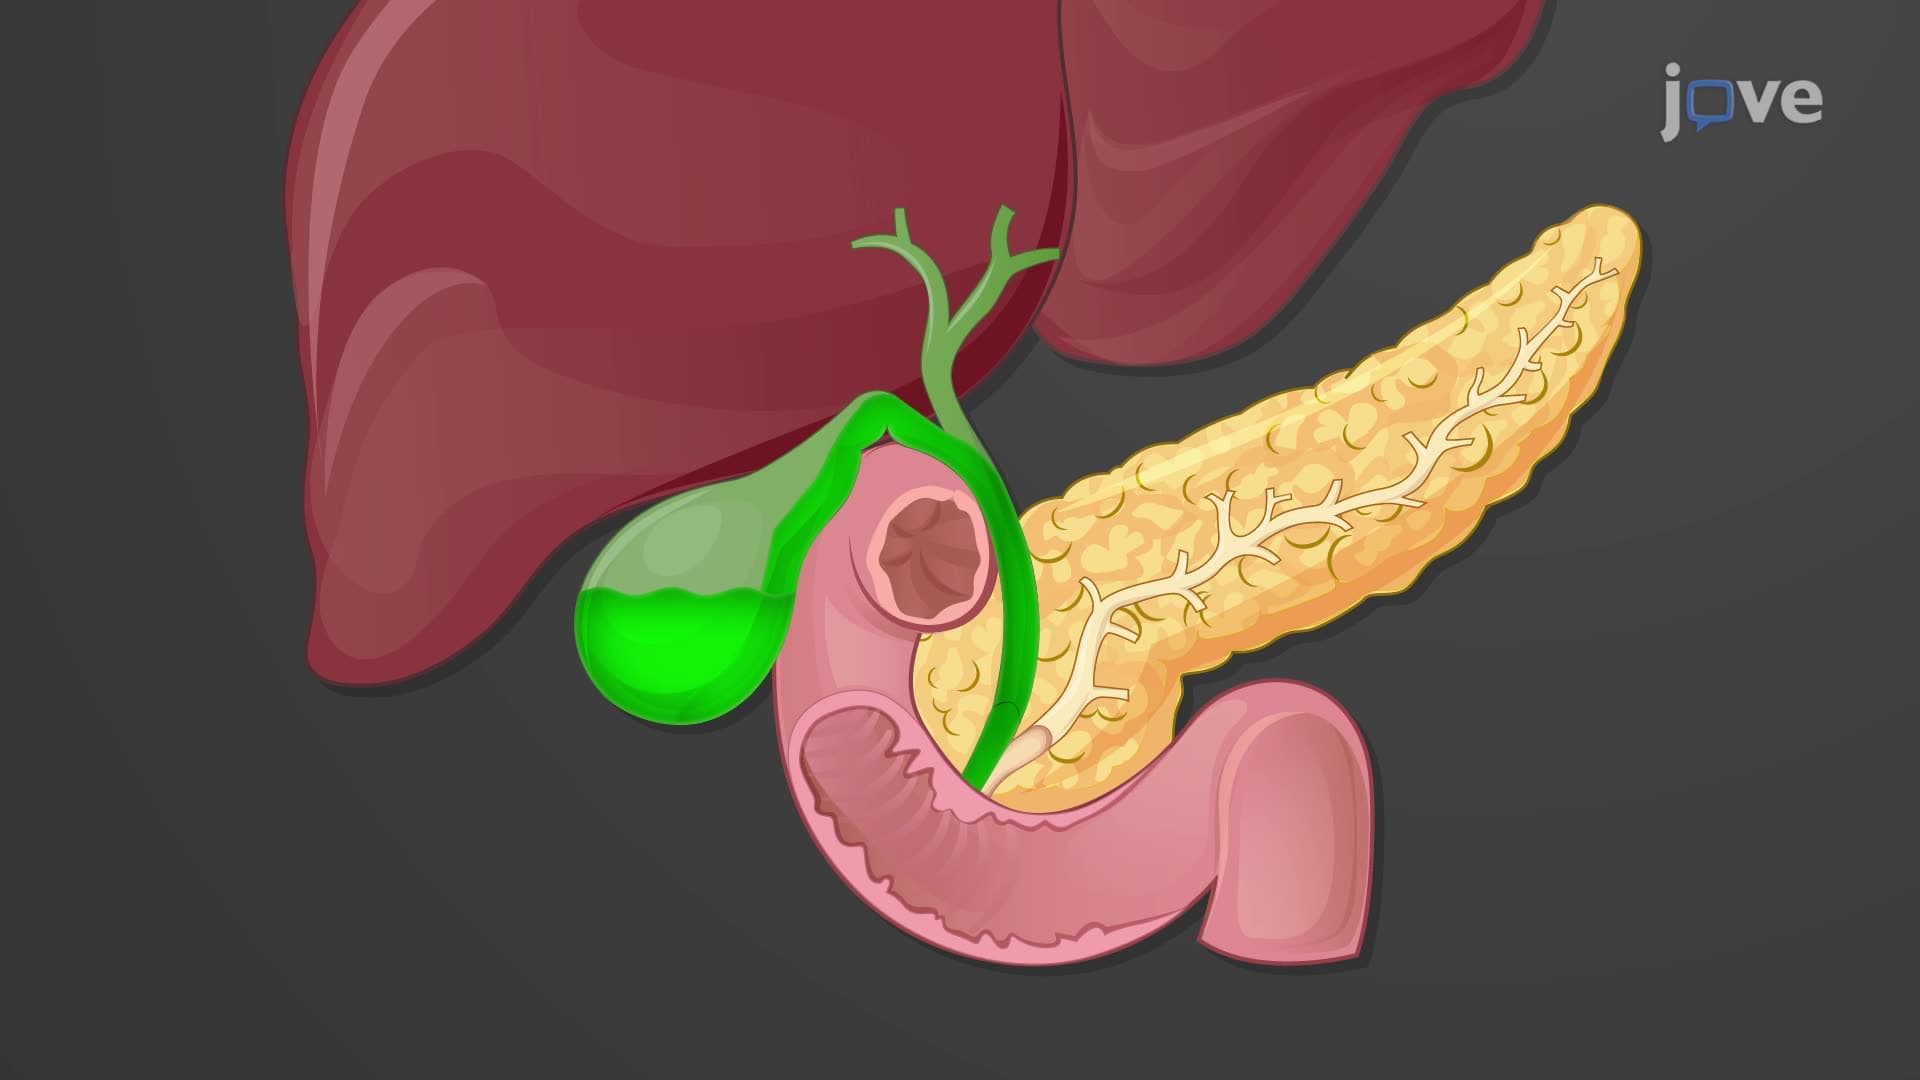
Bile
Bile is released when dietary fats enter...
 01:17
Hepatic Drug Excretion: Enterohepatic Cycling
Post-release drugs and metabolites can be reabsorbed into the body from the intestine. For conjugated metabolites like glucuronides, reabsorption requires enzymatic hydrolysis by intestinal microflora. This...
 01:29
Cholesterol: Significance and Regulation
Considering cholesterol and...
 01:20
Cholecystitis