Related Experiment Video
Updated: May 7, 2026
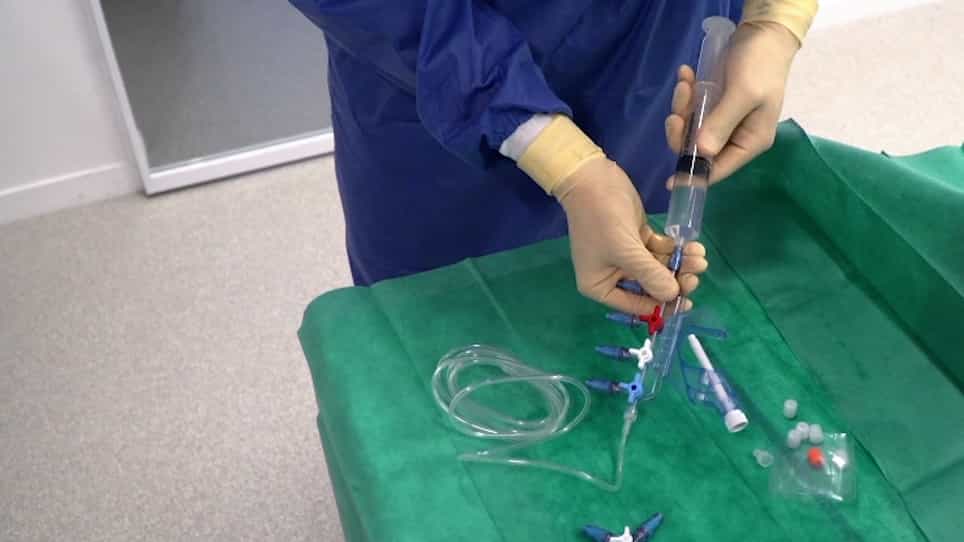
A Protocol to Set Up Needle-Free Connector with Positive Displacement on Central Venous Catheter in Intensive Care Unit
Published on: July 13, 2019
Education of physicians-in-training can decrease the risk for vascular catheter infection
R J Sherertz1, E W Ely, D M Westbrook
1North Carolina Baptist Hospital and Wake Forest University School of Medicine, Winston-Salem 27157, USA. sherertz@wfubmc.edu

Background:
Procedure instruction for physicians-in-training is usually nonstandardized. The authors observed that during insertion of central venous catheters (CVCs), few physicians used full-size sterile drapes (an intervention proven to reduce the risk for CVC-related infection).
Objective:
To improve standardization of infection control practices and techniques during invasive procedures.
Design:
Nonrandomized pre-post observational trial.
Setting:
Six intensive care units and one step-down unit at Wake Forest University Baptist Medical Center, Winston-Salem, North Carolina.
Participants:
Third-year medical students and physicians completing their first postgraduate year.
Intervention:
A 1-day course on infection control practices and procedures given in June 1996 and June 1997.
Measurements:
Surveys assessing physician attitudes toward use of sterile techniques during insertion of CVCs were administered during the baseline year and just before, immediately after, and 6 months after the first course. Preintervention and postintervention use of full-size sterile drapes was measured, and surveillance for vascular catheter-related infection was performed.
Results:
The perceived need for full-size sterile drapes was 22% in the year before the course and 73% 6 months after the course (P < 0.001). The perceived need for small sterile towels at the insertion site decreased reciprocally (P < 0.001). Documented use of full-size sterile drapes increased from 44% to 65% (P < 0.001). The rate of catheter-related infection decreased from 4.51 infections per 1000 patient-days before the first course to 2.92 infections per 1000 patient-days 18 months after the first course (average decrease, 3.23 infections per 1000 patient-days; P < 0.01). The estimated cost savings of this 28% decrease was at least $63000 and may have exceeded $800000.
Conclusions:
Standardization of infection control practices through a course is a cost-effective way to decrease related adverse outcomes. If these findings can be reproduced, this approach may serve as a model for physicians-in-training.

Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:27
Parentral Nutrition: Centeral and Peripheral Parental Nutrition
PN can be administered through two primary routes:
1. Central Parenteral Nutrition (CPN):
CPN involves delivering a high concentration of nutrients through a large vein. This is typically achieved using a Peripherally Inserted Central Catheter (PICC) or,...
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:26
Cardiac Catheterization IV: Nursing Management
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:29
Venous Thrombosis III: Interprofessional Care