Related Experiment Video
Updated: Jan 26, 2026

Real-Time Monitoring and Modulation of Blood Pressure in a Rabbit Model of Ischemic Stroke
Published on: February 10, 2023
Difference between office and ambulatory blood pressure or real white coat effect: does it matter in terms of
P Lantelme1, H Milon, M Vernet
1Service de Cardiologie, Hôpital de la Croix-Rousse, Lyon, France. lantelme@rockefeller.univ-lyon1.fr

Objective:
The blood pressure (BP) response to the doctor's visit, generally referred as the white coat (WC) response, is usually estimated by the difference between office BP (OBP) and ambulatory BP (ABP). The purpose of this study was to determine the validity of this estimation. To that end, we compared the real WC effect and the estimated WC effect (OBP-ABP) in terms of magnitude and consequences on target organs.
Design:
The study comprised 88 patients referred for hypertension. The real WC effect was measured using a Finapres device and expressed as the maximal WC effect (Max WC) or the average WC effect (Aver WC). For the estimation of target organ damages, the whole hypertensive group was separated into two groups according to the medians of the Aver WC, the Max WC, and the estimated WC effects, successively. Left ventricular mass index, E to A mitral wave ratio and pulse wave velocity were compared between groups as were serum creatinine, cholesterol and glucose levels.
Results:
The estimated WC effect proved to be a bad index of the real response to the doctor's visit as assessed by their difference of magnitude between the two (20 +/- 17, 12 +/- 12 and 30 +/- 14 mmHg as estimated WC, Aver WC and Max WC effects, respectively), their loose correlations (r=0.31, P=0.004 between estimated WC and Aver WC effects; r=0.27, P=0.01 between estimated WC and Max WC effects), and finally by the fact that they were in agreement in less than two-thirds of the patients for the categorization of the WC response. Concerning target organ damages, no difference in terms of cardiac mass, diastolic function, arterial distensibility, renal function and cardiovascular risk profile could be discerned between the groups with a high and a low WC effect, either real or estimated, when age and ABP were taken into account.
Conclusion:
The present work supports the view that the true WC effect and its estimation are not equivalent. However, the way in which the WC response is defined does not alter its effect on target organs or cardiovascular risk profile.


Related Concept Videos
 01:24
Blood Pressure
 01:30
Blood Pressure
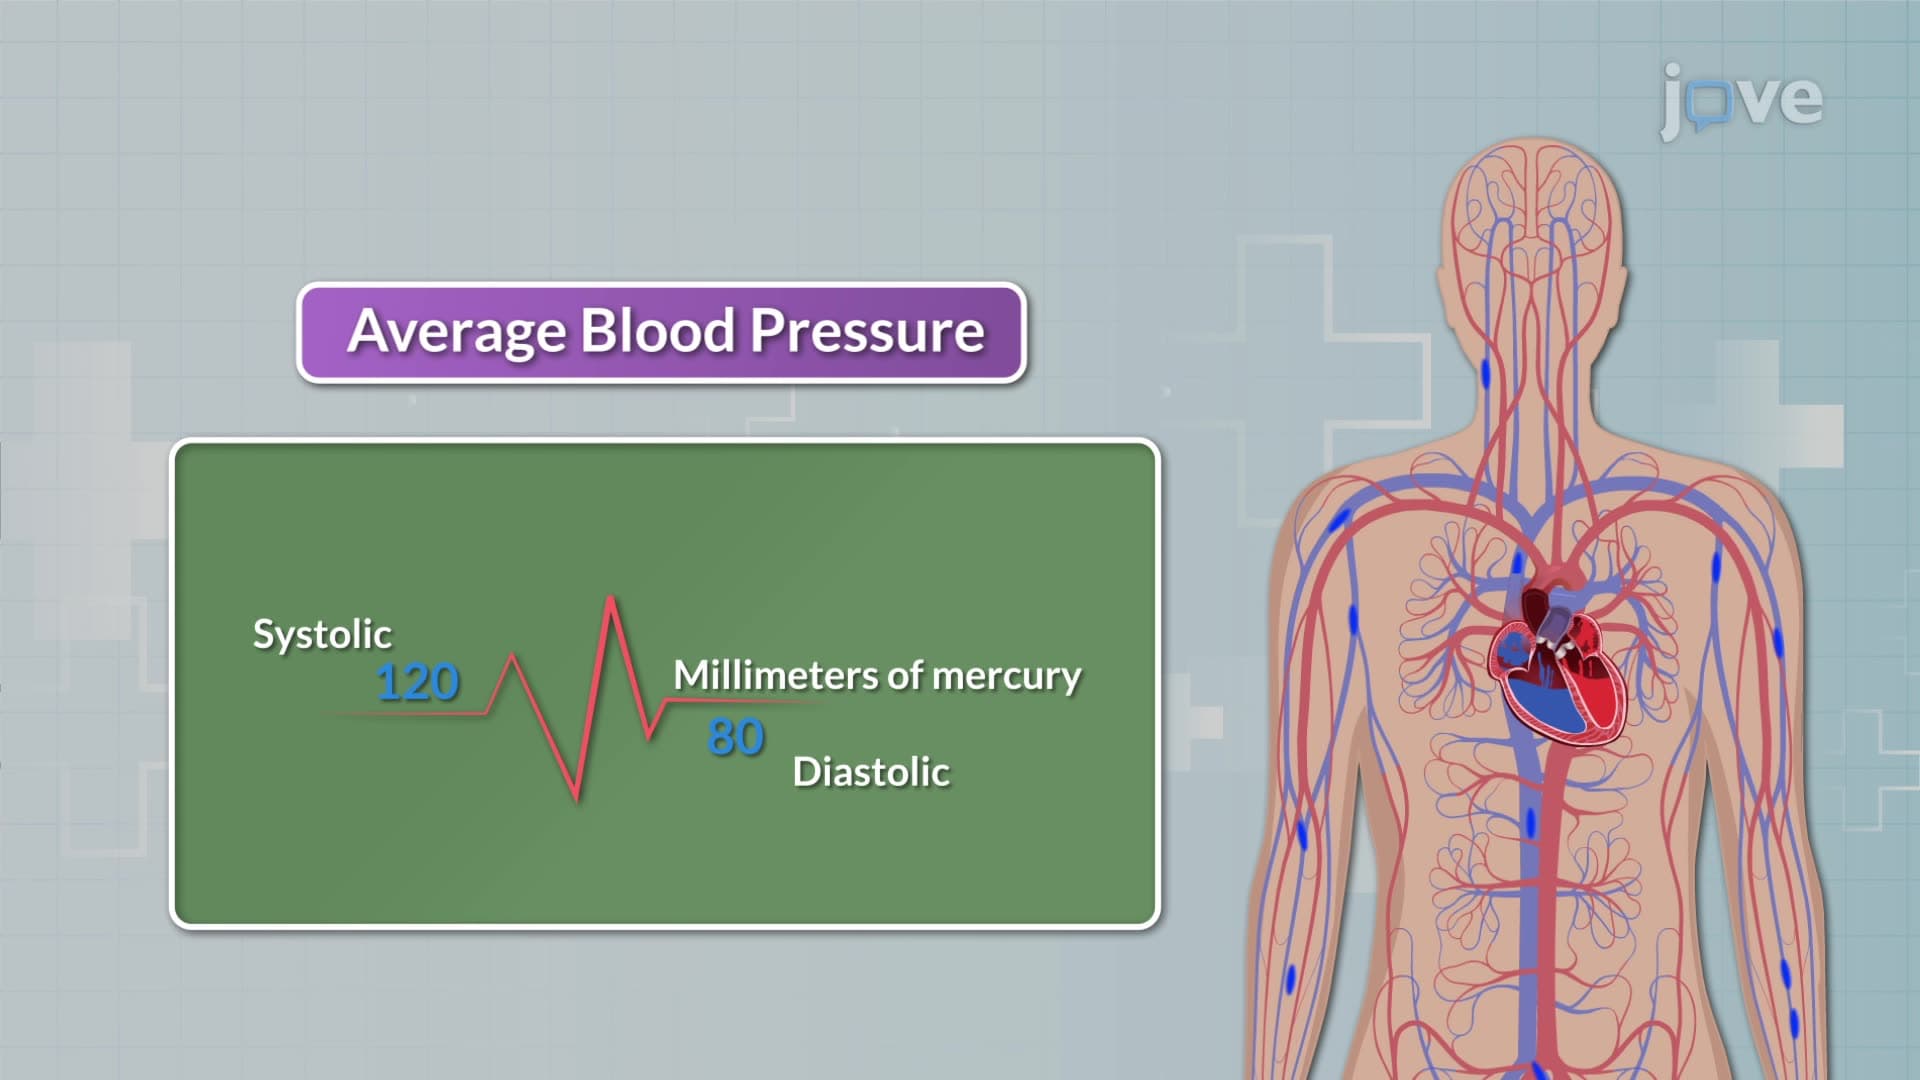
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 02:49
Classifying Matter by State
 01:17
Measurement of Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...