Related Experiment Videos
Intravenous indomethacin for preventing mortality and morbidity in very low birth weight infants
1Child Health, University of Dundee, Ninewells Hospital and Medical School, Dundee, Tayside, UK, DD1 9SY.

Insights
Prophylactic intravenous indomethacin significantly reduces symptomatic patent ductus arteriosus and severe intraventricular hemorrhage in premature infants. While trends suggest reduced mortality, further research is needed to confirm long-term effects.
Area of Science:
- Neonatal Medicine
- Pharmacology
- Clinical Trials
Background:
- Premature infants (<1750g) face risks of patent ductus arteriosus and intraventricular hemorrhage.
- Indomethacin is a potential prophylactic treatment for these neonatal conditions.
Purpose of the Study:
- To review the effectiveness of prophylactic intravenous indomethacin.
- To assess its impact on mortality and morbidity in low birth weight infants.
Main Methods:
- Systematic literature search (1980-1997) of Medline, Embase, and Oxford Database of Perinatal Trials.
- Inclusion of randomized controlled trials in infants <1751g birth weight.
- Meta-analysis of extracted outcome data.
Main Results:
- Significant reduction in symptomatic patent ductus arteriosus (RR 0.35) and severe intraventricular hemorrhage (Grade 3/4, RR 0.60).
- Trend towards reduced neonatal mortality (RR 0.85), but not statistically significant.
- No significant impact on respiratory outcomes; potential transient renal function impairment and increased necrotizing enterocolitis noted.
Conclusions:
- Prophylactic indomethacin offers immediate benefits by reducing PDA and severe IVH.
- No current evidence of long-term harm, but further trials are necessary.
- More research is required to fully understand both beneficial and harmful effects.
Background:
This section is under preparation and will be included in the next issue.
Objectives:
Indomethacin is used to treat symptomatic patent ductus arteriosus and may prevent or limit intraventricular haemorrhage in the neonatal period. This review examines the effectiveness of prophylactic intravenous indomethacin in reducing the mortality and morbidity associated with these conditions in infants weighing less than 1750 grams at birth.
Search Strategy:
A literature search from January 1980 to October 1994 was made in three computerised data bases: Medline; Embase; and the Oxford Database of Perinatal Trials. The search was updated in February 1997.
Selection Criteria:
Strict selection criteria were applied to clinical trials: the population had to be newborn infants of birth weight < 1751 grams; the intervention had to be prophylactic intravenous indomethacin; the trial had to be randomised and controlled; and at least one of several prespecified outcomes had to be reported in the results.
Data Collection And Analysis:
The methodological quality of each study was assessed using explicit criteria. Data on relevant outcome measures were extracted on two separate occasions and, where appropriate, the results of individual trials were combined using meta-analysis techniques to provide a pooled estimate of effect.
Main Results:
There is a trend towards reduced neonatal mortality in infants receiving prophylactic indomethacin, pooled relative risk (RR) = 0. 85 [95% CI 0.66 to 1.09]. The incidence of symptomatic patent ductus arteriosus is significantly reduced in treated infants, pooled RR = 0.35 [0.26 to 0.47] but there is no evidence that treatment affects respiratory outcomes. Prophylactic indomethacin significantly reduces the incidence of Grade 3 and 4 intraventricular haemorrhage in treated infants, pooled RR = 0.60 [0.43 to 0.83]. There is no evidence to suggest prophylactic indomethacin is associated with any long term adverse effect although there is a trend in treated infants towards an increased incidence of necrotizing enterocolitis, and some evidence that treatment may transiently impair renal function. There is no evidence that haemostasis is disturbed.
Reviewer'S Conclusions:
Prophylactic treatment with indomethacin has a number of immediate benefits, in particular a reduction in symptomatic patent ductus arteriosus and severe intraventricular haemorrhage. There is no evidence at present of long-term harm. Further trials are needed to assess more precisely the effects, both beneficial and harmful, on short and long-term outcomes.
Related Concept Videos
 01:24
Parenteral Anesthetics: Overview
 01:29
Drug Dosing: Infants and Children
 01:24
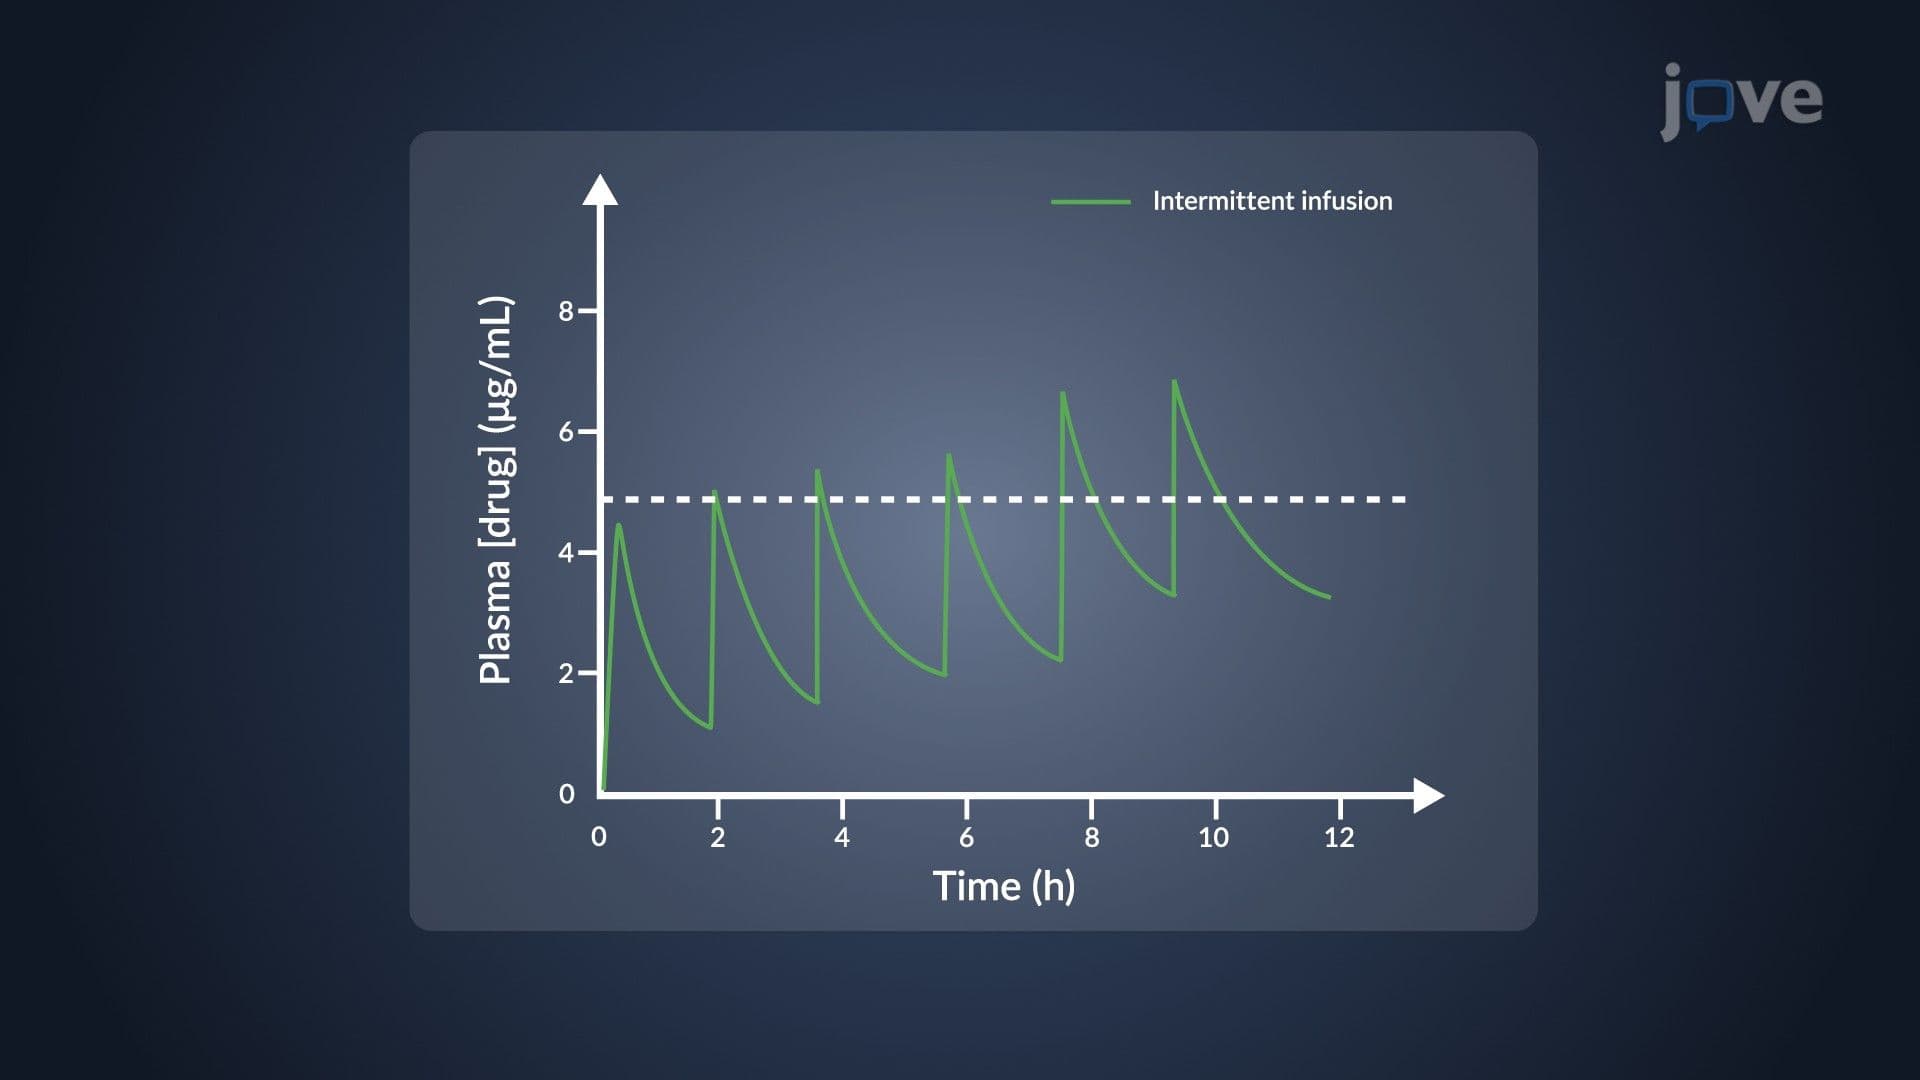
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins