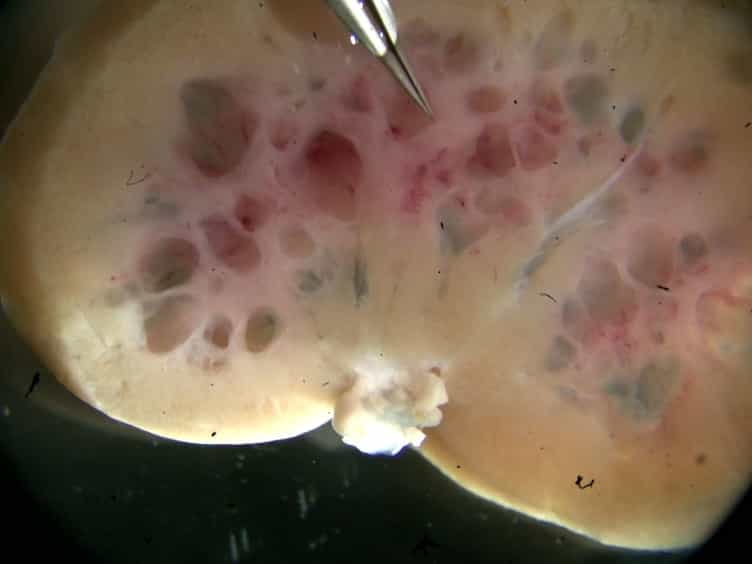
[Hypokalemic pareses secondary to renal tubular acidosis]

L G Gøransson1, T Apeland, R Omdal

  • 1Medisinsk avdeling Sentralsjukehuset i Rogaland, Stavanger.

Related Concept Videos

Antihypertensive Drugs: Potassium-Sparing Diuretics01:28

Antihypertensive Drugs: Potassium-Sparing Diuretics
Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...
Diabetic Ketoacidosis ll: Pathophysiology01:22

Diabetic Ketoacidosis ll: Pathophysiology

Diabetic ketoacidosis (DKA) is a metabolic emergency characterized by hyperglycemia, ketonemia, and metabolic acidosis. It results from severe insulin deficiency and an excess of counterregulatory hormones, leading to uncontrolled lipolysis, ketogenesis, and widespread electrolyte and fluid disturbances.Pathophysiology The central event in DKA is a profound loss of insulin action. Without insulin, glucose uptake in insulin-dependent tissues is impaired, while hepatic glucose production...
Chronic Kidney Disease II: Clinical Manifestations01:24

Chronic Kidney Disease II: Clinical Manifestations
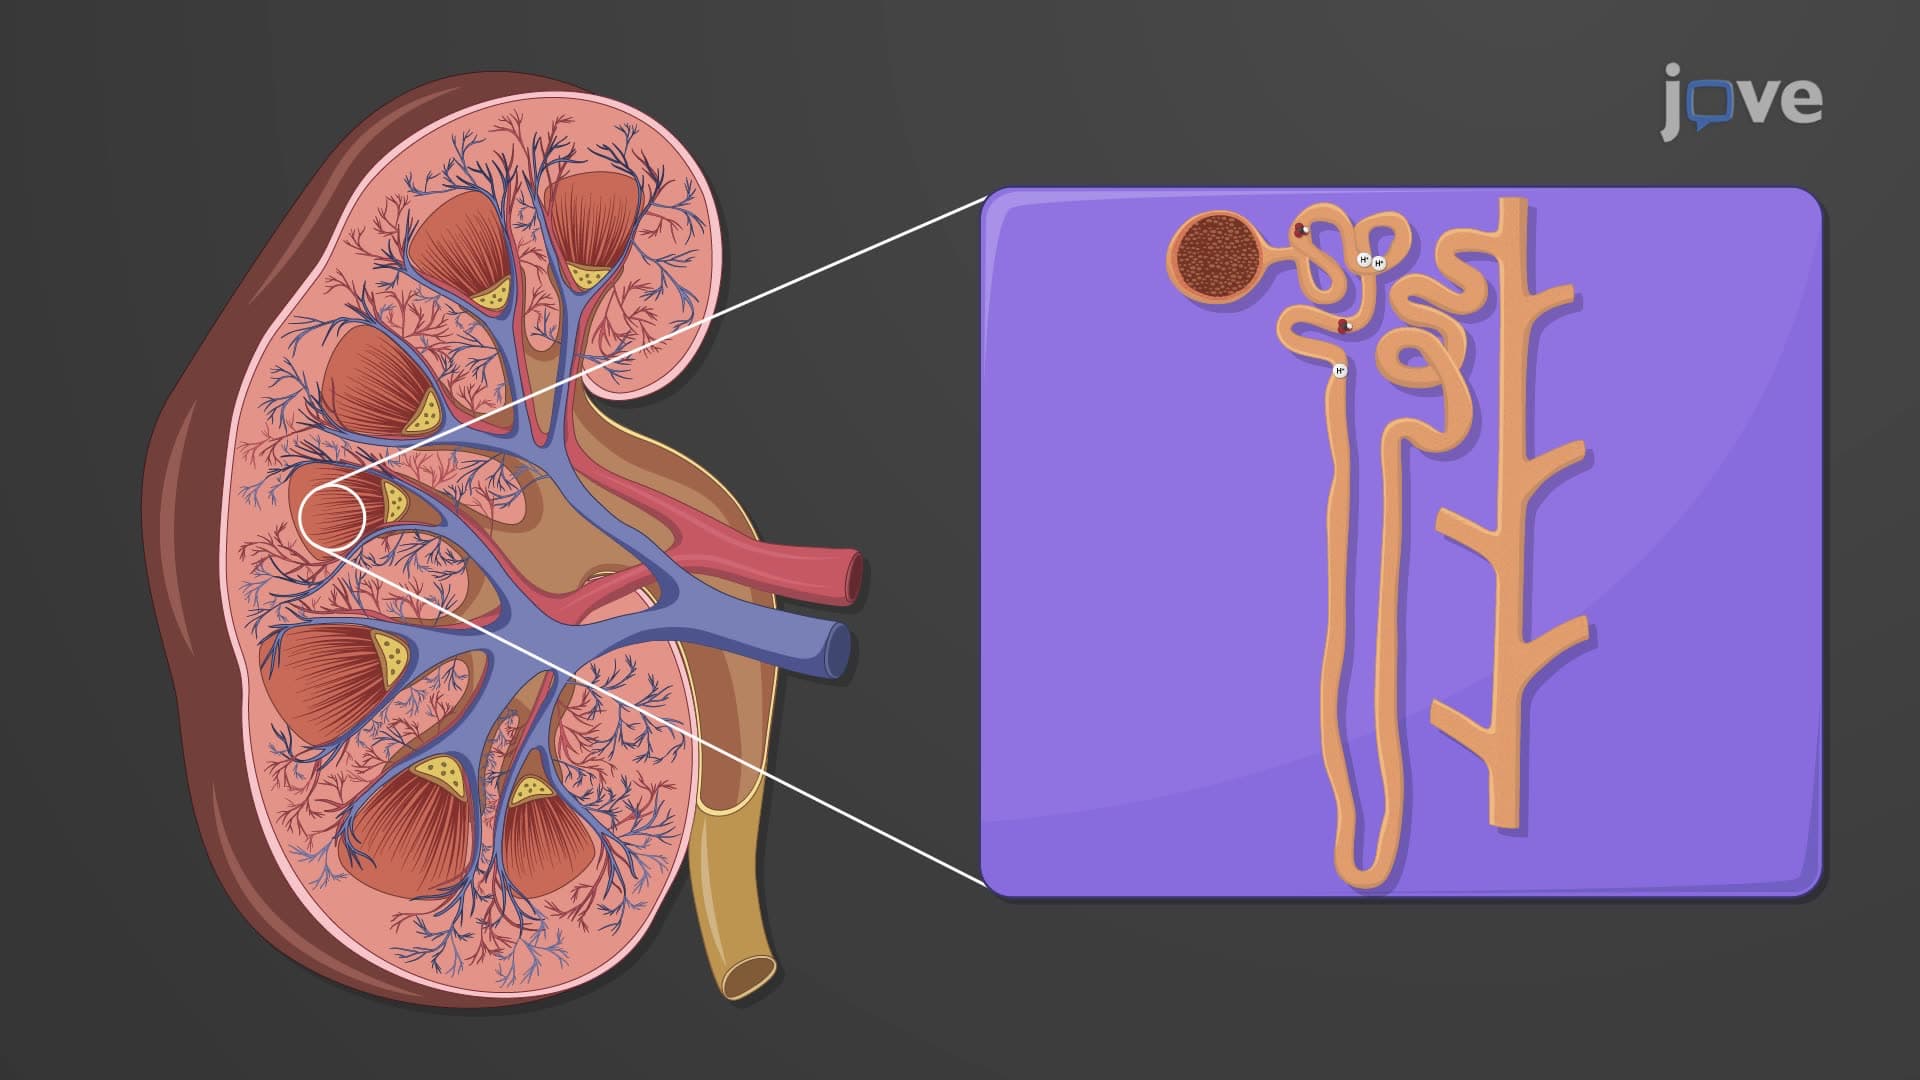
Chronic Kidney Disease (CKD) progressively impairs multiple body systems due to the accumulation of uremic toxins, which disrupt cellular functions across various organs.Neurologic symptomsNeurologic symptoms often arise early in CKD, as uremic toxin buildup drives changes in cognitive and motor functions. Patients frequently experience fatigue, headache, confusion, difficulty concentrating, and, in severe cases, seizures. Peripheral neuropathy commonly manifests as burning sensations in the...
Renal Regulation of Acid-Base Balance01:29

Renal Regulation of Acid-Base Balance

Metabolic reactions in the body produce nonvolatile acids, such as sulfuric acid, which generate an acid load of approximately 1 mEq of H+ per kilogram of body weight daily. Excreting H+ in the urine is essential to balance this acid load.
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...

Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology
Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...
Diabetic Ketoacidosis l: Introduction01:25

Diabetic Ketoacidosis l: Introduction

DefinitionDiabetic ketoacidosis (DKA) is an acute, life-threatening complication of diabetes mellitus, characterized by a triad of hyperglycemia (blood glucose >250 mg/dL), ketonemia or ketonuria, and metabolic acidosis (arterial pH <7.30 and serum bicarbonate <18 mEq/L). It results from insulin deficiency combined with elevated levels of counterregulatory hormones—glucagon, catecholamines, cortisol, and growth hormone—leading to increased lipolysis, hepatic ketone production, and...