Related Experiment Video
Updated: Jul 29, 2026


Noninvasive Determination of Vortex Formation Time Using Transesophageal Echocardiography During Cardiac Surgery
Published on: November 28, 2018
The hospital volume-outcome relationship in general thoracic surgery. Is the surgeon the critical determinant?
1Department of Thoracic Surgical Oncology, Roswell Park Cancer Institute, Buffalo, New York, USA. urschelj@fhs.mcmaster.ca

Background:
Complex operations, such as those performed in thoracic surgery, have a hospital volume-outcome relationship. It is difficult to isolate the effect of the surgeon in this relationship since experienced thoracic surgeons tend to practice in high-volume tertiary care hospitals. An American comprehensive cancer hospital created a community outreach satellite program in thoracic surgery, and this provided a unique opportunity to study the hospital volume-outcome relationship without the confounding variable of surgeon experience.
Methods:
A retrospective review of thoracic surgical operations done over a 4-year period at a small community hospital, by a tertiary care hospital surgeon, was conducted. Operative mortality was the major outcome measure. Two high complexity operations (pneumonectomy and esophagectomy) were specifically scrutinized.
Results:
486 thoracic surgical procedures (317 minor and 169 major cases) were done. There was one in-hospital death (aspiration pneumonia after esophageal stenting) and one 30-day mortality (readmission for cerebral vascular accident after lobectomy). Data,for the 10 esophagectomy patients is as follows: age - 66+/-13 years; length of stay - 12.8+/-3.4 days; anastomotic leaks - 0; operative mortality - 0. Data for the 6 pneumonectomy patients is as follows: age - 69+/-8 years; length of stay - 8.5+/-5.2 days; preoperative FEV1 - 1.6+/-0.3 litres; fistulas or empyema - 0; operative mortality - 0.
Conclusions:
Despite having a very low volume of thoracic surgical cases the community hospital had crude outcomes comparable to those reported from high volume tertiary hospitals. This suggests that the surgeon may be a more important factor in the hospital volume-outcome relationship than previously thought. Nevertheless, complex thoracic surgical operations are ideally performed by an experienced surgeon, and in a high volume hospital


Related Concept Videos
 01:15
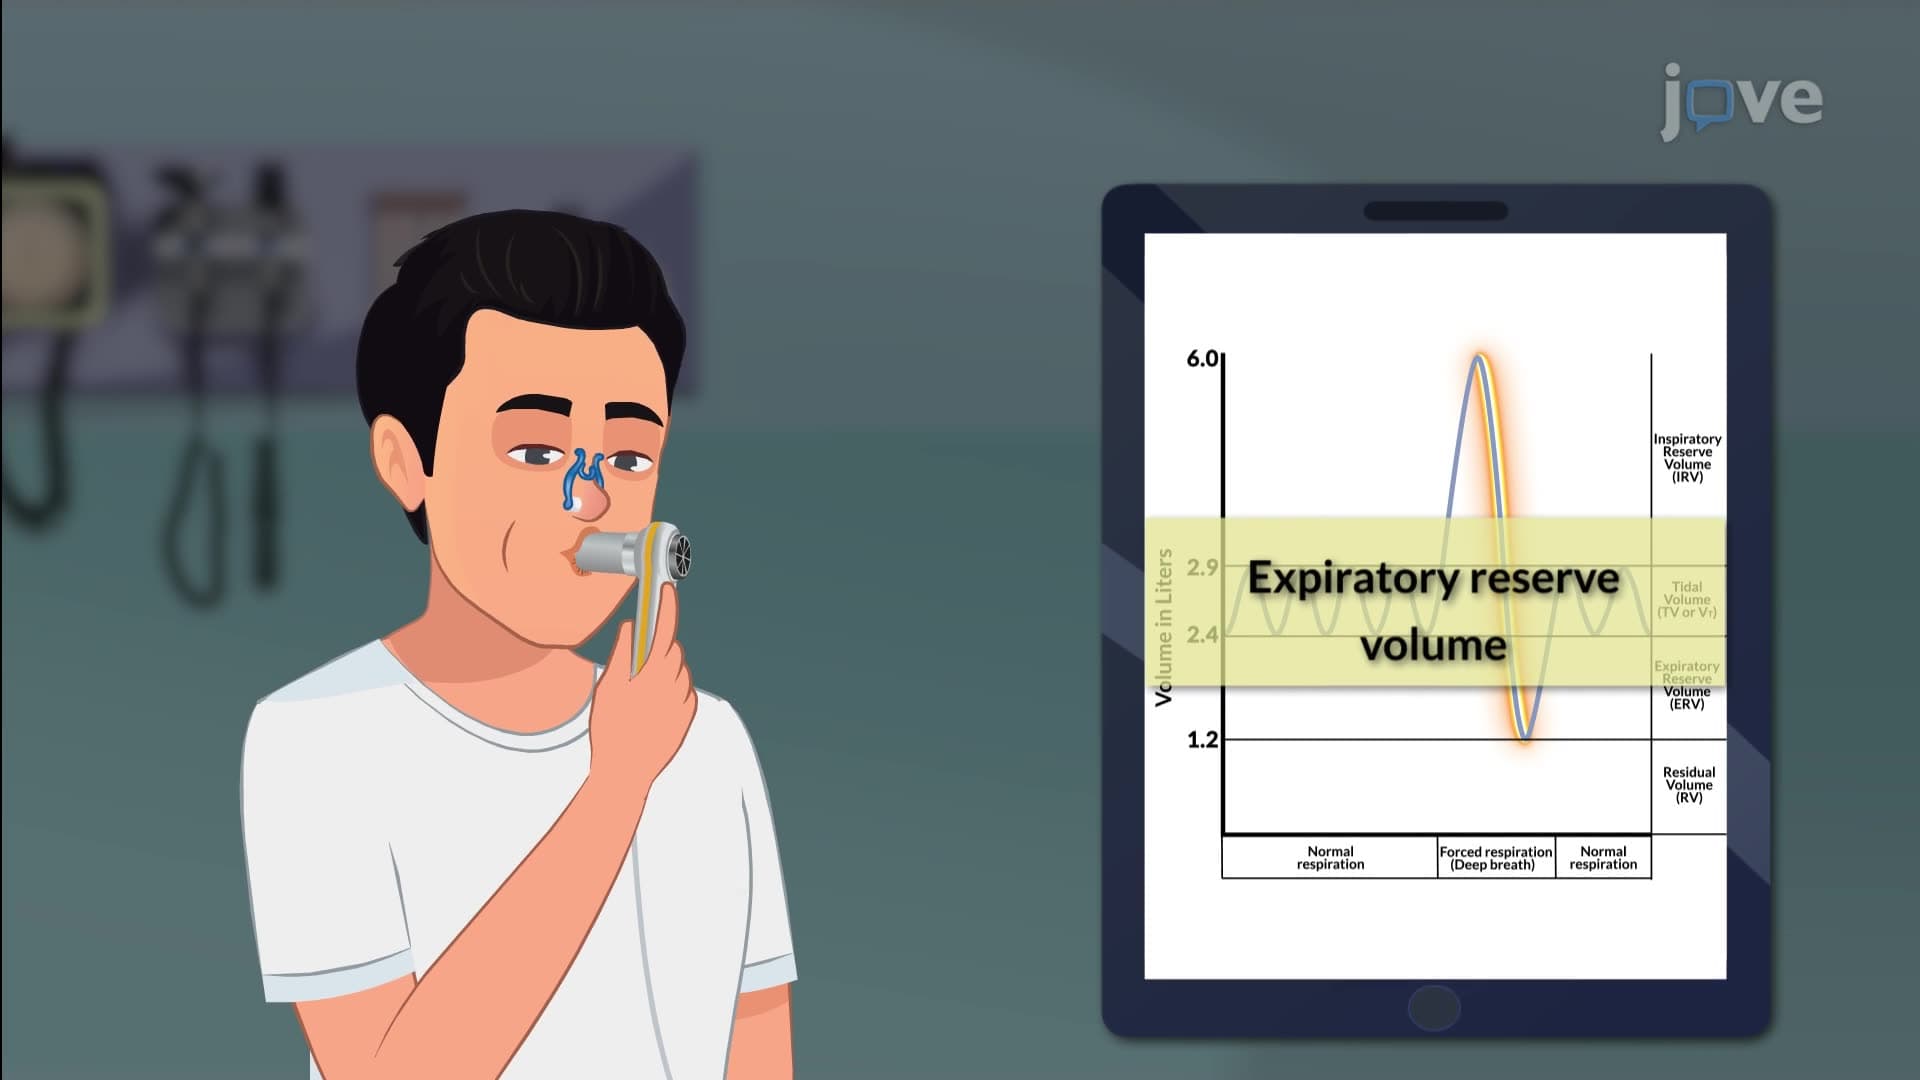
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling law of the...
 01:24
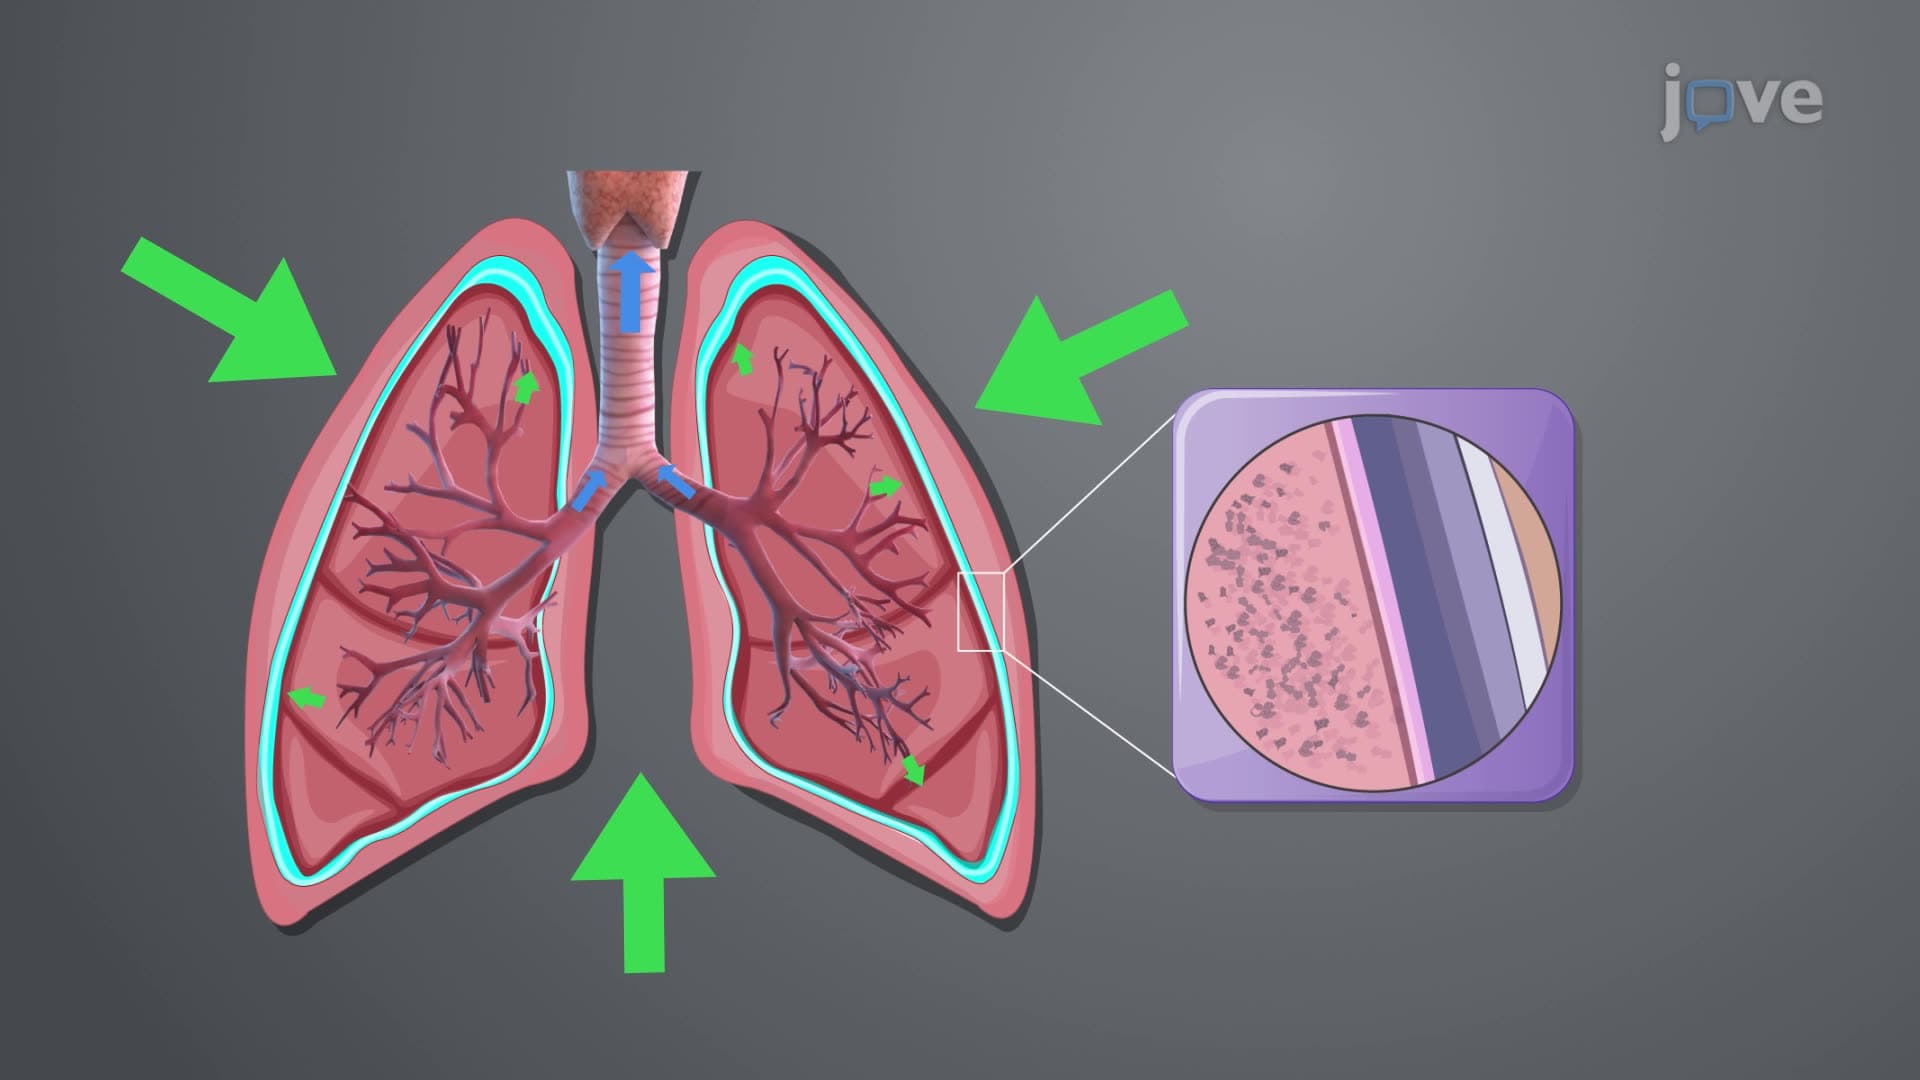
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...