Related Experiment Video
Updated: Oct 2, 2026
Cannula Implantation into the Cisterna Magna of Rodents
Published on: May 23, 2018
Pump-regulated cerebrospinal fluid drainage
J R Vender1, P Houle, A M Flannery
1Division of Pediatric Neurosurgery, Medical College of Georgia, Augusta, GA 30912, USA. jvender@mail.mcg.edu

Insights
Pump-controlled lumbar subarachnoid drainage offers a safe and effective method for managing cerebrospinal fluid (CSF) issues in pediatric patients. This technique ensures precise CSF removal in a closed system, overcoming challenges in children.
Area of Science:
- Neurosurgery
- Pediatric Neurology
- Critical Care Medicine
Background:
- Cerebrospinal fluid (CSF) drainage via lumbar subarachnoid space is crucial for treating CSF fistulas and managing intracranial pressure.
- Pediatric patients present unique challenges for traditional lumbar drain management.
- Effective CSF management is vital for neurological health in both children and adults.
Observation:
- The presented pump-controlled lumbar subarachnoid drainage technique addresses specific pediatric challenges.
- This method provides a closed system, mitigating issues related to patient position and activity.
- Accurate titration of CSF removal is a key feature of the observed technique.
Findings:
- The pump-controlled lumbar drainage method is demonstrated as safe and effective in the pediatric population.
- Precise control over CSF removal rates was achieved using this technique.
- The closed system design proved advantageous in maintaining consistent drainage regardless of patient movement or position.
Implications:
- This technique offers a valuable advancement for pediatric neurosurgery and critical care.
- Improved management of CSF-related conditions in children can lead to better patient outcomes.
- The method's robustness suggests potential for wider application in managing intracranial pressure and CSF leaks.
Abstract:
The drainage of cerebrospinal fluid (CSF) from the lumbar subarachnoid space is an effective technique for the treatment of CSF fistula and control of intracranial pressure in children and adults. The use of the lumbar drain poses unique challenges, however, in the pediatric population. We present a safe and effective method of pump-controlled lumbar subarachnoid drainage. This technique allows accurate titration of CSF removal while providing a closed system which is not sensitive to position changes or patient activity. Four case histories are reviewed.
More Related Videos
Related Concept Videos
 01:22
Aneurysm IV: Nursing Management
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
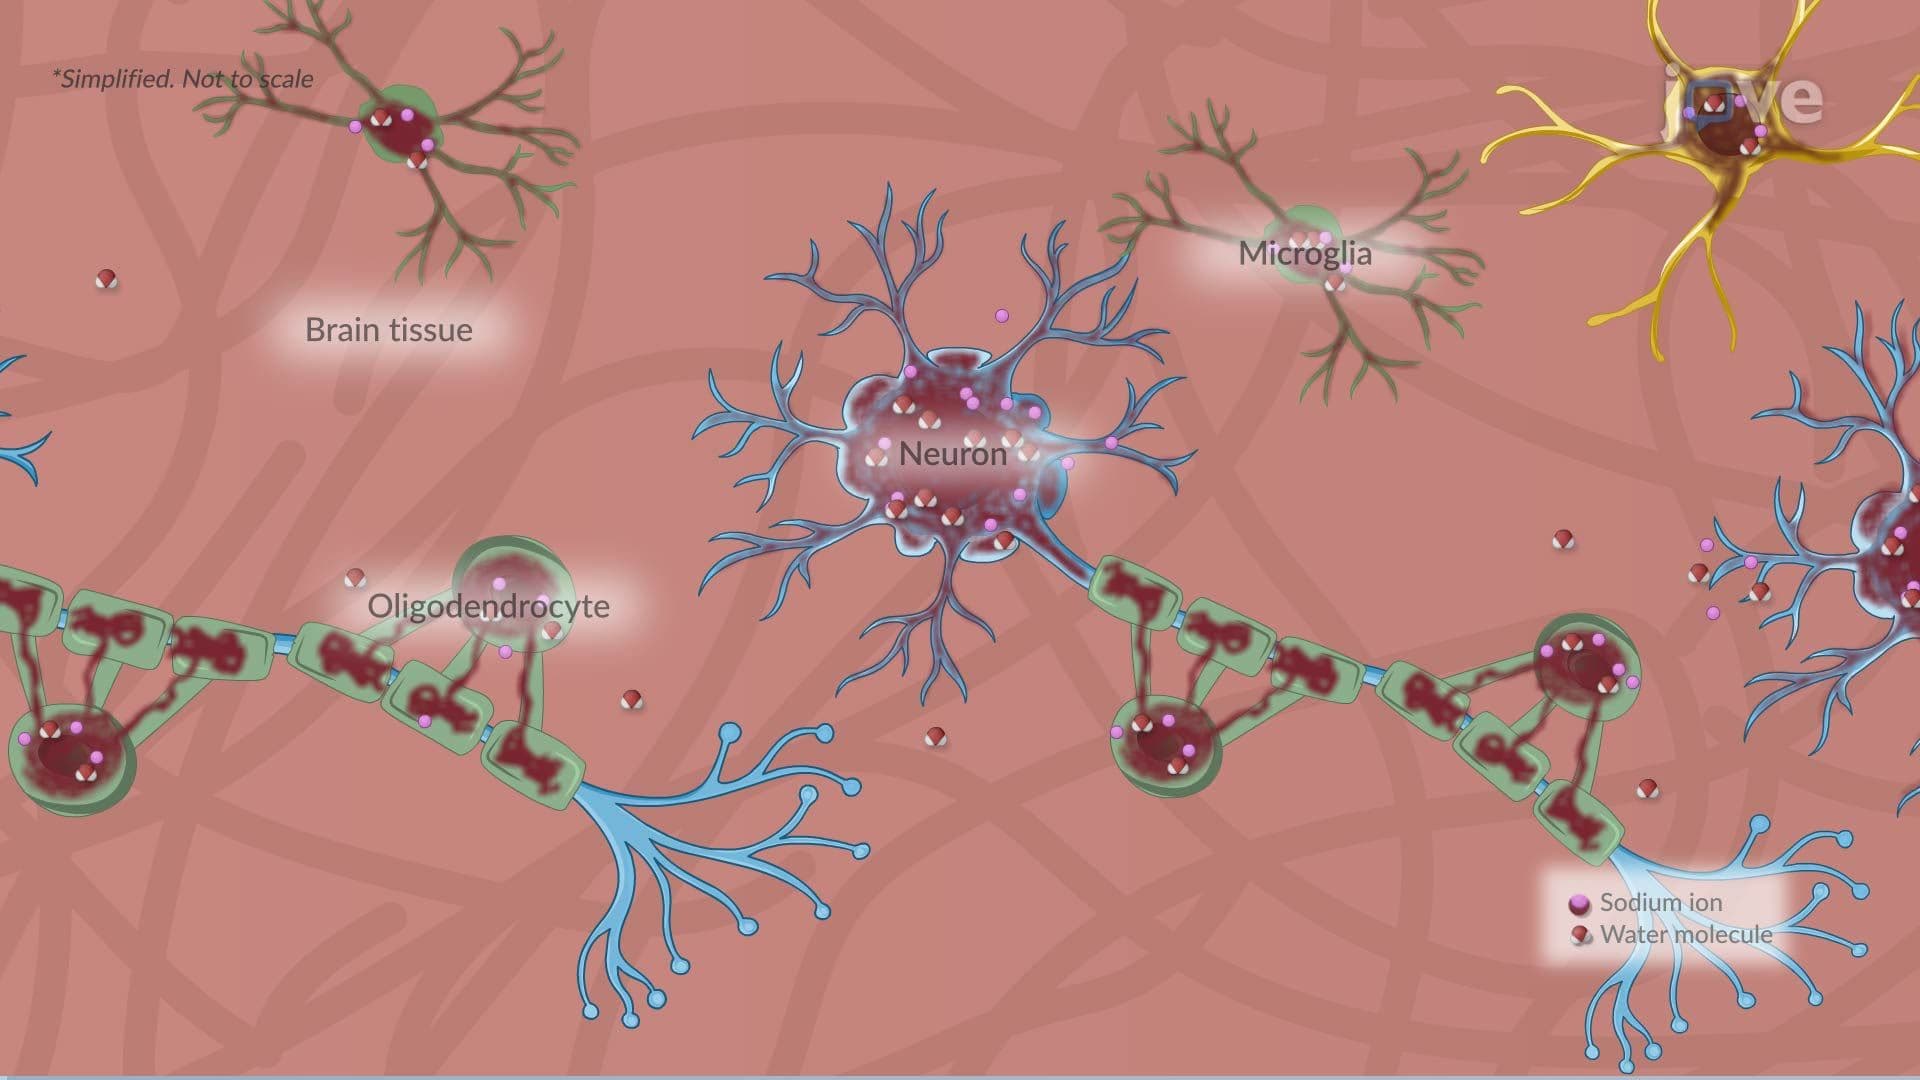
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:21
Cytotoxic Edema: Pathophysiology