Related Experiment Video
Updated: Aug 22, 2026

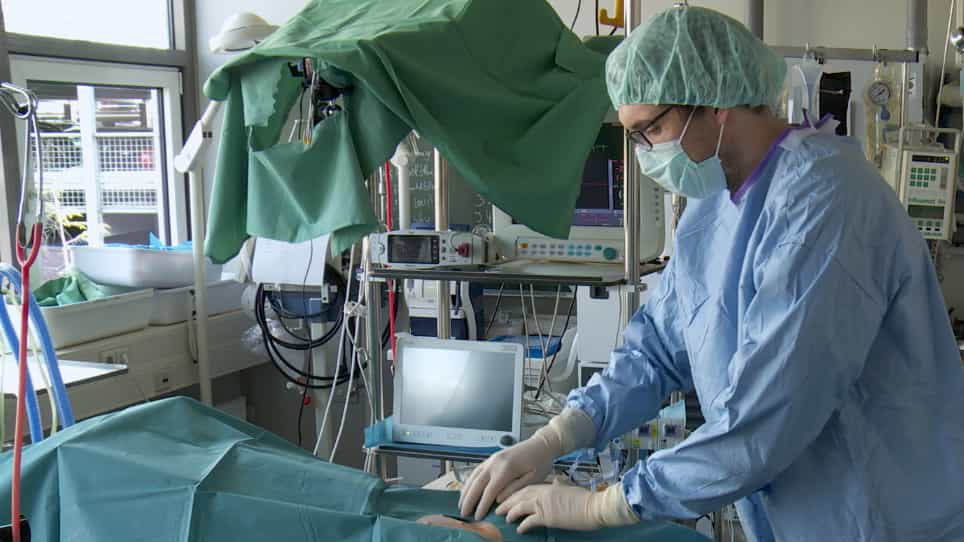
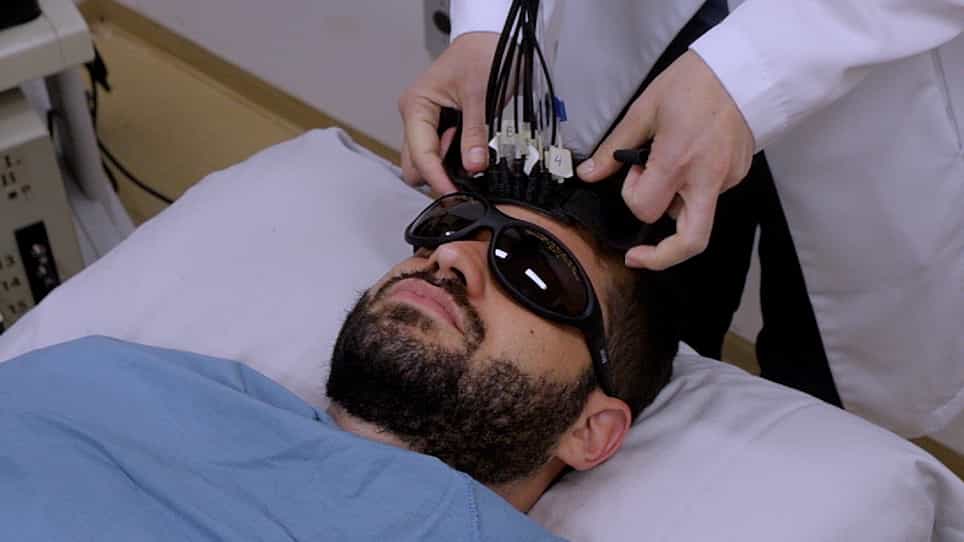
A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
[Head-brain injury and cerebral hypoxia. Diagnosis--monitoring--therapy]

Abstract:
The main reason for posttraumatic secondary brain damage is cerebral hypoxia. Both, severity and duration of hypoxia are crucial in determining wether irreversible cerebral infarction will occur or not. For the clinical routine, the diagnosis of hypoxia is indirectly made by low CPP, low jugular-venous oxygen saturation (SjO2) or low tissue PO2. To minimize misleading false negative SjO2, the CT-Approach for the side of monitoring and calculation of arterial-jugular-venous lactate content for detection of anaerobic metabolism is recommended. Targeted treatment of hypoxia according to the underlying cause is mandatory. Primary goal is to increase cellular oxygen delivery by correction of low arterial oxygen content and elevation of regional CBF. Within the autoregulatory range decreasing CPP causes vasodilation and increasing CPP vasoconstriction with increasing or decreasing cerebral blood volume respectively. Initially elevation of the lower autoregulatory threshold often requires CPP 70 mmHg. Targeted treatment of intracranial hypertension must avoid decreasing CPP. In the early posttraumatic phase prevention of cerebral hypoxia relies on management of CBF by means of CPP and cerebral vascular resistance. Thereafter targeted treatment of intracranial hypertension caused by cerebral edema and hypervolemia are increasingly important.
Related Concept Videos
 01:23
Hypoxia
Types of Hypoxia
There are four primary types of hypoxia, each resulting from a different cause:
1. Anemic hypoxia: This type occurs due to insufficient oxygen delivery caused by a lack of red blood cells (RBCs) or RBCs with abnormal or...
 01:15
Ischemic Stroke ll: Pathophysiology
 01:28
Traumatic Brain Injury l: Introduction