Extensor digiti minimi tendon "rerouting" transfer in permanent abduction of the little finger
Related Experiment Video
Updated: Oct 15, 2026
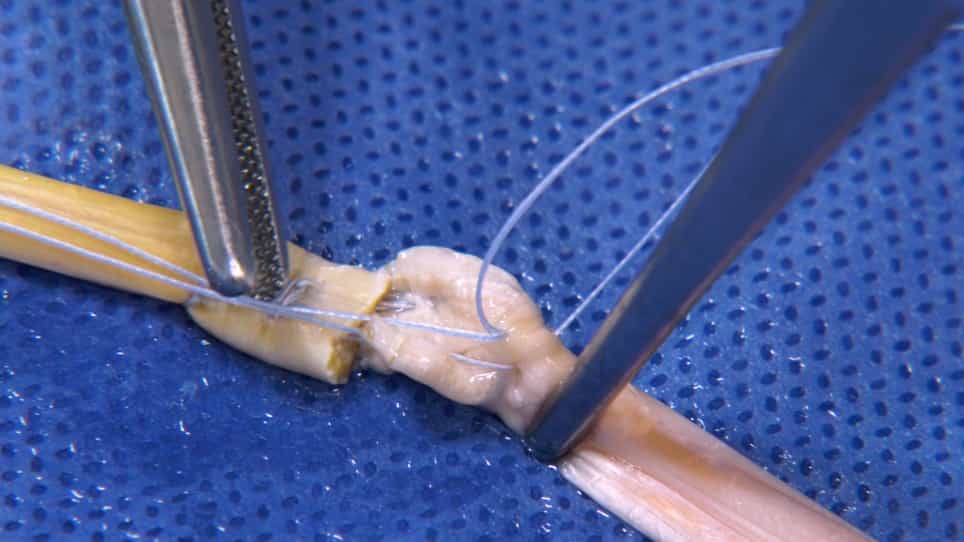
Polytetrafluoroethylene (PTFE) as a Suture Material in Tendon Surgery
Published on: October 6, 2022
N Bellan1, F Belkhiria, C Touam
1Service de Chirurgie Orthopédique et Traumatologique, Hôpital Militaire de Tunis, Tunisie.

Abstract:
Permanent abduction of the little finger is a bothersome deformity which usually occurs in the context of sequelae of ulnar nerve palsy (Wartenberg's sign), but also in rheumatoid arthritis. The authors report an original technique for correction of this deformity. The extensor digiti minimi tendon is sectioned at its distal insertion and transferred in the wrist through the extensor retinaculum. The "rerouted" tendon is finally resutured distally on the radial aspect of the interosseous muscle. Side-to-side suture of the transferred tendon to the extensor digitorum tendon of the little finger further reinforces the solidity of the procedure. The distal insertion of the extensor digiti minimi tendon is consequently radialized. Its new direction eliminates the abduction component, and the tendon then behaves as an active adductor of the little finger. Five cases (2 cases of ulnar nerve palsy, 3 cases of rheumatoid arthritis) are reported with a mean follow-up of 19 months. All patients have complete active adduction of the little finger in extension, with a persistent capacity for abduction. The other correction techniques published in the literature are discussed.

Related Concept Videos
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...