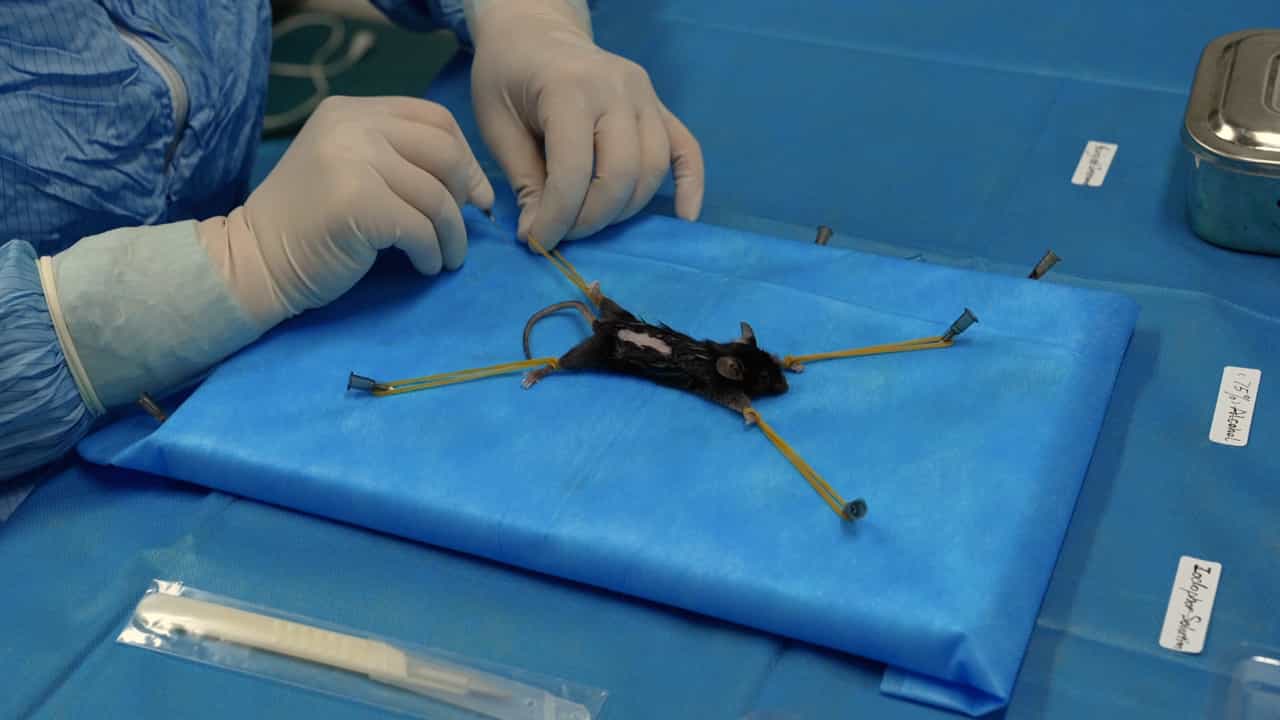
Related Experiment Video
Updated: Jul 30, 2026


A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Influence of estrogen deficiency and replacement on T-cell populations in rat lymphoid tissues and organs
F F Safadi1, I R Dissanayake, G G Goodman
1Department of Anatomy and Cell Biology, Temple University School of Medicine, Philadelphia, PA 19140, USA.

Estrogen deficiency following ovariectomy or menopause results in bone loss. Although evidence strongly suggests that the immune system is involved in the pathogenesis of estrogen-deficient osteoporosis, it is not clear what role, if any, the T-lymphocyte plays in this process. Therefore, we examined the distribution of T-cell subsets in lymphoid organs and tissues, under varying estrogenic states in the rat. Six-month-old female Sprague-Dawley rats, ovariectomized (Ovx) and sham-operated, were randomized 5 d post-surgery into six groups to receive the following treatments: (A) sham/placebo; (B) sham/low-dose E2; (C) sham/high-dose E2; (D) Ovx/placebo; (E) Ovx/low-dose E2; (F) Ovx/high-dose E2. Half of the treated rats (groups A-F) were sacrificed on d 14; the remainder on d 28. Following euthanasia, mononuclear cells were isolated from the thymus, peripheral blood, spleen, lymph node and bone marrow, and were labeled for flow cytometric analysis using mouse anti-rat monoclonal antibodies directed against CD5, CD4, and CD8 antigenic markers. In the thymus, ovariectomy caused a dramatic increase and E2 treatment caused a dose-dependent decrease in weight that was proportional to the number of thymocytes. In the bone marrow, ovariectomy caused a significant reduction in the percentage of all T-cell subsets examined and this effect persisted throughout the duration of the study. Estrogen replacement therapy at the low-dose reversed the effects of ovariectomy and high-dose E2 treatment caused an increase in T-cell subsets in both the sham and Ovx groups, an effect that was more pronounced at d 14 compared with d 28. Although the percentages of some T-cell subsets in the other lymphoid organs/tissues were altered by ovariectomy or E2 treatment at d 0 and 14, all these changes had normalized by d 28 except for CD5 and CD4 cells in peripheral blood. In summary, with the exception of T-lymphocytes in the bone marrow, the effects of varying estrogenic states on T-cells were variable and transient. The influence of estrogen status on bone marrow T-lymphocytes suggests that these cells may play a role in mediating the effects of estrogen on bone turnover and warrant additional studies focusing on the functional role of T-cells in the bone marrow compartment.
Estrogen deficiency following ovariectomy or menopause results in bone loss. Although evidence strongly suggests that the immune system is involved in the pathogenesis of estrogen-deficient osteoporosis, it is not clear what role, if any, the T-lymphocyte plays in this process. Therefore, we examined the distribution of T-cell subsets in lymphoid organs and tissues, under varying estrogenic states in the rat. Six-month-old female Sprague-Dawley rats, ovariectomized (Ovx) and sham-operated, were randomized 5 d post-surgery into six groups to receive the following treatments: (A) sham/placebo; (B) sham/low-dose E2; (C) sham/high-dose E2; (D) Ovx/placebo; (E) Ovx/low-dose E2; (F) Ovx/high-dose E2. Half of the treated rats (groups A-F) were sacrificed on d 14; the remainder on d 28. Following euthanasia, mononuclear cells were isolated from the thymus, peripheral blood, spleen, lymph node and bone marrow, and were labeled for flow cytometric analysis using mouse anti-rat monoclonal antibodies directed against CD5, CD4, and CD8 antigenic markers. In the thymus, ovariectomy caused a dramatic increase and E2 treatment caused a dose-dependent decrease in weight that was proportional to the number of thymocytes. In the bone marrow, ovariectomy caused a significant reduction in the percentage of all T-cell subsets examined and this effect persisted throughout the duration of the study. Estrogen replacement therapy at the low-dose reversed the effects of ovariectomy and high-dose E2 treatment caused an increase in T-cell subsets in both the sham and Ovx groups, an effect that was more pronounced at d 14 compared with d 28. Although the percentages of some T-cell subsets in the other lymphoid organs/tissues were altered by ovariectomy or E2 treatment at d 0 and 14, all these changes had normalized by d 28 except for CD5 and CD4 cells in peripheral blood. In summary, with the exception of T-lymphocytes in the bone marrow, the effects of varying estrogenic states on T-cells were variable and transient. The influence of estrogen status on bone marrow T-lymphocytes suggests that these cells may play a role in mediating the effects of estrogen on bone turnover and warrant additional studies focusing on the functional role of T-cells in the bone marrow compartment.