Related Experiment Video
Updated: Oct 15, 2026
Long Term Chronic Pseudomonas aeruginosa Airway Infection in Mice
Published on: March 17, 2014
Influence of clinical history on airways bacterial colonization in subjects with chronic tracheostomy
M Lusuardi1, A Capelli, C G Cerutti
1Salvatore Maugeri Foundation, IRCCS, Rehabilitation Institute of Veruno, Italy. mlusuardi@fsm.it

Abstract:
Patients with chronic tracheostomy are subject to significant bacterial colonization of the airways, a risk factor for respiratory infections. The aim of our study was to verify whether bacterial colonization and humoral immune response in the airways can be influenced by the disease which led to chronic respiratory failure and tracheostomy. Thirty-nine clinically stable outpatients with chronic tracheostomy were considered: 24 were affected by chronic obstructive pulmonary disease (COPD) (mean age 66 years, range 54-78, M/F 19/3; months since tracheostomy 23, range 3-62), 15 by restrictive lung disease (RLD) (12 thoracic wall deformities, three neuromuscular disease; age 57 years, range 41-72; M/F 3/12, months since tracheostomy 22, range 2-68). Recent antibiotic or corticosteroid treatments (< 1 month) were among exclusion criteria. Bacterial counts were assessed in tracheobronchial secretions with the method of serial dilutions. Identification of bacterial strains was performed by routine methods. Albumin, IgG, A, and M were measured in airways secretions with an immunoturbidimetric method. No significant differences were found between the two groups as regards either the quantitative bacterial cultures (RLD 81.4, 2.6-4200 x 10(4); COPD 75.9, 1.0-1530 x 10(4) colony forming units (cfu)/ml, geometric mean, range) or the prevalence of the main bacterial strains, (Pseudomonas species: 38 and 37%, Serratia marcescens: 31 and 23%, Staphylococcus aureus: 14 and 6%, Proteus species: 3 and 8%, for RLD and COPD respectively) as a percentage of total strains isolated (RLD = 26, COPD = 48). Immunoglobulin levels did not show significant differences, apart from being higher in underweight subjects. We conclude that in our series of stable outpatients with chronic tracheostomy, bacteria-host interaction in the airways was not influenced by the clinical history.
Related Concept Videos
 01:29
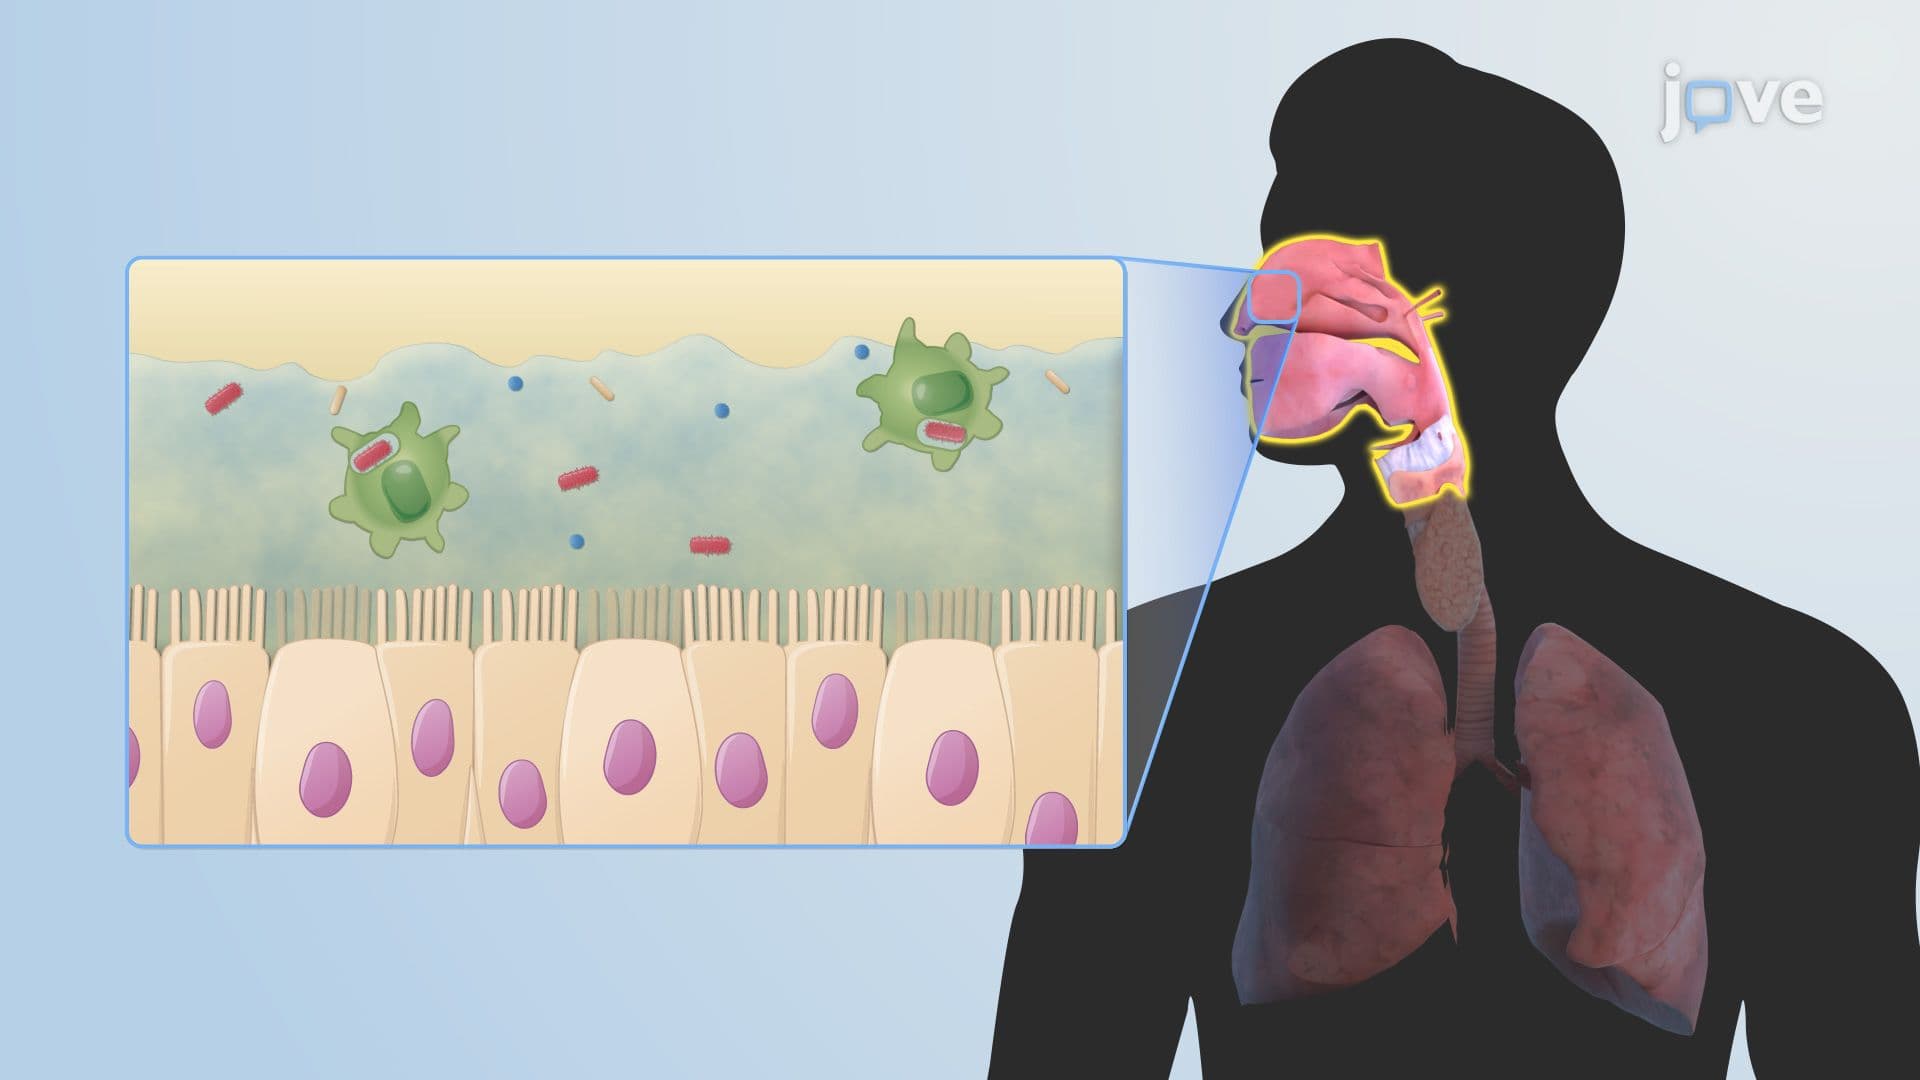
Microbiota of the Respiratory Tract
 01:28
Physical Assessment of the Respiratory Tract I: Health History
Subjective Data
Subjective data provides vital information about the patient's health history and symptoms. This data is typically collected through interviews in which patients describe their experiences, symptoms, and concerns.
Health history and key...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:23
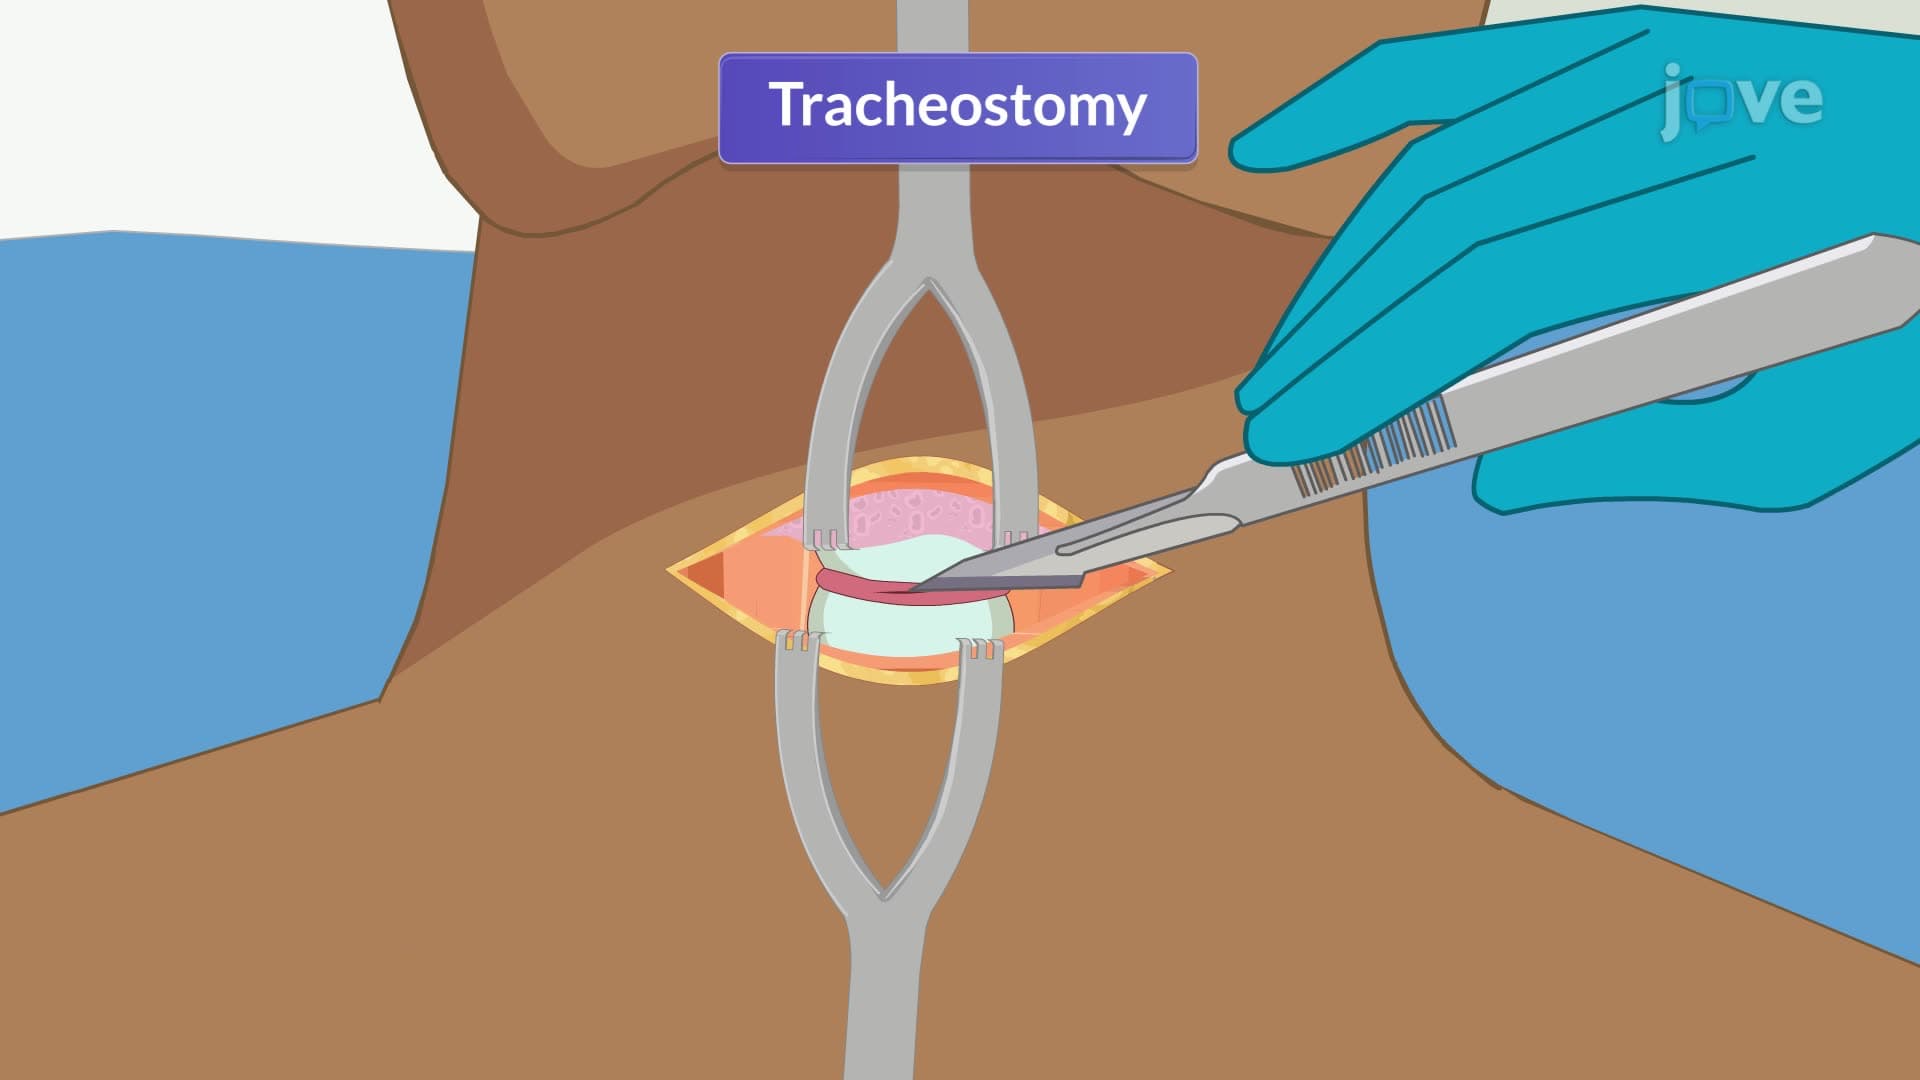
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...