Related Experiment Video
Updated: Aug 4, 2026
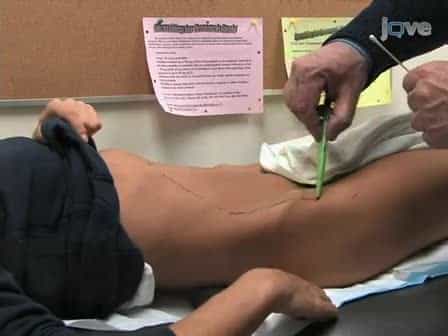

Demonstration of Cutaneous Allodynia in Association with Chronic Pelvic Pain
Published on: June 23, 2009
Musculoskeletal pelvic pain in a pediatric and adolescent gynecology practice
Schroeder1, Sanfilippo, Hertweck
1Divisions of Pediatric and Adolescent Gynecology, Departments of Obstetrics and Gynecology, MCP/Hahnemann School of Medicine and University of Louisville School of Medicine, Pittsburgh, PA, USA.

Abstract:
Background: Pelvic pain is a common complaint encountered in pediatric and adolescent gynecology. Etiologies are similar to those found in adult women, but the incidence and presentations vary with age. The purpose of this study is to review musculoskeletal (MS) pelvic pain in a pediatric and adolescent gynecology setting. Methods: A retrospective review of charts of 63 patients presenting to a private practice pediatric and adolescent gynecologist between 7/1/97 and 6/30/99 was performed. To be included in analysis, patients had a diagnosis of pelvic pain which could not be explained by standard gynecologic history, physical exam, laboratory, and ultrasound evaluation or did not respond to standard treatments for known endometriosis. A history of laparoscopy was not required, but when it was performed it could be used to exclude patients from analysis if a reason for the pain was identified. All patients who fulfilled these criteria had been screened for MS etiologies of pelvic pain using the leg lift (Carnett test) and/or head lift. Results: Sixty-three patients aged 9-23 (mean 15.21, SD 2.71) fulfilled the criteria for evaluation. Diagnoses included irritable bowel syndrome (N = 4, 6.35%), interstitial cystitis (N = 1, 1.56%), unexplained (N = 7, 11.11%), endometriosis not responding to ablation & GnRH agonists (N = 2, 3.17%), endometriosis not responding to ablation & GnRH agonists & MS pain (N = 7, 11.11%), and MS pain (N = 42, 66.67%). Mean age of those with MS pain was 15. 27 (SD 2.94), and mean duration of symptoms prior to diagnosis was 17.97 mo (SD 20.90, range 1 week-7 yr). On physical exam, trigger points were identified as causative factors in 5 (10.20%), and 40 (81.63%) had a + Carnett test. Of those with a final diagnosis of MS pain, only 5/31 (16.31%) responded to nonsteroidal anti-inflammatory agents, 6/30 (20.0%) responded to OCPs, and 3/11 (27.27%) responded to DMPA-2/3 also had a diagnosis of endometriosis. Nineteen (38.78%) had been surgically explored for the pain in the past, 1 by laparotomy & 18 by laparoscopy. Only 3 (15.79%) had symptomatic improvement after surgery. Physical therapy resulted in resolution of symptoms in 20/21 (95.24%) who completed treatment. Four of 5 (80%) who underwent trigger point injections responded.Conclusions: MS etiologies of pelvic pain are common in the adolescent age group and respond well to physical therapy. Physical therapy might be employed as an early intervention prior to surgery in adolescent girls with unexplained pelvic pain.
More Related Videos
 07:20
Intraoperative Detection of Subtle Endometriosis: A Novel Paradigm for Detection and Treatment of Pelvic Pain Associated with the Loss of Peritoneal Integrity
Published on: December 21, 2012
 02:41
Acupoint Catgut Embedding for Treatment of Chronic Pelvic Pain Due to the Sequelae of Pelvic Inflammatory Disease
Published on: May 3, 2024
Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:21
Nursing Assessment of the Genitourinary System I: Health History
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
 01:22
Nursing Assessment of the Genitourinary System III: Percussion and Auscultation
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:28
Urinary Tract Calculi V: Nursing Management