Transcapillary forces and the development of oedema in the lower limb of patients with chronic critical limb ischaemia (CLI)
Related Experiment Video
Updated: Oct 15, 2026
Osmotic Drug Delivery to Ischemic Hindlimbs and Perfusion of Vasculature with Microfil for Micro-Computed Tomography Imaging
Published on: June 29, 2013
H Z Khiabani1, M D Anvar, A J Kroese
1Department of Vascular Diagnosis and Research, University of Oslo, Norway.

Insights
Edema in critical limb ischemia (CLI) may stem from increased reabsorption pressure, not just low plasma albumin. This elevated pressure drives fluid filtration, leading to swelling in affected limbs.
Area of Science:
- Vascular Physiology
- Edema Pathogenesis
- Critical Limb Ischemia Research
Background:
- Transcapillary fluid transport is crucial for maintaining tissue hydration.
- Edema in critical limb ischemia (CLI) is a common complication with multifactorial causes.
- Understanding fluid dynamics in CLI is essential for effective treatment strategies.
Purpose of the Study:
- To investigate the factors regulating transcapillary fluid transport in patients with critical limb ischemia (CLI).
- To elucidate the specific causes of peripheral pitting edema in unilateral CLI.
- To analyze the relationship between interstitial fluid pressure, plasma colloid osmotic pressure, and edema formation.
Main Methods:
- Recruited 16 patients (6 men, 10 women; mean age 79 years) with unilateral CLI and pitting edema.
- Measured interstitial fluid colloid osmotic pressure (COP if) and interstitial fluid pressure (P if) in both affected and unaffected limbs using blister suction cups and wick-in-needle techniques.
- Measured plasma colloid osmotic pressure (COP pl) and plasma albumin concentration from venous blood samples.
Main Results:
- Interstitial fluid colloid osmotic pressure (COP if) was significantly lower in CLI limbs (2.3 mmHg) compared to contralateral limbs (3.1 mmHg).
- Interstitial fluid pressure (P if) was significantly higher in CLI limbs (0.7 mmHg) compared to contralateral limbs (-1.4 mmHg).
- Calculated reabsorption pressure (P r) was significantly higher in CLI limbs (19.6 mmHg) than in contralateral limbs (16.7 mmHg).
Conclusions:
- Low plasma albumin concentration and reduced plasma colloid osmotic pressure (COP pl) in CLI patients, while noted, do not fully explain unilateral edema.
- Elevated interstitial fluid pressure (P if) and consequently higher reabsorption pressure (P r) in CLI limbs are likely drivers of increased transcapillary filtration.
- These findings suggest that elevated reabsorption pressure, leading to increased net filtration, is a key factor in the development of edema in critical limb ischemia.
Objective:
factors regulating transcapillary fluid transport were investigated to elucidate the causes of oedema in CLI.
Material:
sixteen patients, 6 men and 10 women (mean age of 79+/-10.3 years) with unilateral CLI and peripheral pitting oedema.
Methods:
measurements were performed in both limbs. Interstitial fluid was collected by applying blister suction cups on the dorsolateral part of the foot and colloid osmotic pressure of this fluid (COP if) was measured in a colloid oncometer. Plasma colloid osmotic pressure (COP pl) was obtained from venous blood. Interstitial fluid pressure (P if) was measured by wick-in-needle technique.
Results:
mean COP if in the limbs with CLI was 2.3 S.D. 0.5 mmHg, significantly lower than in the limbs without CLI (3.1 S.D. 0.7 mmHg, p<0.0001). Mean COP pl was 21.1 S.D. 1.8 mmHg, which was lower than in healthy controls. Mean plasma albumin concentration was 30 S.D. 6 g/l which was lower than the reference values. Mean P if in the limbs with CLI was 0.7 S.D. 1.6 mmHg, significantly higher than in the limbs without CLI (-1.4 S.D. 1.4 mmHg, p<0.0001). The calculated mean reabsorption pressure (P r) in the limbs with CLI was 19.6 S.D. 1.7 mmHg, significantly higher than in the contralateral limbs (16.7 S.D. 2.1 mmHg, p<0.001).
Conclusion:
a low plasma albumin concentration in patients with CLI agrees with the reduction in COP pl but cannot explain the oedema formation, since it is unilateral. The high P r may cause a high transcapillary filtration pressure, resulting in a relatively great net filtration and subsequent oedema formation.

Related Concept Videos
 01:28
Capillary Exchange
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
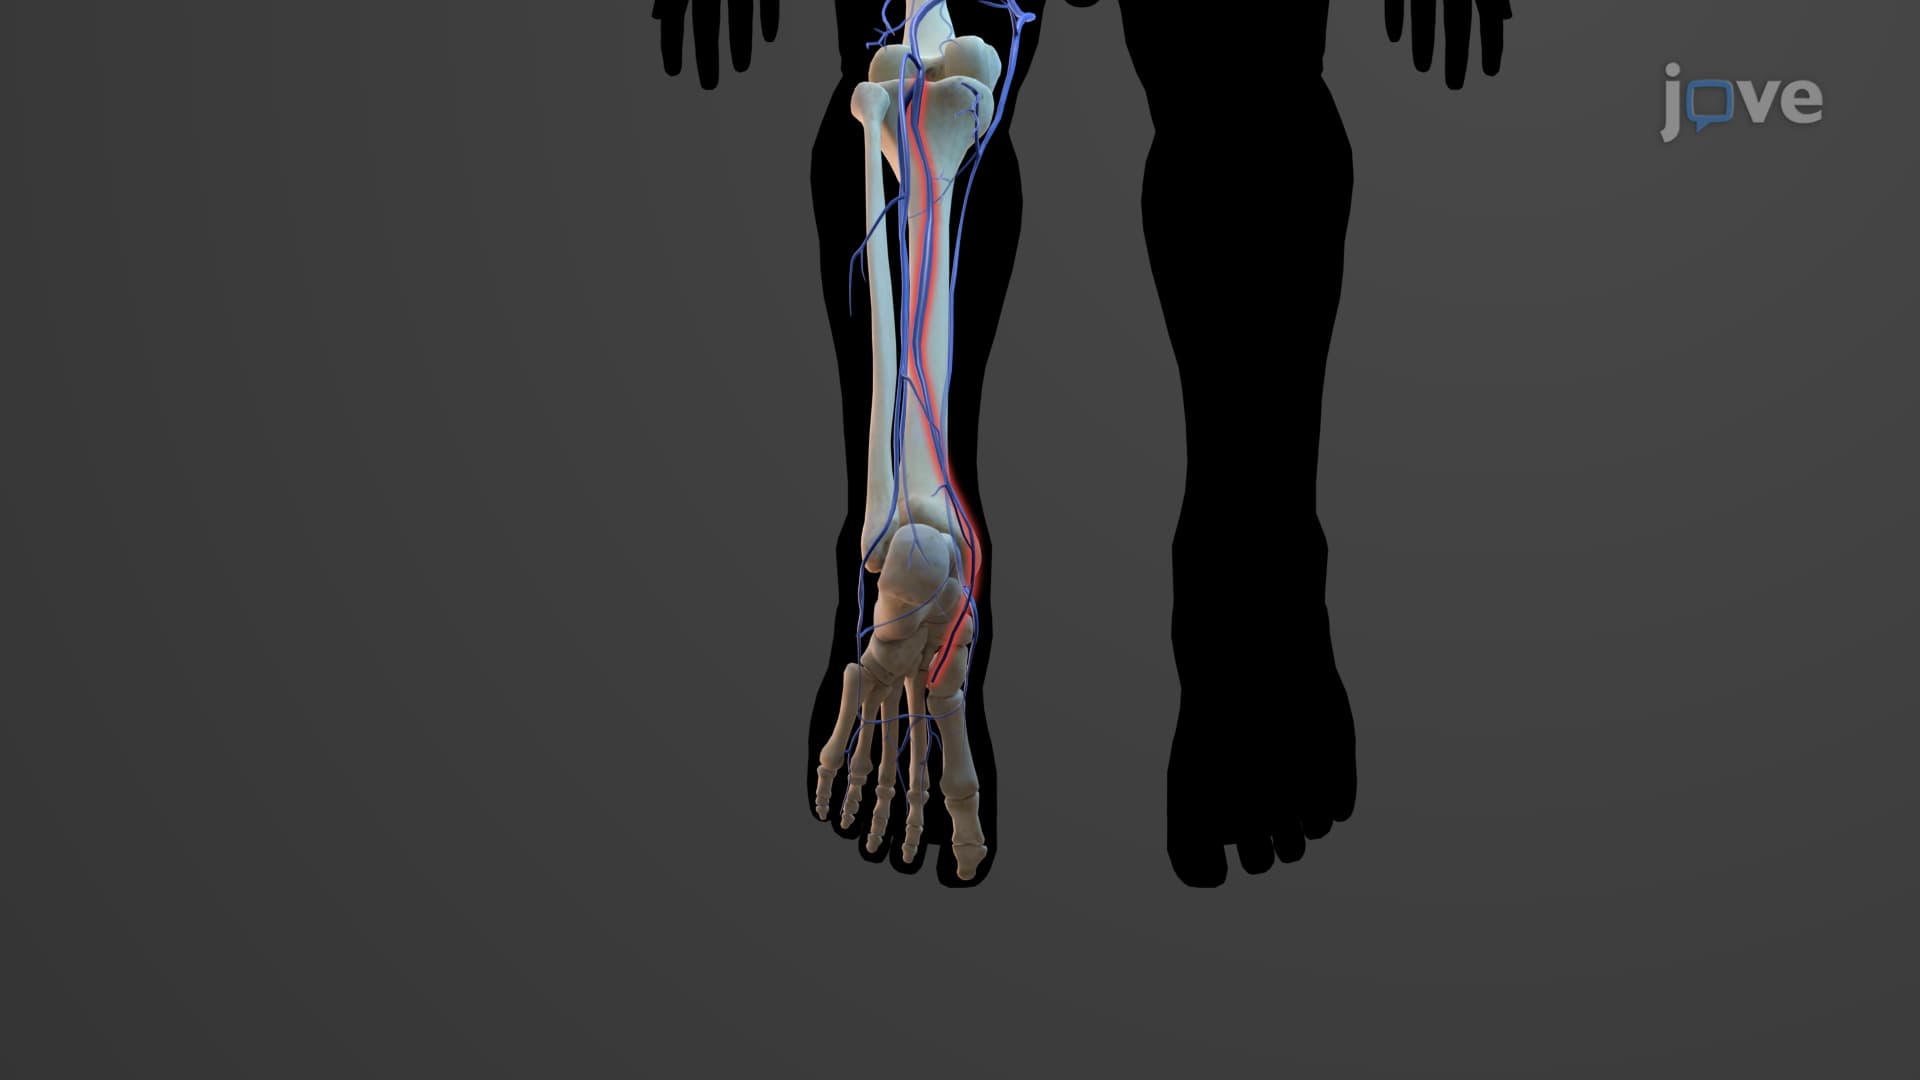 01:15
Veins of Lower Limbs
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the knee,...
 01:18
Fluid Movement Between Compartments
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:31
Diabetic Foot Ulcer