Iatrogenic pharyngoesophageal perforation in premature infants
Related Experiment Video
Updated: Oct 15, 2026

Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015

Insights
Iatrogenic pharyngoesophageal perforation in premature infants is difficult to diagnose and often mistaken for esophageal atresia. Early diagnosis and management are crucial for improving outcomes in these high-risk neonates.
Area of Science:
- Neonatal surgery
- Pediatric gastroenterology
- Critical care medicine
Background:
- Premature infants face a high risk of iatrogenic pharyngoesophageal perforation.
- This rare condition often presents with symptoms mimicking esophageal atresia.
- Diagnostic challenges and management strategies are critical for affected neonates.
Purpose of the Study:
- To highlight the diagnostic difficulties associated with iatrogenic pharyngoesophageal perforation in premature infants.
- To discuss appropriate management strategies based on clinical experience and literature review.
- To analyze outcomes and associated morbidities in neonates with this condition.
Main Methods:
- Retrospective review of 10 premature neonates treated for pharyngoesophageal perforation between 1980 and 1995.
- Analysis of diagnostic methods including plain chest x-ray, contrast esophagography, and endoscopy.
- Comparison of surgical versus conservative management approaches.
Main Results:
- Pharyngoesophageal perforation was caused by airway intubation or NGT insertion in most cases.
- Esophageal atresia was the initial diagnosis in 40% of cases, leading to diagnostic delays.
- Surgical intervention was required in 50% of cases, while conservative management was successful in the remainder.
- Complications included bronchopulmonary dysplasia and necrotizing enterocolitis; mortality was 20%.
Conclusions:
- Iatrogenic pharyngoesophageal perforation in premature infants is challenging to diagnose and can be misidentified as esophageal atresia.
- Clinical presentation, imaging (X-ray, esophagography), and endoscopy aid in diagnosis.
- Non-surgical management is feasible in many cases, but outcomes can be unfavorable due to prematurity and comorbidities.
Background:
Premature infants are particularly at risk of iatrogenic pharyngoesophageal perforation. It is a rare occurrence but when it does occur it often mimics esophageal atresia. In the light of 10 patients treated in our service and those reported in the literature we have highlighted the diagnostic difficulties and discussed the appropriate management.
Patients:
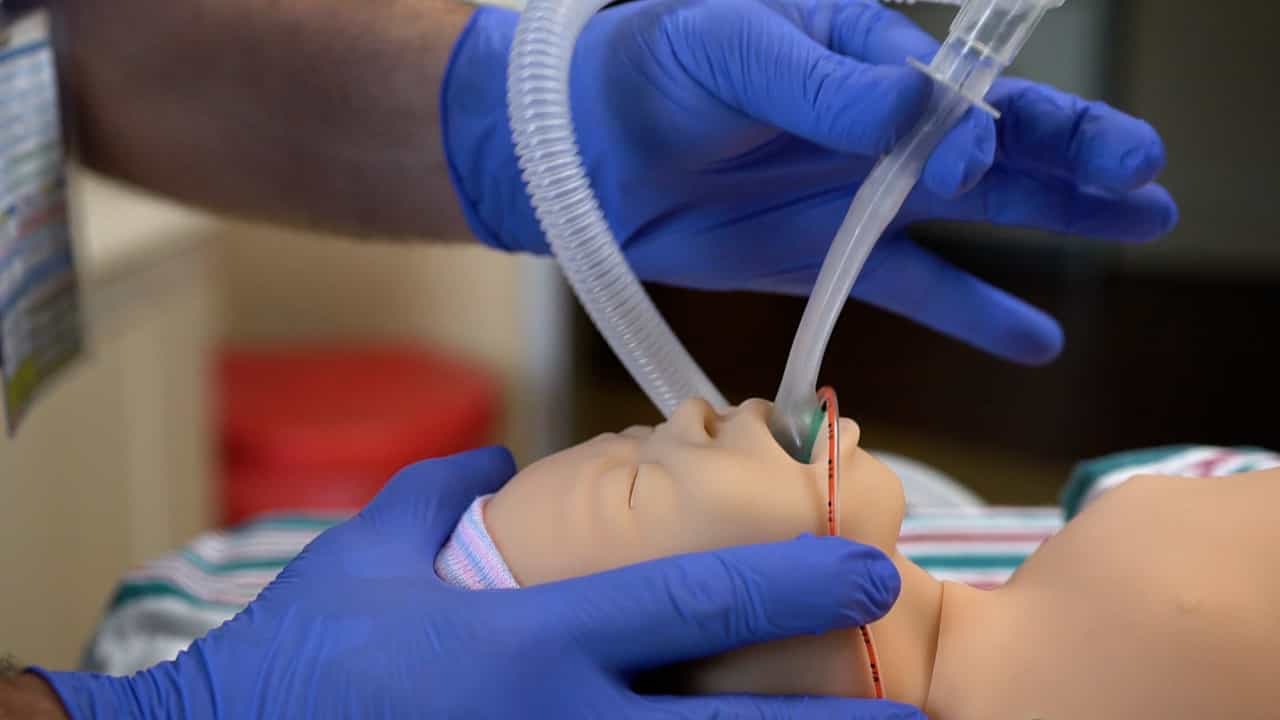
Between 1980 and 1995, we treated 10 premature neonates for pharyngoesophageal perforation. Six of these neonates weighed less than 1500 g. Esophageal atresia was the primary diagnosis in 4 cases. The pharyngoesophageal perforation was caused by repeated airway intubation in 3 cases and by overenthusiastic routine postpartum suctioning or nasogastric tube (NGT) insertion in 7 others. Severe respiratory distress occurred in 7 neonates. A plain chest x-ray revealed a large right pneumothorax in 3 cases and an aberrant NGT in 3 other cases. Four neonates had a contrast esophagography and 4 neonates underwent endoscopy. Five cases were treated surgically. In 3 of these, esophageal atresia was the presumptive diagnosis and the perforation was only diagnosed intraoperatively via a right thoracotomy. One neonate required suturing of the perforation and another had a gastrostomy. In all 5 cases a mediastinal drain was left in situ. The 5 remaining neonates were treated conservatively with broad spectrum antibiotics, total parenteral nutrition, a silastic NGT and pharyngeal aspiration. One of these neonates had previously had a laparotomy for a colonic perforation. There was a good outcome in 4 neonates, one of whom required instrumental dilatation for an esophageal stricture. Bronchopulmonary dysplasia developed in 3 cases and necrotizing enterocolitis in 1 other case. Two neonates died.
Conclusion:
An iatrogenic perforation is often difficult to diagnose and can easily be confused with esophageal atresia. Clinical findings, a plain chest x-ray, an esophagography and endoscopy are helpful. Surgery can be avoided in most instances. The outcome is not always favorable especially as premature neonates are at risk of severe concomitant pathology.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Hiatal Hernia
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...