[Morphological and functional pelvic floor disorders from the gynecological viewpoint]
Related Experiment Video
Updated: Oct 15, 2026

Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
1Klinik und Poliklinik für Geburtshilfe und Frauenheilkunde, Klinikum der Universität München/Grosshadern. christoph.anthuber@gyn.med.uni-muenchen.de

Purpose:
The following article is designed to describe the diagnostics and therapy of morphological and functional defects in the female pelvic floor from a gynaecological point of view. Assessment of the relevance of imaging techniques is of particular importance.
Material And Methods:
The main diagnoses are: in the anterior compartment of the pelvic floor, urethro- cystocele; in the middle compartment, uterine descent/prolapse or enterocele; and in the posterior compartment, rectocele. They are clinically examined by means of a standardised gynaecological examination and classified according to recommendations from the International Continence Society (ICS) in order to obtain internationally comparable results. Comparison with the usual imaging procedures (introitus- and perineal sonography, colpocystorectography/defaecography and functional MRI of the pelvic floor) are described and critically discussed. The most important functions affected are storage and evacuation of the bladder and rectum. They are clinically examined by means of stress test and padweigh test and technically examined using urodynamics, sphincter-rectum manometry and EMG. Imaging procedures play a very important role here also.
Results:
Comparison of clinical and imaging procedures shows that the two methods are at present limited in comparability, mainly because different points of reference are used to quantify results. The line of the hymen is a good point of reference in grading descent and prolapse. During the gynaecological examination, the three compartments can readily be assessed separately by use of split gynaecological specula. This is presently practically impossible using imaging procedures. The pubococcygeal line is generally used to describe findings.
Discussion:
Scientific progress can only be expected if and when these problems are studied as a whole. Imaging procedures have securely established themselves in the diagnostic repertoire, but do not as yet influence therapy decisions. The indication and choice of operation depend on the severity of the patient's symptoms the clinical findings and the results of urodynamic investigations. Dynamic CTG is presently the most reliable method of showing all three compartments at rest and during function. It has largely replaced colpocystorectography. Sonography is found to be varied in ist results at the moment.
Related Concept Videos
 01:26
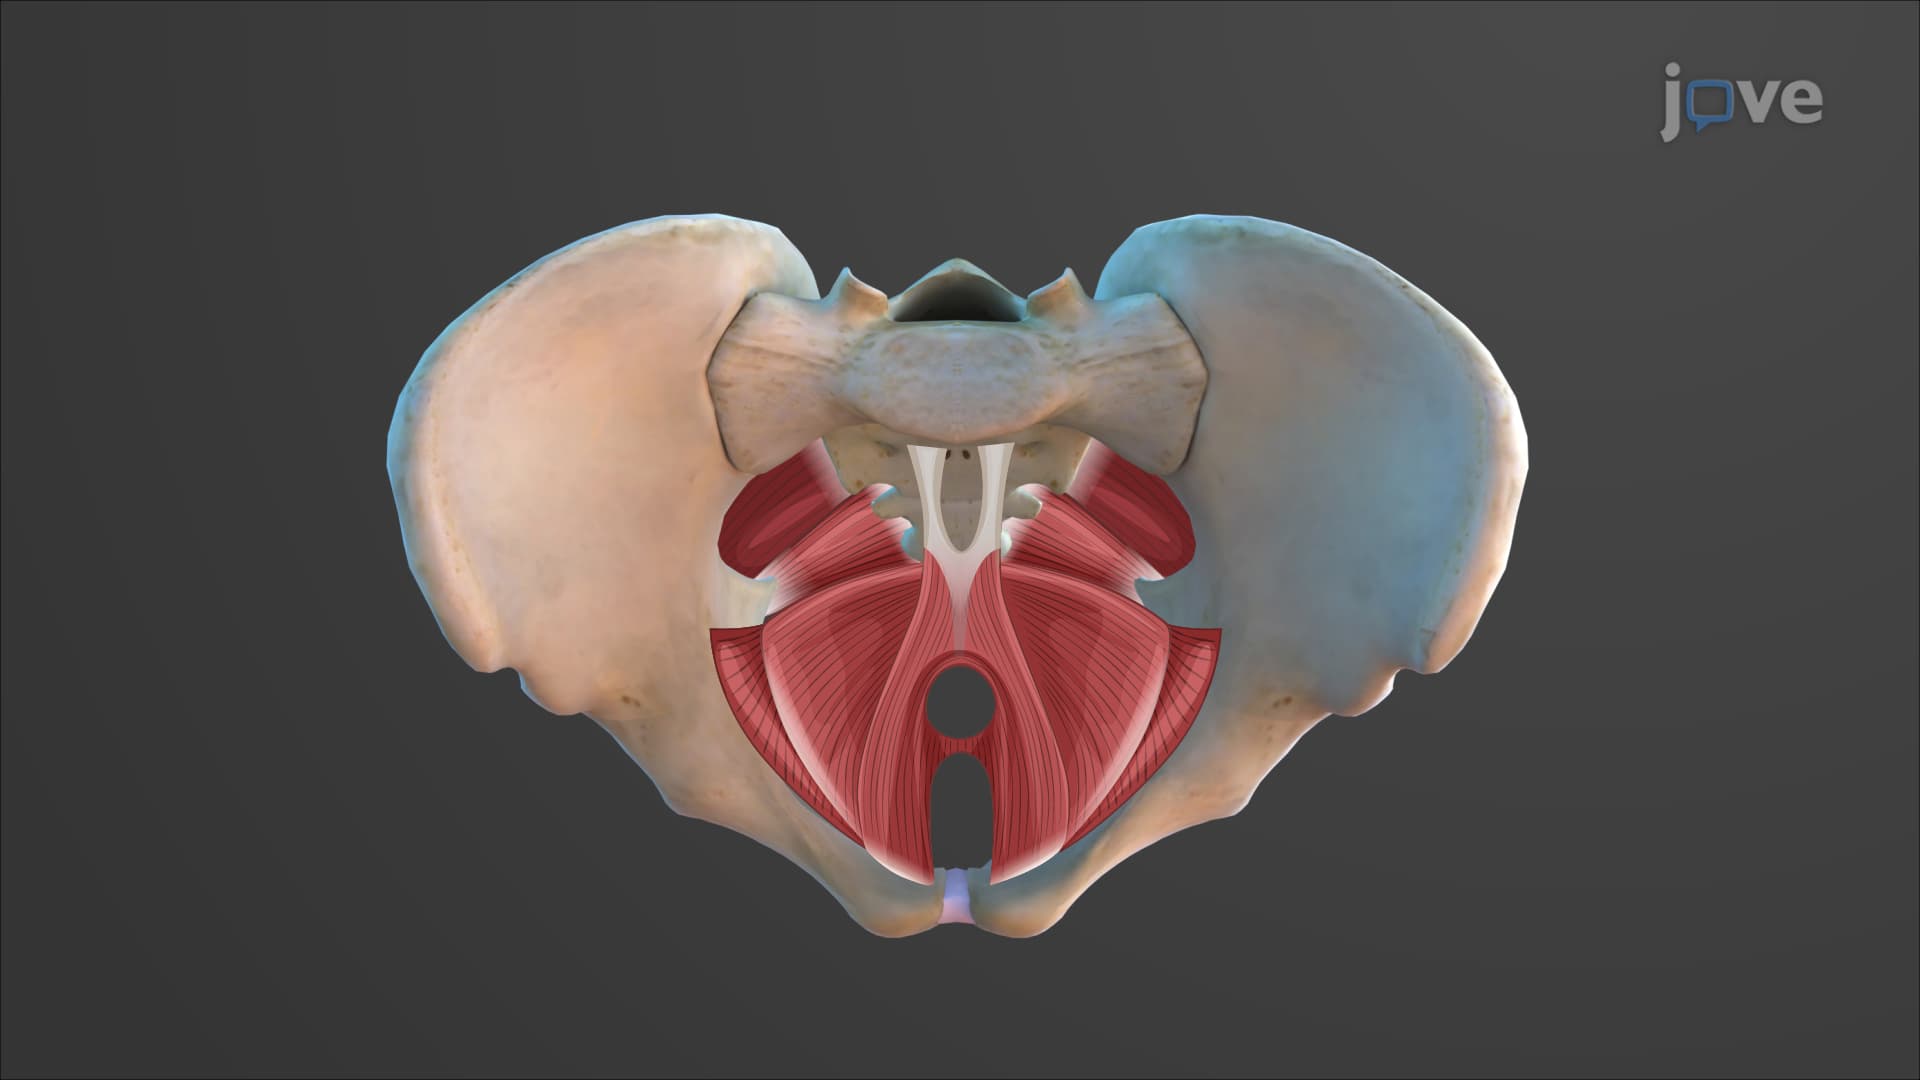
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:20
Disorders of the Urinary System
Urinary tract infections (UTIs) are one of the most common urinary system disorders. They are caused by bacteria that enter the urethra and can spread to the bladder resulting in cystitis. Pyelonephritis is the result of a UTI that has ascended to the level of the...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:24
Disorders of the Female Reproductive System
 01:20
Gastrointestinal Motility Disorders