Related Experiment Video
Updated: Oct 15, 2026
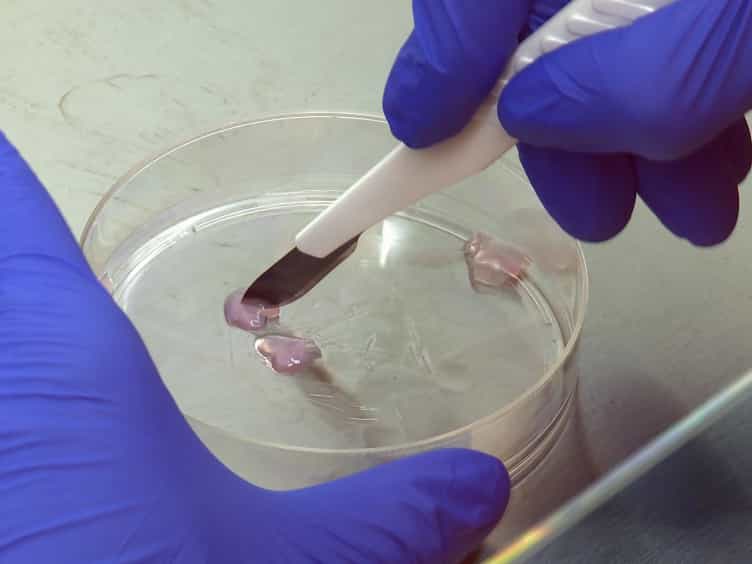
A 3D Human Lung Tissue Model for Functional Studies on Mycobacterium tuberculosis Infection
Published on: October 5, 2015
Adrenocortical reserve and morphology in tuberculosis
G A Prasad1, S K Sharma, A Mohan
1Department of Medicine, All India Institute of Medical Sciences, New Delhi.

Abstract:
Ninety seven patients (63 males, mean age 31.8 years, SD 2.3) with various forms of tuberculosis were studied. All of them were HIV negative. Thirty normal control subjects (16 males, mean age 36.4 years, SD 1.8) were also studied. Fifty-eight of the 97 patients (59.8%) were malnourished (BMI < 18 kg/m2). The mean basal serum cortisol was lower in the TB group (n = 91) (351 nmol/1; SD 150) as compared to the normal control group (n = 8) (402 nmol/1; SD 93) but this difference did not attain statistical significance. Following administration of synthetic ACTH (cosyntropin), the 30 and 60 minutes mean serum cortisol values in the TB group were significantly lower as compared to the normal control group (p < 0.05). Forty five of the 91 patients (49.5%) who underwent the ACTH stimulation test had compromised adrenal reserve. Fourteen of the 86 patients (16.3%) in whom adrenal morphology was studied revealed adrenal gland enlargement on abdominal CT scan. ACTH stimulation was done in 12 of these 14 patients and eight of them had compromised adrenal reserve. Repeat ACTH stimulation done six months to one year after treatment in 13 patients revealed significantly increased 30 minutes (p < 0.05) and 60 minutes (p < 0.05) serum cortisol values. While nine of these 13 patients were negative responders before treatment, only three of them had evidence of compromised adrenal reserve after one year of antituberculosis treatment, (p < 0.05). Serum cortisol values in patients with drug-sensitive and drug-resistant tuberculosis did not differ significantly. Patients with drug-resistant tuberculosis had a higher prevalence of adrenal gland enlargement (7 of the 30) as compared to those with drug-sensitive tuberculosis (7 of the 56) (p = NS). Subclinical adrenal insufficiency is prevalent in a significant number of patients with both drug-sensitive and drug-resistant tuberculosis, and in some of these it is associated with adrenal gland enlargement. The compromised adrenal reserve and enlargement seem to reverse with therapy.

Related Concept Videos
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:23
Tuberculosis
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...