Related Experiment Video
Updated: Aug 18, 2026


Murine Appendectomy Model of Chronic Colitis Associated Colorectal Cancer by Precise Localization of Caecal Patch
Published on: August 24, 2019
Abdominal pain and appendicitis: is there a difference in referrals between HMO pediatricians and private
1Division of Pediatric Surgery, UMDNJ-Robert Wood Johnson Medical School, New Brunswick, NJ 08903-0019, USA.

Insights
Health maintenance organizations (HMOs) and private pediatricians showed similar diagnostic accuracy for appendicitis and rates of perforated appendicitis. This suggests managed care does not negatively impact timely surgical referrals for pediatric appendicitis.
Area of Science:
- Pediatric Surgery
- Health Services Research
- Gastroenterology
Background:
- Rising incidence of late and perforated appendicitis has been anecdotally linked to managed care practices.
- Concerns exist that health maintenance organizations (HMOs) may delay surgical referrals to control costs.
Purpose of the Study:
- To compare diagnostic accuracy and referral patterns for pediatric appendicitis between HMO-affiliated and private practice pediatricians.
- To investigate whether managed care influences the timeliness of surgical referrals for appendicitis.
Main Methods:
- A 5-year retrospective study (1991-1996) comparing pediatricians within a single HMO to those in private practice in New Brunswick, NJ.
- Analysis of patient referrals for abdominal pain, focusing on appendicitis, perforated appendicitis, and non-surgical abdominal pain diagnoses.
- Utilized a capitated agreement where HMO consultations were free, removing financial disincentives for referrals.
Main Results:
- Overall appendicitis incidence was 42% (208/492); 58% presented with non-appendicitis abdominal pain.
- Diagnostic accuracy for appendicitis was similar: 46% for HMO pediatricians vs. 40% for private pediatricians.
- Rates of perforated appendicitis (28% HMO vs. 30% private) and negative surgical explorations (8% HMO vs. 9% private) were comparable.
Conclusions:
- Pediatricians within an HMO and private practice demonstrated similar diagnostic accuracy and referral outcomes for appendicitis.
- The study found no evidence that the HMO's capitated agreement led to overuse of consultations or delayed referrals.
- Referral habits and diagnostic judgments were not significantly altered by participation in the HMO, suggesting managed care did not negatively impact care for appendicitis.
Background:
In the last few years, there have been many reports of the rising incidence of late appendicitis and perforated appendicitis. The rise of managed care medicine has been blamed for this, because the health maintenance organizations (HMO) and gatekeepers allegedly want to keep the child away from the surgeon and hospital to save costs.
Methods:
The authors were in a unique position a number of years ago because they had only a single HMO in their area of practice (New Brunswick, NJ) employing 14 pediatricians, and 86 pediatricians were in private practice or on the medical school staff. The HMO had a yearly contract with the pediatric surgeons, and all visits and surgeries were covered by a yearly agreement (capitated agreement). The authors compared the number of children with appendicitis, perforated appendicitis, or just abdominal pain (not requiring surgery), between both groups over a 5-year period (1991 to 1996).
Results:
A total of 492 patients were referred with abdominal pain over a 5-year period. Two hundred eight (42%) had appendicitis, and 284 (58%) had just abdominal pain and eventually were sent home. The HMO pediatricians diagnosed appendicitis accurately in 46% of their patients (55 of 118), and 54% were abdominal pain that was not appendicitis (63 of 118). For the private pediatricians, the percentages were: 40% of their patients had appendicitis (153 of 374), and 60% had abdominal pain without appendicitis (221 of 374). The incidence of perforated appendicitis was similar (28% HMO v 30% private), and the incidence of negative explorations were similar (8% HMO v 9% private).
Conclusions:
The results are very similar in both groups, with a similar percentage of abdominal pain not being appendicitis (60% v 54%). HMO patients did not pay for consultations, and the HMO was not charged for any consultations. However, it does not appear that they overused the consultations for abdominal pain that were not appendicitis. Their accuracy for correct diagnosis of appendicitis was similar to the private group (46% v 40%), and the incidence of perforated appendicitis for both groups was 28% to 30%. The authors cannot draw any conclusions from their experience that HMOs in general do refer patients to surgeons in a timely fashion, and do not delay the referrals to avoid the cost of consultation, because the authors had a capitated agreement with their HMO, and consultations were free. Both groups of pediatricians, the HMO and the private pediatricians, did not realize financial gain or loss by sending children to the pediatric surgeon and were not penalized by sending patients with abdominal pain to the surgeon. On the contrary, their referral habits and judgments were similar and did not appear to change by being part of an HMO.
Related Concept Videos
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four quadrants...
 01:23
Assessment of the Abdomen III: Palpation
 01:25
Assessment of the Abdomen I: Inspection and Auscultation
The abdominal examination is a cornerstone of clinical medicine, serving as a critical tool in diagnosing various gastrointestinal (GI) diseases. It involves a systematic approach that includes inspection and auscultation, each with distinct yet complementary roles in assessing the abdomen. This article will delve into these two primary methods healthcare professionals use to examine the abdomen.
Inspection of the Abdomen
The first step in any abdominal examination is inspection.
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:19
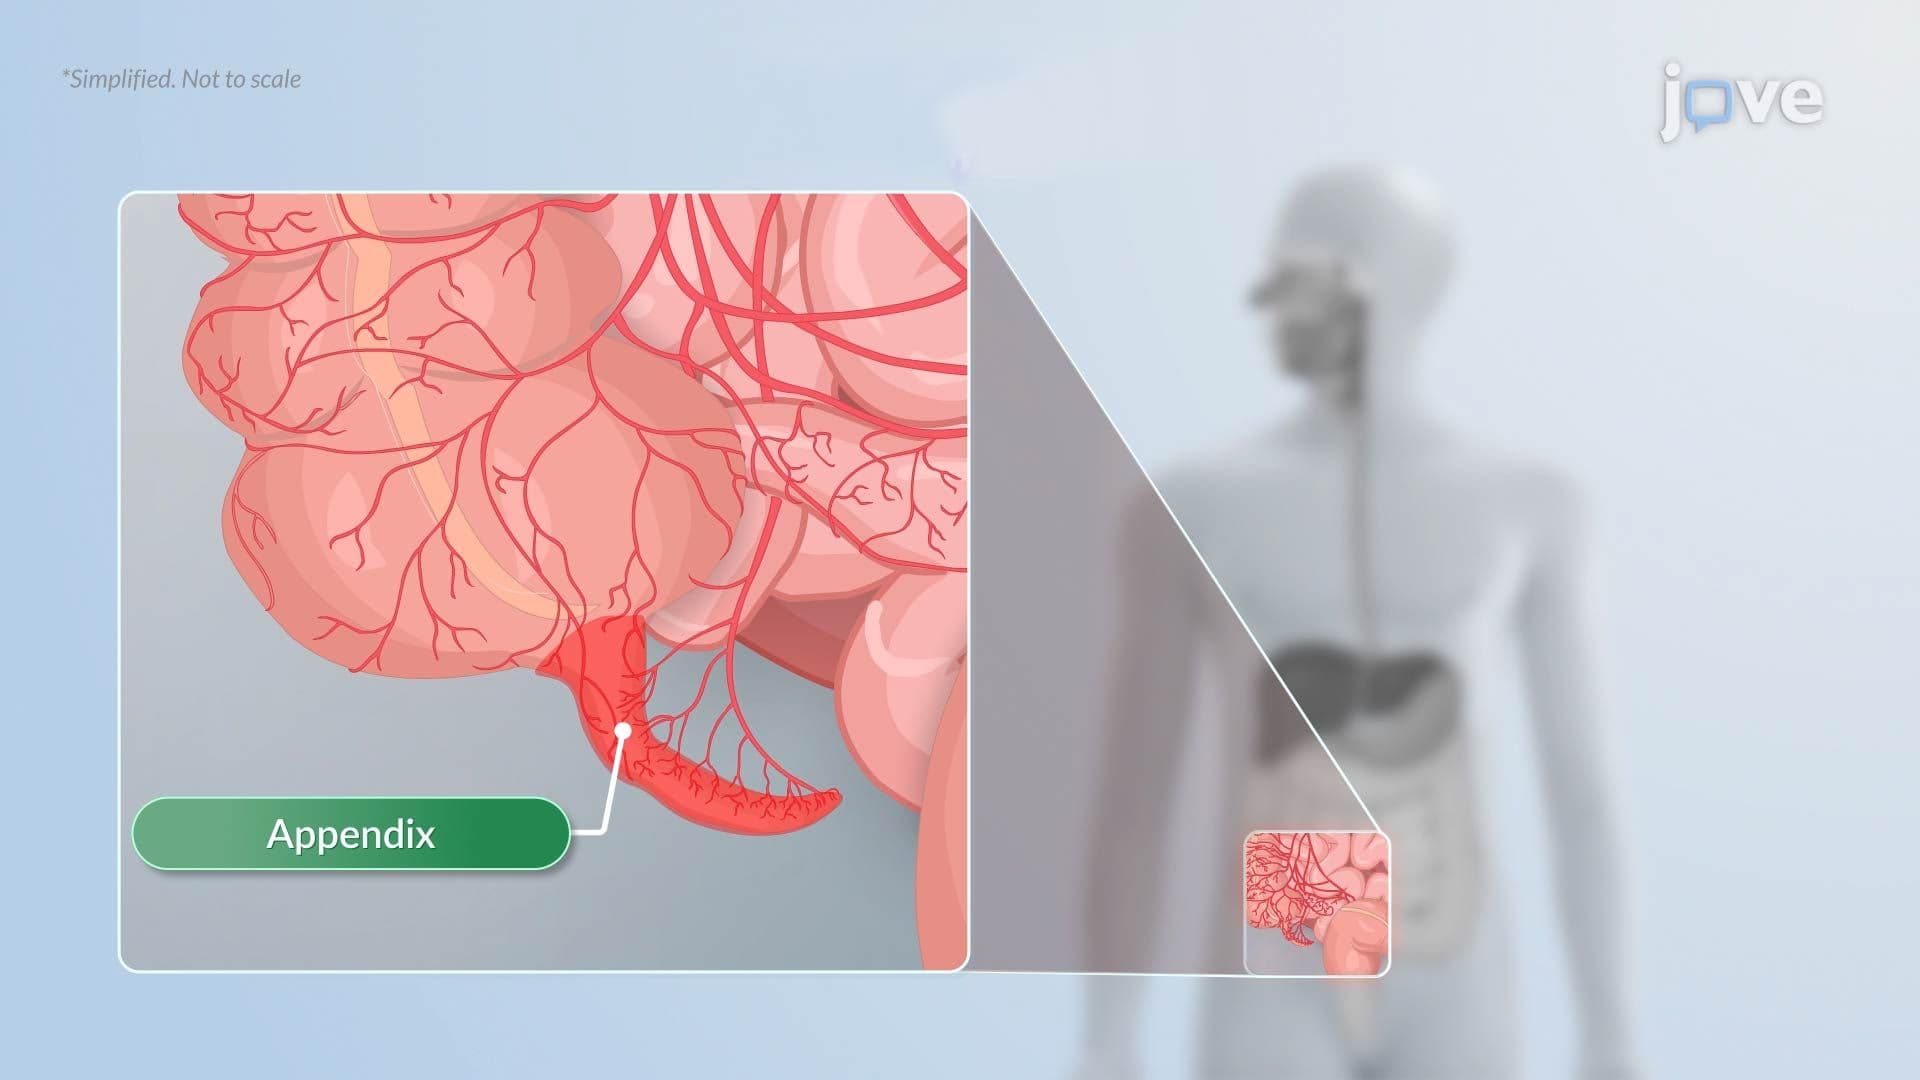
Appendicitis