Related Experiment Video
Updated: Aug 12, 2026


Generation of a Chronic Obstructive Pulmonary Disease Model in Mice by Repeated Ozone Exposure
Published on: August 25, 2017
Exposure of chronic obstructive pulmonary disease patients to particulate matter: relationships between personal and
S T Ebelt1, A J Petkau, S Vedal
1University of British Columbia, School of Occupational and Environmental Hygiene, Vancouver.

Abstract:
Mot time-series studies of particulate air pollution and acute health outcomes assess exposure of the study population using fixed-site outdoor measurements. To address the issue of exposure misclassification, we evaluate the relationship between ambient particle concentrations and personal exposures of a population expected to be at risk of particle health effects. Sampling was conducted within the Vancouver metropolitan area during April-September 1998. Sixteen subjects (non-smoking, ages 54-86) with physician-diagnosed chronic obstructive pulmonary disease (COPD) wore personal PM2.5 monitors for seven 24-hr periods, randomly spaced approximately 1.5 weeks apart. Time-activity logs and dwelling characteristics data were also obtained for each subject. Daily 24-hr ambient PM10 and PM2.5 concentrations were measured at five fixed sites spaced throughout the study region. SO4(2-), which is found almost exclusively in the fine particle fraction and which does not have major indoor sources, was measured in all PM2.5 samples as an indicator of accumulation mode particulate matter of ambient origin. The mean personal and ambient PM2.5 concentrations were 18 micrograms/m3 and 11 micrograms/m3, respectively. In analyses relating personal and ambient measurements, ambient concentrations were expressed either as an average of the values obtained from five ambient monitoring sites for each day of personal sampling, or as the concentration obtained at the ambient site closest to each subject's home. The mean personal to ambient concentration ratio of all samples was 1.75 (range = 0.24 to 10.60) for PM2.5, and 0.75 (range = 0.09 to 1.42) for SO4(2-). Regression analyses were conducted for each subject separately and on pooled data. The median correlation (Pearson's r) between personal and average ambient PM2.5 concentrations was 0.48 (range = -0.68 to 0.83). Using SO4(2-) as the exposure metric, the median r between personal and average ambient concentrations was 0.96 (range = 0.66 to 1.0). Use of the closest ambient site did not improve the median correlation of the group for either PM2.5 or SO4(2-). All pooled analyses resulted in lower correlation coefficients than the median correlation coefficient of individual regressions. Personal SO4(2-) was more highly correlated with all ambient measures than PM2.5. Inclusion of time-activity and dwelling characteristics data did not result in a useful predictive regression model for PM2.5 personal exposure, but improved the model fit from simply regressing against ambient concentration (R2 = 0.27). The model for SO4(2-) was predictive (R2 = 0.82), as personal exposures were largely explained by ambient levels. These results indicate a relatively low correlation between personal exposure and ambient PM2.5 that is not improved by assigning exposure to the closest ambient monitor. The correlation between personal exposure and ambient concentration is high, however, when using SO4(2-), an indicator of accumulation mode particulate matter of ambient origin.
More Related Videos


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease
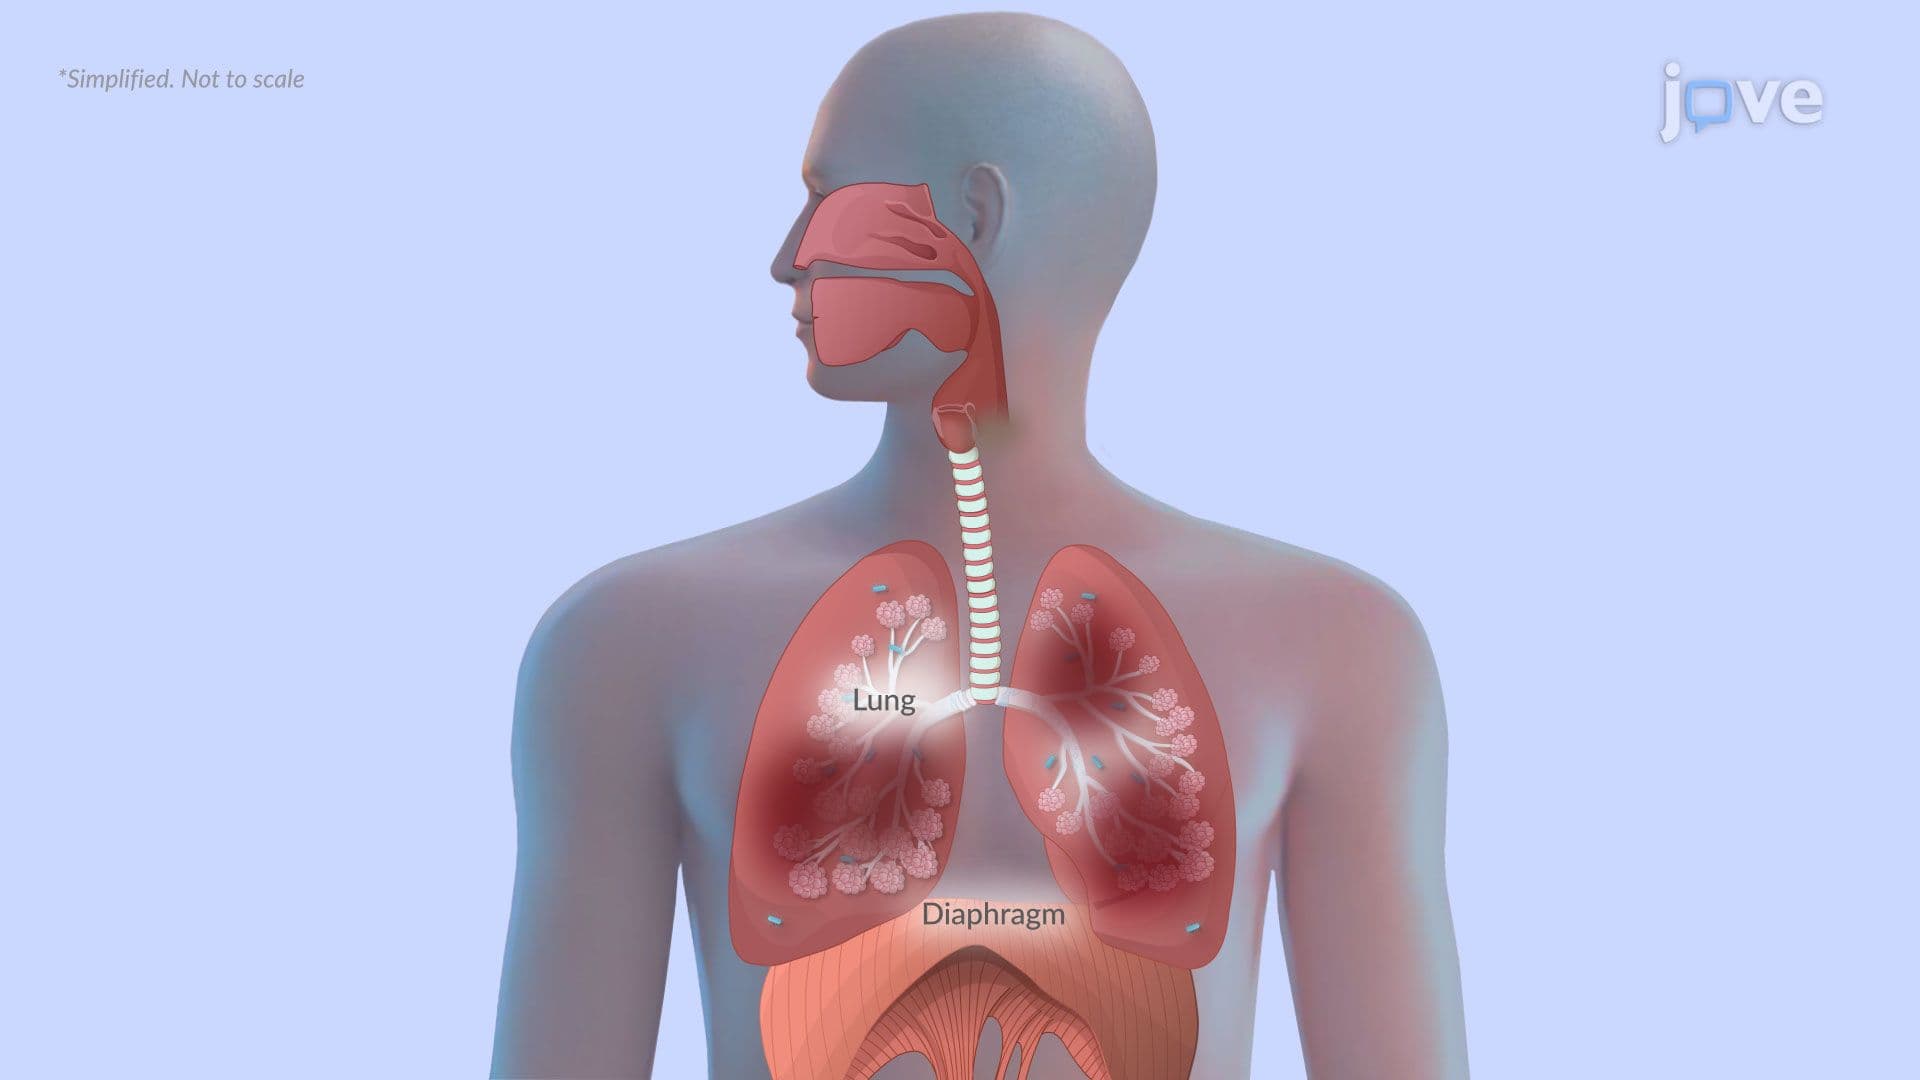
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
Chronic Obstructive Pulmonary Disease I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features