Related Experiment Video
Updated: Aug 27, 2026


Evaluation of Coronary Flow Reserve After Myocardial Ischemia Reperfusion in Rats
Published on: June 28, 2019
Outcome of coronary revascularization in patients on renal dialysis
M Agirbasli1, W S Weintraub, G L Chang
1Andreas Gruentzig Cardiovascular Center, Division of Cardiology, Emory University School of Medicine, Atlanta, Georgia, USA.

Insights
Percutaneous transluminal coronary angioplasty (PTCA) and coronary artery bypass grafting (CABG) show similar high 1-year mortality in renal dialysis patients. Focus should shift to preventing and treating coronary artery disease before revascularization.
Area of Science:
- Cardiology
- Nephrology
- Interventional Cardiology
Background:
- Retrospective studies indicate high mortality and poor outcomes for renal dialysis patients undergoing percutaneous transluminal coronary angioplasty (PTCA) or coronary artery bypass grafting (CABG).
- Renal dialysis patients represent a high-risk population for cardiovascular interventions.
Purpose of the Study:
- To compare mortality and clinical event rates between PTCA and CABG in patients on renal dialysis.
- To evaluate the safety and efficacy of coronary revascularization strategies in this specific patient cohort.
Main Methods:
- A retrospective analysis of 252 renal dialysis patients who underwent PTCA (122) or CABG (130) between 1987 and 1997.
- Comparison of baseline characteristics, angiographic findings, in-hospital outcomes, and 1-year mortality between the PTCA and CABG groups.
Main Results:
- The CABG group had a higher prevalence of left main and 3-vessel coronary artery disease.
- Periprocedure and in-hospital mortality were significantly higher in the CABG group (6.9%) compared to the PTCA group (1.6%).
- One-year mortality rates were similar (23% PTCA vs. 27% CABG), with PTCA patients requiring repeat revascularization more frequently (22% vs. 2%).
Conclusions:
- Both PTCA and CABG can be performed in selected renal dialysis patients with acceptable in-hospital complication rates.
- One-year mortality remains high for dialysis patients following coronary revascularization, underscoring the need for preventative strategies.
- Future efforts should prioritize the prevention and early treatment of coronary artery disease in renal dialysis patients to improve long-term outcomes.
Abstract:
Previous retrospective studies showed high periprocedure mortality rate and poor outcome after percutaneous transluminal coronary angioplasty (PTCA) or coronary artery bypass grafting (CABG) among renal dialysis patients. The purpose of this study was to compare mortality and clinical event rates in renal dialysis patients after PTCA or CABG. We identified 252 patients from the Emory Cardiovascular Database who were on dialysis and who received PTCA (122 patients) or CABG (130 patients) at Emory University Hospital and Crawford W. Long Hospital between March 1987 and December 1997. Baseline and angiographic characteristics, in-hospital, and 1-year outcome were compared between the 2 groups. Left main disease and 3-vessel coronary artery disease were significantly more common in the CABG group. There was a higher periprocedure and in-hospital mortality in the CABG group (6.9% vs 1.6%, p = 0.04). Patients in the PTCA group underwent repeat revascularization 11 times more frequently within 1 year (22% vs 2%). At 1 year, mortality was 23% in the PTCA group and 27% in the CABG group, with no statistical difference between the 2 groups. This nonrandomized comparison reveals that PTCA and CABG can be performed in selected renal dialysis patients with an acceptable in-hospital major complication rate; however, 1-year mortality remains high in dialysis patients after coronary revascularization. Therefore, attempts at improving outcome in dialysis patients should focus on the prevention and treatment of coronary artery disease before they require coronary revascularization.


Related Concept Videos
 01:15
Renal Drug Excretion: Overview
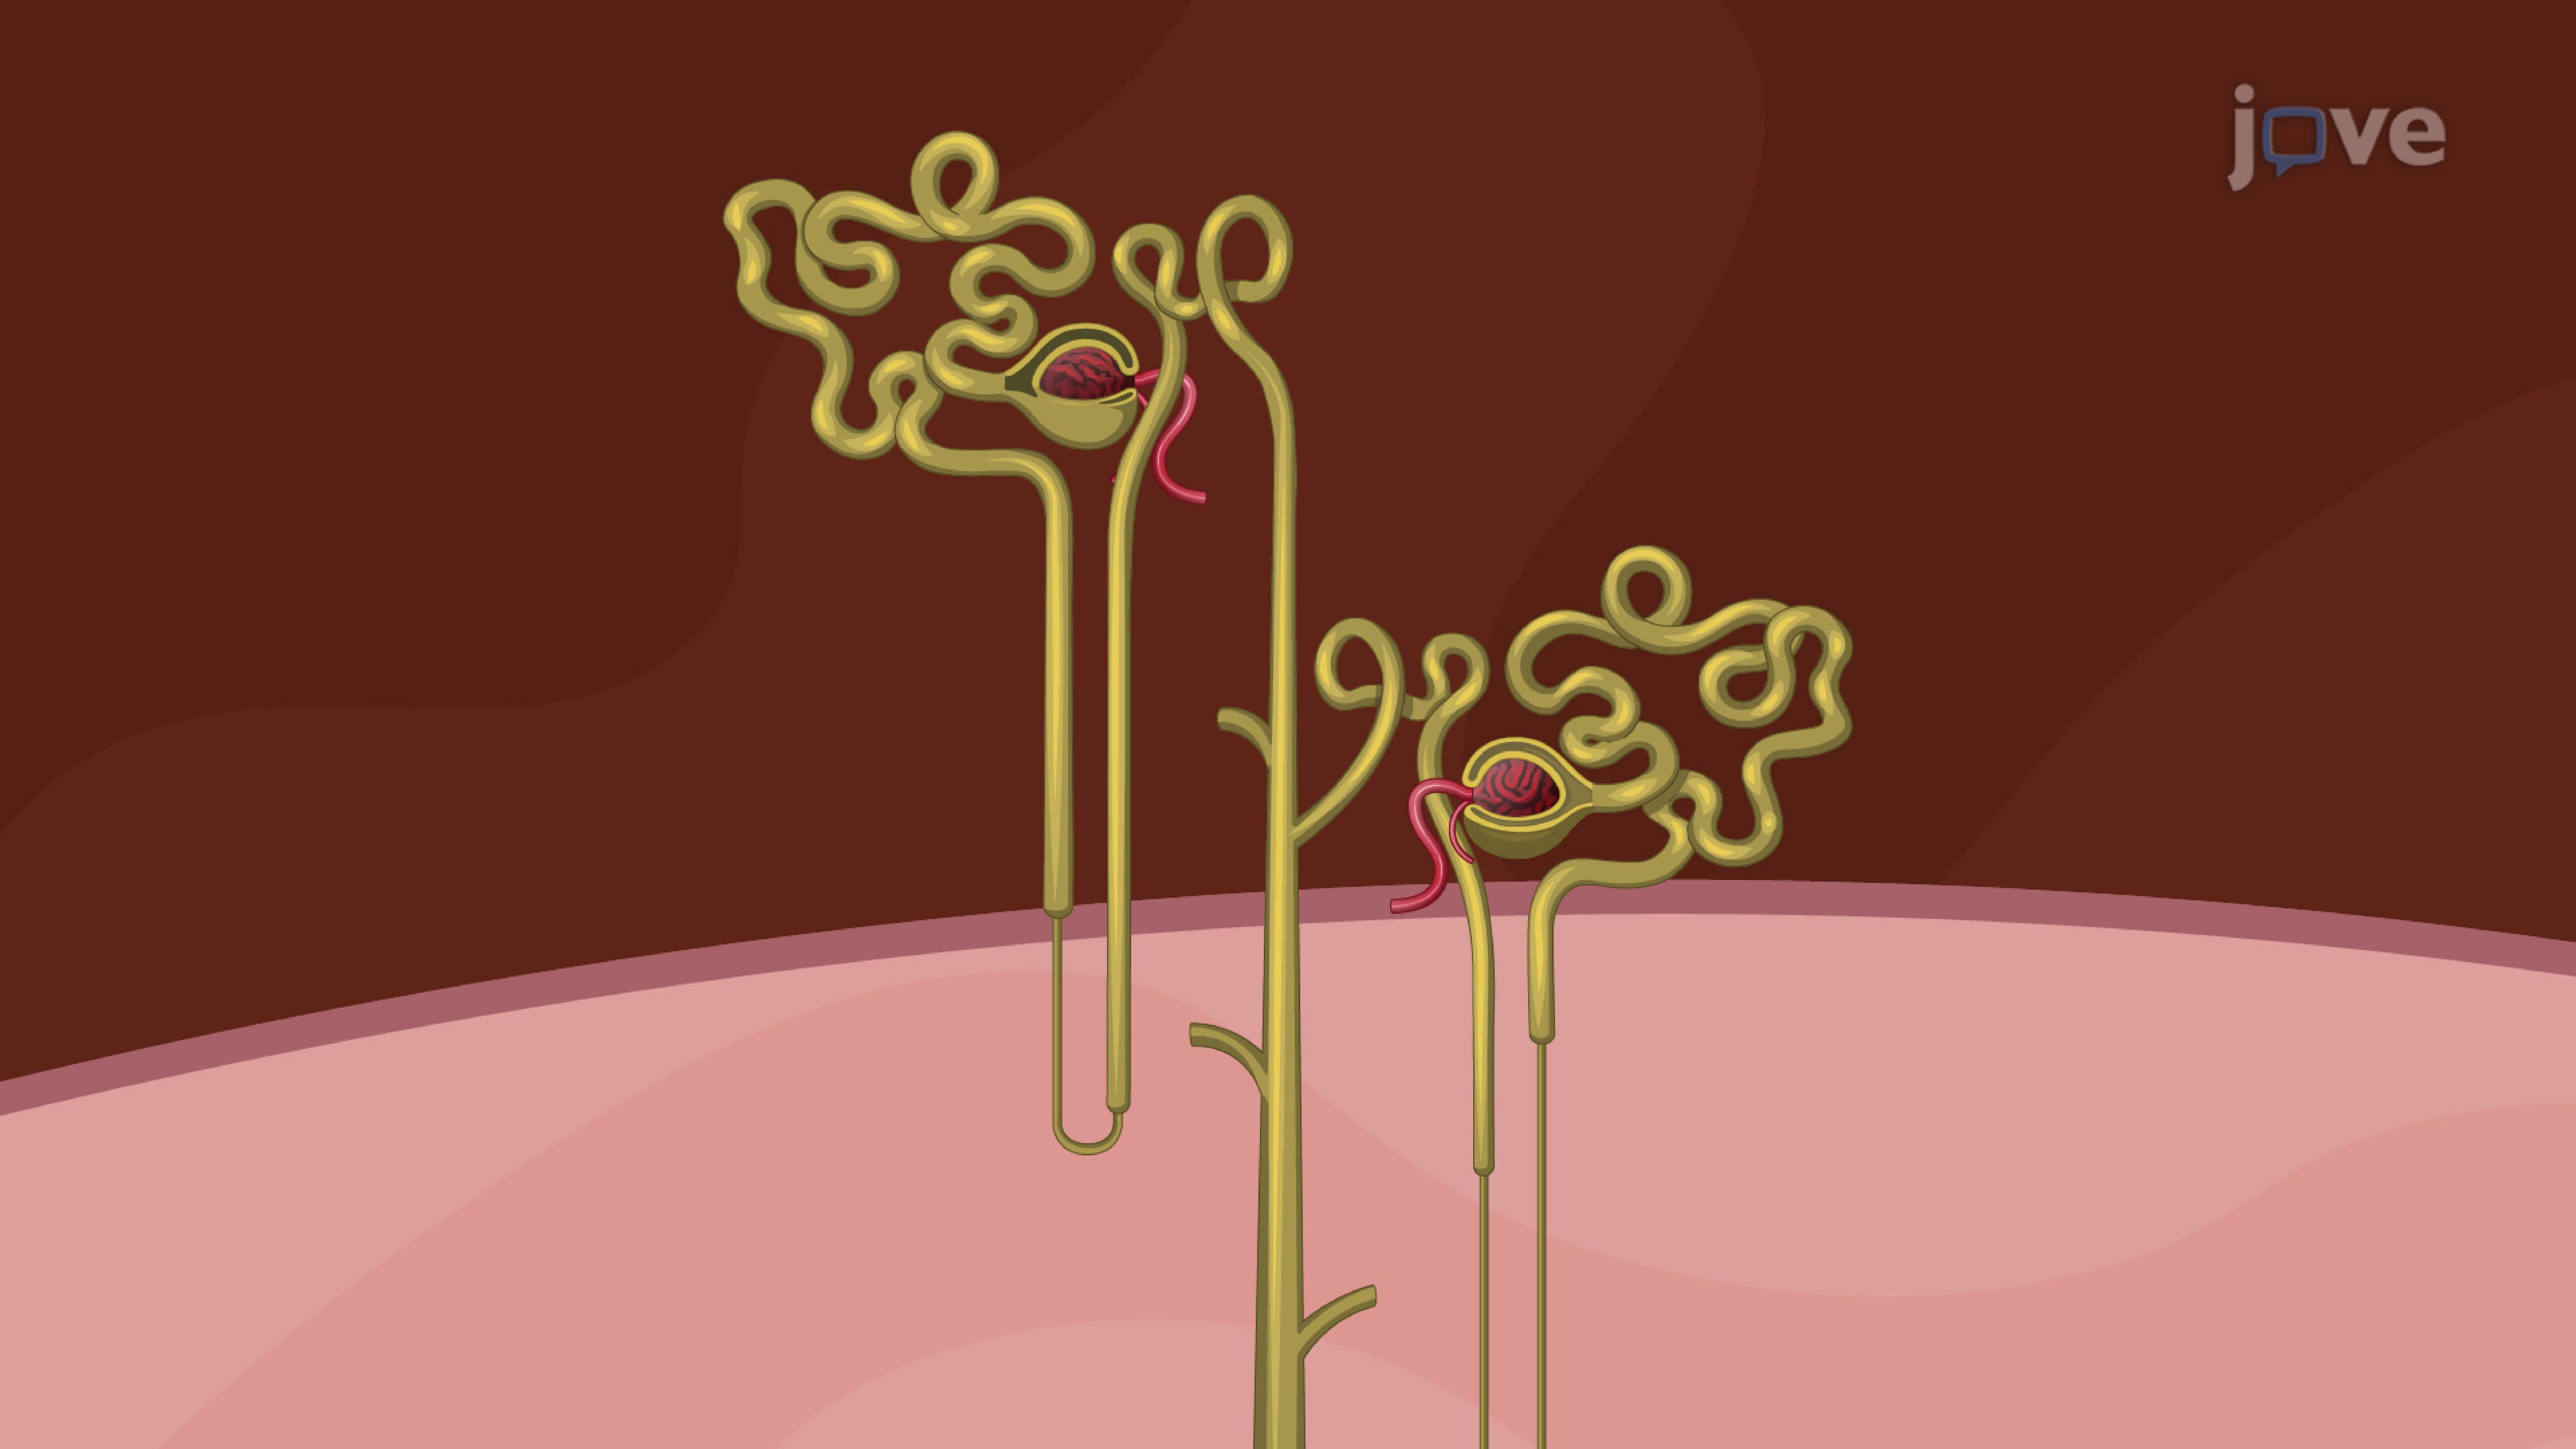
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:30
Continuous Renal Replacement Therapy
 01:24
Hemodialysis II: Procedure and Complications
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention