Related Experiment Video
Updated: Oct 13, 2026

Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
A survey of exercise testing: methods, utilization, interpretation, and safety in the VAHCS

Background:
Healthcare organizations are being graded in terms of their adherence to practice guidelines. The authors sought information on practice patterns of exercise testing within the Veterans Affairs Health Care System (VAHCS) to determine how well current practice patterns adhere to current guidelines. In addition, we sought to update past surveys to determine methods, indications, utilization of alternative diagnostic modalities, criteria for interpretation, safety, and physician supervision of exercise testing within the VAHCS.
Methods:
Questionnaires were sent to 72 of the largest Veterans Affairs Medical Centers with cardiology divisions. The centers were queried regarding volume and type of exercise testing (standard, nuclear, and echocardiographic), indications, safety, protocols used, and criteria for interpretation.
Results:
Seventy-one questionnaires were returned, comprising a total of 75,828 exercise tests performed within the last year. Virtually all indications for exercise testing fit the American Heart Association/American College of Cardiology (AHA/ACC) guidelines Class I criteria; 46% of patients were tested for the evaluation of chest pain; 14% were tested to evaluate patients at high risk for coronary artery disease; 10% were preoperative evaluations; and 8% were post-myocardial infarction evaluations. The most commonly used diagnostic test was the standard exercise electrocardiogram; a patient was five times more likely to undergo a standard exercise electrocardiogram or nuclear exercise test than an exercise or pharmacologic echocardiogram. The largest proportion of centers (49%) used 1.0-mm horizontal or downsloping ST depression as a criterion for an abnormal test, although 22% considered 1.5-mm upsloping ST depression to be abnormal, and 25% relied on a treadmill score. Seventy-eight percent of respondents used the treadmill, and of these, 82% used the Bruce or modified Bruce protocol. Four major cardiac events were reported (three myocardial infarctions, one sustained ventricular tachycardia) representing an event rate of 1.2/10,000. A physician was present during 73% of all standard exercise tests; 21% of respondents reported that a physician was required to be present "only for high-risk patients."
Conclusion:
Indications for exercise testing are in close agreement with the AHA/ACC guidelines; thus, the test continues to have an important role in diagnosis and prognosis among patients with or suspected of having coronary artery disease. The exercise test is an extremely safe procedure, with an event rate similar to other recent surveys. However, a great deal of variation exists in terms of criteria for abnormal results and whether physician presence is required during exercise testing.
Related Concept Videos
 01:26
Exercise Stress Test
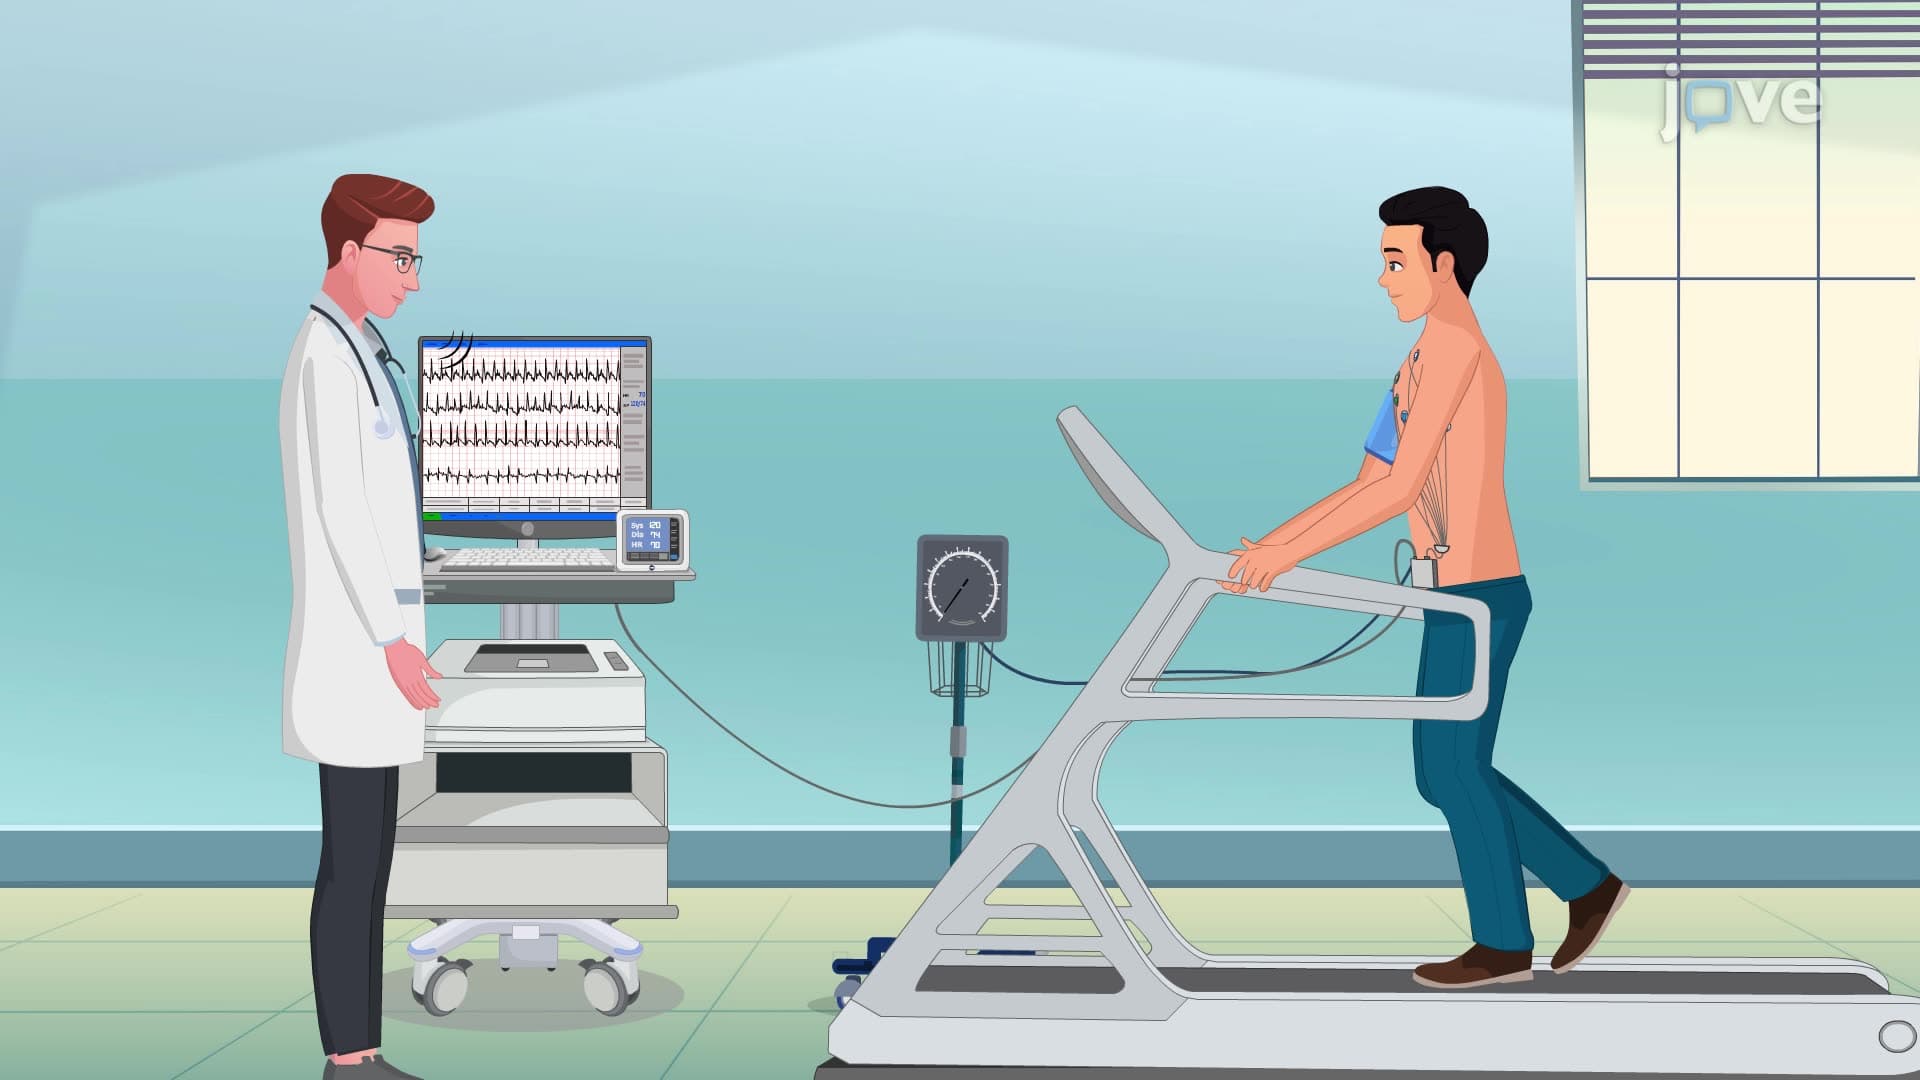
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: