
[Percutaneous treatment of multiple heart defects]
M Ledesma1, F D Gómez, C Alva Espinosa
1Departamento de Hemodinamia, Hospital de Cardiología Centro Médico Nacional Siglo XXI, IMSS, México D.F.

Insights
Percutaneous interventions effectively treat multiple congenital heart defects in children. This minimally invasive approach offers a viable alternative for complex cardiac conditions, leading to asymptomatic outcomes.
Area of Science:
- Pediatric Cardiology
- Interventional Cardiology
- Congenital Heart Disease
Background:
- Multiple congenital heart defects (CHDs) present complex therapeutic challenges.
- Percutaneous interventions are increasingly utilized for various cardiac conditions.
Purpose of the Study:
- To evaluate the feasibility and outcomes of percutaneous interventions in pediatric patients with multiple CHDs.
- To assess the efficacy of these minimally invasive procedures in improving hemodynamic parameters.
Main Methods:
- Retrospective review of 6 pediatric cases with multiple CHDs.
- Procedures included occlusion of patent ductus arteriosus (PDA), balloon angioplasty for coarctation of the aorta (AC), pulmonary valve stenosis (PVS), and aortic stenosis (AE).
- One case of Shone's syndrome involved angioplasty and valvuloplasty.
Main Results:
- Successful occlusion of PDA in all patients using coils or occluders.
- Significant reduction in valvular gradients post-intervention: AC (46 to 9 mmHg), PVS (110 to 10 mmHg), AE (40 to 14 mmHg).
- One patient with Shone's syndrome underwent successful angioplasty and valvuloplasty, with subsequent surgical repair for subaortic stenosis.
Conclusions:
- Percutaneous intervention is a feasible and effective treatment modality for select pediatric patients with multiple CHDs.
- Minimally invasive approaches can lead to significant hemodynamic improvement and positive clinical outcomes.
- These interventions can be safely performed in conjunction with surgical management for complex CHD cases.
Abstract:
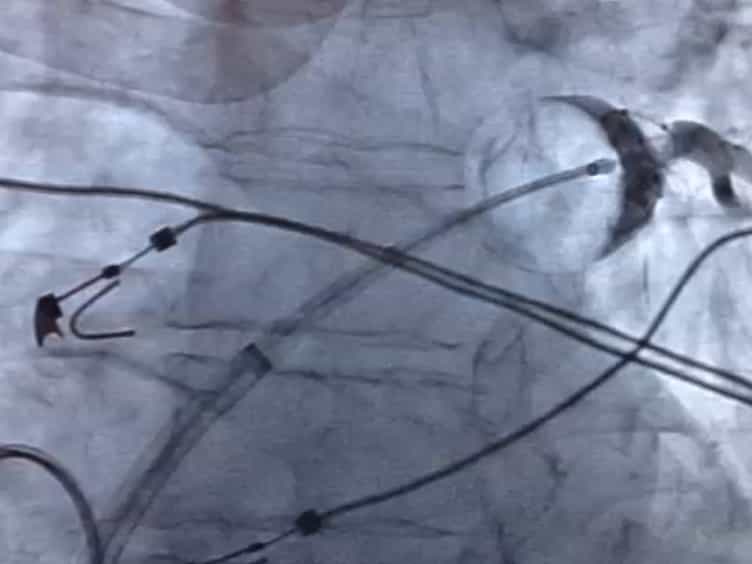
We describe our experience in 6 cases with multiple congenital heart defects treated by percutaneous intervention. Their age ranged from 2.3 to 10 years (mean 6.1), with follow-up from 1 to 84 months (mean 28.8). Two cases had coarctation of the aorta (AC) and persistent ductus arteriosus (PDA). Two patients had pulmonary valve stenosis (PVS) and PDA, one case with aortic stenosis (AE) and PDA and one case with AC, mitral stenosis and subaortic stenosis (Shone's Syndrome). Ductus arteriosus was occluded in all patients with Gianturco coils or Rashkind occluder. The valvular gradient post balloon decreased in cases with AC from 46 to 9 mmHg, with PVS from 110 to 10 mmHg and with AE from 40 to 14 mmHg. In a 8 year old boy with Shone's syndrome, we performed angioplasty of aortic coarctation, mitral valvuloplasty with Inoue catheter. He was referred to surgery for subaortic repair stenosis. All are asymptomatic at follow-up. In conclusion; percutaneous intervention is possible in patients with multiple congenital heart defects.


Related Concept Videos
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:29
Cardiomyopathy V: Interprofessional Care