Related Experiment Video
Updated: Aug 17, 2026
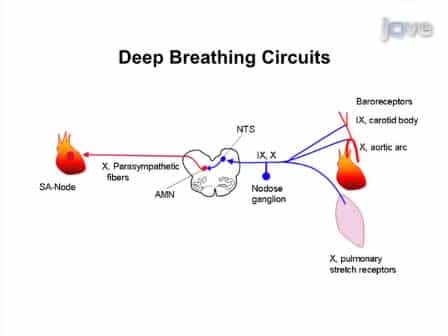

Quantitative Autonomic Testing
Published on: July 19, 2011
The American Society of Anesthesiologists' Physical Status: category V revisited
A Sidi1, E B Lobato, J A Cohen
1Department of Anesthesiology, University of Florida College of Medicine, Gainesville 32610-0254, USA.

Study Objective:
To determine the perioperative mortality and intraoperative morbidity according to operative procedure and postoperative period for American Society of Anesthesiologists' Physical Status (ASA-PS) V category patients.
Design:
Retrospective chart review.
Setting:
University-affiliated medical center.
Measurements And Main Results:
The perioperative records of 111,051 consecutive anesthetized patients, from 1990 to 1997 were retrospectively reviewed. Data were collected and analyzed to determine ASA-PS classification, perioperative mortality, intraoperative morbidity, mortality according to operative procedure, and mortality postoperatively for ASA-PS V patients. At the University of Florida, 0.37% of our patients were ASA-PS V. Most had anesthesia for abdominal (26.2%), cardiothoracic (27.9%), cranial (12.3%), or diagnostic procedures (11.6%). The overall mortality rate decreased in 1993-1995 and 1995-1997, compared to 1990-1993, from 64.16 +/- 4.53 (+/-SD) to 46.7 +/- 9.5 and 56.8 +/- 1.1, respectively. The mortality rate decreased in the immediate postoperative period from 15.7 +/- 5.1 to 4.6 +/- 1.5 and 4.1 +/- 2. 8 intraoperatively, and from 42.5 +/- 1.8% to 22.1 +/- 5.1 and 26.8 +/- 1.8 within 24 hours postoperatively. The mortality rate increased from 0 +/- 0 to 7.4 +/- 3.9 and 15.5 +/- 4.9 (p < 0.05 for all), during the late postoperative period (>2 weeks, during hospitalization). Intraoperative morbidity (untoward events) was significantly higher for ASA-PS V patients than for ASA-PS IV patients only in emergency cases (11.1 +/- 4.8% vs. 5.5 +/- 1.4%).
Conclusions:
The ASA-PS V classification is determined subjectively rather than objectively, and can be variable within its parameters, depending on the individual interpretation of ASA classification, patient population, case severity, surgical and anesthesia factors, and the year of the study. Even though immediate perioperative mortality decreased in our patient population, late postoperative mortality increased during the same time period, possibly demonstrating a shift in mortality time rather than an absolute decrease in overall mortality. Although the ASA-PS V category was never intended to be a predictor of outcome, it correlates with perioperative mortality as well as or even better than other classifications of mortality and morbidity. The decreased mortality in the ASA-PS V patient population may be related to different factors, which are beyond the scope of this study.


Related Concept Videos
 01:17
Pulse amplitude and quality
A weak or absent pulse may indicate reduced cardiac output or poor left ventricular contraction, which can be signs of cardiovascular dysfunction or...
 01:14
SBAR II: Application of SBAR
SBAR Report from a Nurse to a Health Care Provider
S: "Hello, Dr. Smith. This is Jane, RN, from the Med Surg unit. I am calling to tell you about Ms. White in Room 210, who is experiencing increased pain and redness at her incision site. Her recent...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:22
Stages of General Anesthesia
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above the...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management