Related Experiment Video
Updated: Jul 5, 2026
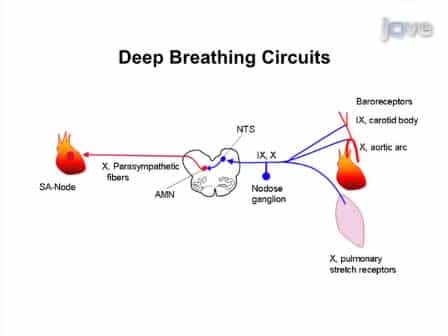

Quantitative Autonomic Testing
Published on: July 19, 2011
Hypertensive emergencies
1Department of Medicine, Weill Medical College of Cornell University, New York Presbyterian Hospital, NY, USA.

A hypertensive emergency is a situation in which uncontrolled hypertension is associated with acute end-organ damage. Most patients presenting with hypertensive emergency have chronic hypertension, although the disorder can present in previously normotensive individuals, particularly when associated with pre-eclampsia or acute glomerulonephritis. The pathophysiological mechanisms causing acute hypertensive endothelial failure are complex and incompletely understood but probably involve disturbances of the renin-angiotensin-aldosterone system, loss of endogenous vasodilator mechanisms, upregulation of proinflammatory mediators including vascular cell adhesion molecules, and release of local vasoconstrictors such as endothelin 1. Magnetic resonance imaging has demonstrated a characteristic hypertensive posterior leucoencephalopathy syndrome predominantly causing oedema of the white matter of the parietal and occipital lobes; this syndrome is potentially reversible with appropriate prompt treatment. Generally, the therapeutic approach is dictated by the particular presentation and end-organ complications. Parenteral therapy is generally preferred, and strategies include use of sodium nitroprusside, beta-blockers, labetelol, or calcium-channel antagonists, magnesium for pre-eclampsia and eclampsia; and short-term parenteral anticonvulsants for seizures associated with encephalopathy. Novel therapies include the peripheral dopamine-receptor agonist, fenoldapam, and may include endothelin-1 antagonists.
A hypertensive emergency is a situation in which uncontrolled hypertension is associated with acute end-organ damage. Most patients presenting with hypertensive emergency have chronic hypertension, although the disorder can present in previously normotensive individuals, particularly when associated with pre-eclampsia or acute glomerulonephritis. The pathophysiological mechanisms causing acute hypertensive endothelial failure are complex and incompletely understood but probably involve disturbances of the renin-angiotensin-aldosterone system, loss of endogenous vasodilator mechanisms, upregulation of proinflammatory mediators including vascular cell adhesion molecules, and release of local vasoconstrictors such as endothelin 1. Magnetic resonance imaging has demonstrated a characteristic hypertensive posterior leucoencephalopathy syndrome predominantly causing oedema of the white matter of the parietal and occipital lobes; this syndrome is potentially reversible with appropriate prompt treatment. Generally, the therapeutic approach is dictated by the particular presentation and end-organ complications. Parenteral therapy is generally preferred, and strategies include use of sodium nitroprusside, beta-blockers, labetelol, or calcium-channel antagonists, magnesium for pre-eclampsia and eclampsia; and short-term parenteral anticonvulsants for seizures associated with encephalopathy. Novel therapies include the peripheral dopamine-receptor agonist, fenoldapam, and may include endothelin-1 antagonists.


Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart beats)...
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:17
Measurement of Blood Pressure
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:28
Hypertension I: Introduction