Investigation and outcome of neonatal hepatitis in infants with hypopituitarism
Related Experiment Video
Updated: Oct 13, 2026
Isolation of Neonatal Extrahepatic Cholangiocytes
Published on: June 5, 2014
C H Spray1, P Mckiernan, K E Waldron
1Liver Unit, Birmingham Children's Hospital, NHS Trust, UK.

Insights
Congenital hypopituitarism can cause neonatal hepatitis. Prompt diagnosis and hormone replacement therapy (thyroxine, hydrocortisone, growth hormone) improve liver outcomes in infants.
Area of Science:
- Pediatrics
- Endocrinology
- Hepatology
Background:
- Congenital hypopituitarism is a known cause of neonatal hepatitis.
- Diagnosis can be challenging even with clinical suspicion.
Purpose of the Study:
- To review the natural history and outcomes of infants with neonatal hepatitis secondary to hypopituitarism.
- To highlight the importance of timely diagnosis and treatment.
Main Methods:
- Retrospective review of 12 infants with neonatal hepatitis and hypopituitarism.
- Clinical assessment including dysmorphism, optic nerve hypoplasia, micropenis, and hypoglycemia.
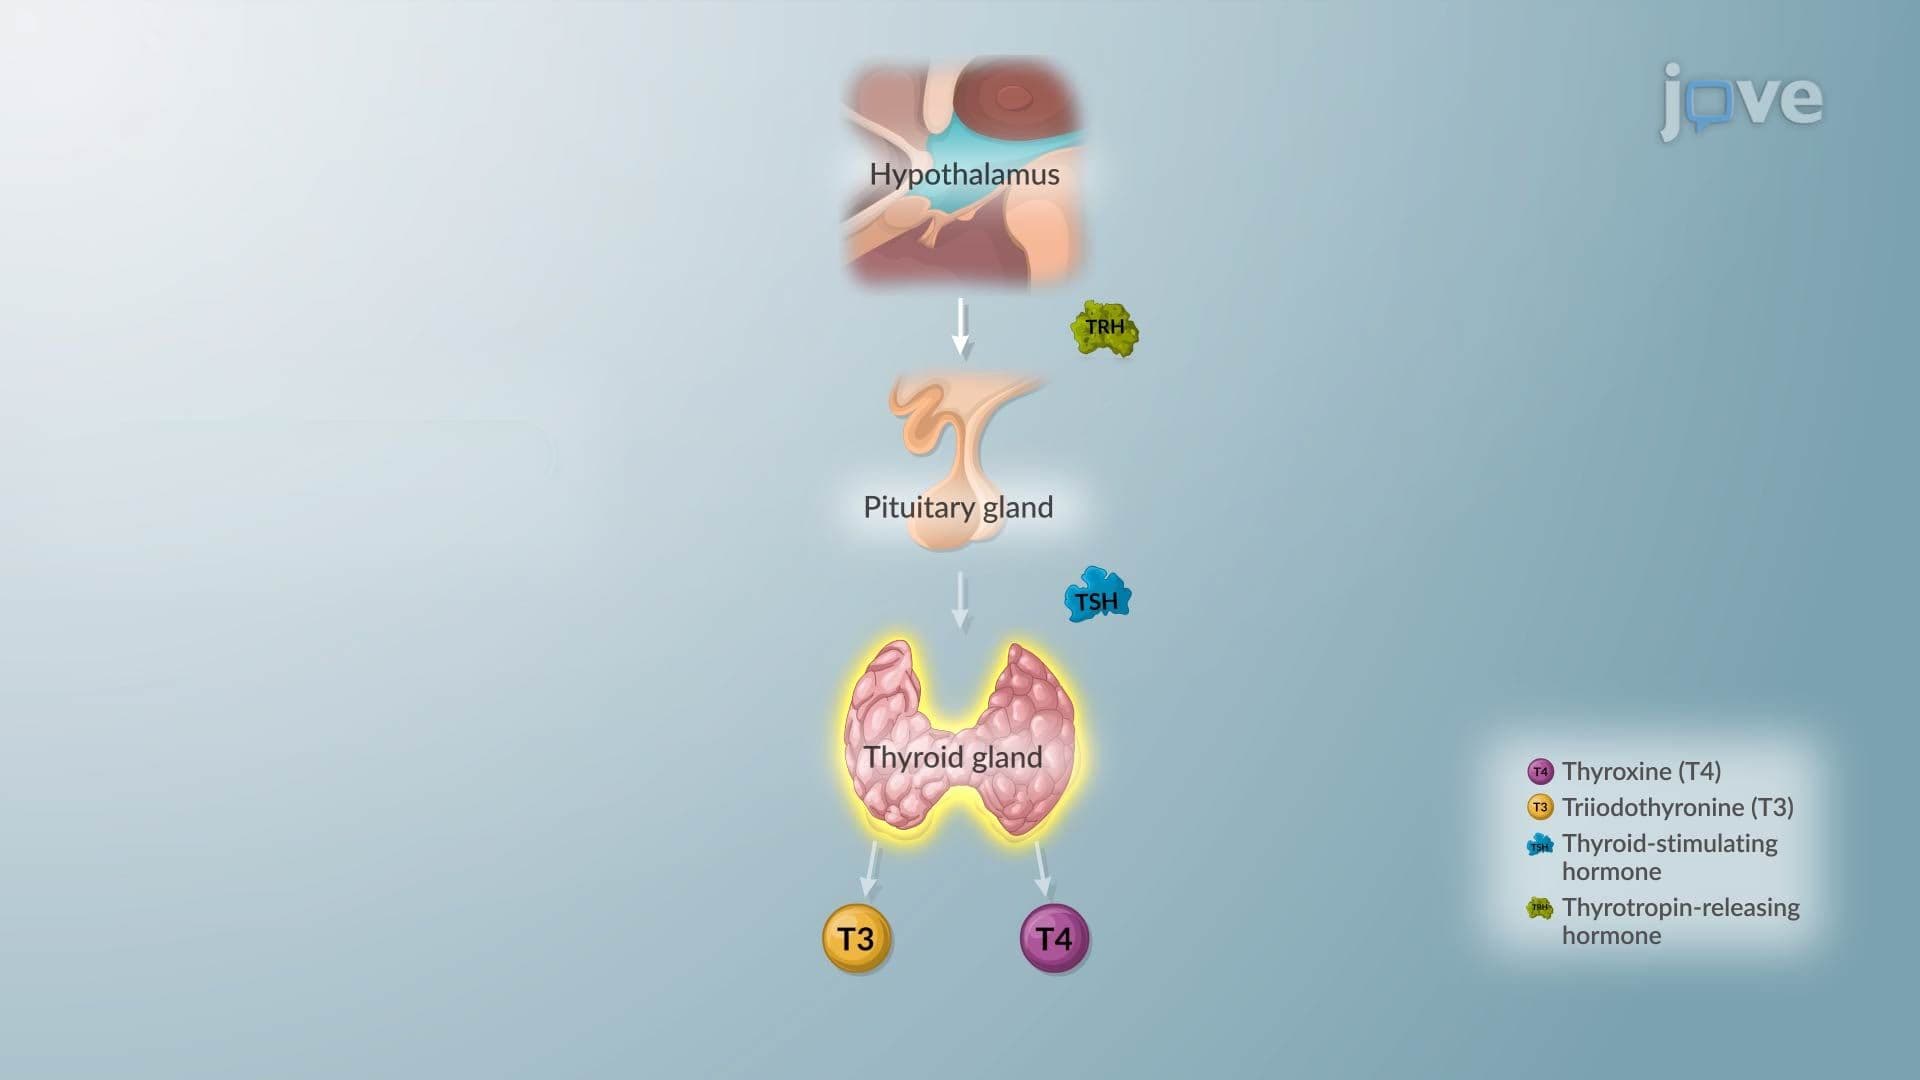
- Endocrine investigations: free thyroxine (T4), thyroid-stimulating hormone (TSH), and serum cortisol levels.
Main Results:
- Hepatitis resolved in 9/12 infants within 6 weeks of hormone replacement therapy (thyroxine, hydrocortisone, growth hormone).
- Two infants had spontaneous resolution before treatment.
- One infant with delayed treatment developed cirrhosis and portal hypertension, requiring liver transplantation.
Conclusions:
- Hypopituitarism should be considered in infants with unexplained neonatal hepatitis.
- Delayed diagnosis and treatment are linked to persistent liver dysfunction and irreversible liver disease.
Unlabelled:
Congenital hypopituitarism is a recognized cause of neonatal hepatitis, but the diagnosis may be difficult to establish even if clinically suspected. In order to determine the natural history of this disorder, the outcome of 12 infants with neonatal hepatitis secondary to hypopituitarism is reviewed. The clinical diagnosis of hypopituitarism was established on a combination of features, which include dysmorphism (4 infants), optic nerve hypoplasia (8 infants), micropenis (5 male infants) and recurrent hypoglycaemia (blood glucose < 2.4 mmol/l (8 infants)). Endocrine investigation revealed low free thyroxine (T4) levels (< 10 pmol/l), with normal thyroid stimulating hormone (TSH) levels (0.4-4.5 mU/l) (11 infants), and serum cortisol levels which were inappropriately low (< 200 nmol/l). In 9 of 12 infants, liver disease resolved within 6 wk following treatment with thyroxine, hydrocortisone and, where appropriate, growth hormone, including Cases 9 and 1 in whom diagnosis and treatment were delayed until 3 mo and 3 y of age, respectively. Liver disease resolved spontaneously in two infants prior to starting hormone replacement therapy (Cases 11, 12), and one male infant (Case 10), in whom the diagnosis and hormone replacement therapy were delayed until 5 y of age, developed cirrhosis and portal hypertension and later underwent liver transplantation.
Conclusion:
The diagnosis of hypopituitarism should always be considered in infants with unexplained neonatal hepatitis. Delay in diagnosis and appropriate treatment was associated with persistently abnormal liver function tests and may lead to irreversible liver disease.