Bladder outlet obstruction nomogram for women with lower urinary tract symptomatology
Related Experiment Video
Updated: Aug 13, 2026

Nerve-sparing Mid-urethral Obstruction (NeMO) in Female Small Rodents
Published on: April 25, 2017
1Weill Medical College, Cornell University, New York, New York, USA.

The aim of our study was to construct a bladder outlet obstruction nomogram for women with lower urinary tract symptoms. A urodynamic database of 600 consecutive women was reviewed. Bladder outlet obstruction, utilizing strict diagnostic criteria, was diagnosed in 50 (8.3%) patients. A comparison of patient characteristics, uroflowmetry, and detrusor pressure-uroflow studies was carried out between the obstructed patients (mean age, 64.4 +/- 17.6 years) and 50 age-matched unobstructed controls (mean age, 64.8 +/- 10.7 years). Maximum flow rates were significantly higher in free uroflow studies (free Qmax) than in pressure-flow studies (Qmax), in both obstructed (9.3 +/- 3.7 versus 5.7 +/- 3.6 mL/s, respectively. P = 2. 6 10(-6)) and unobstructed (25.6 +/- 11.2 versus 11.8 +/- 5.9 mL/s, respectively. P = 8.7 10(-12)) patients. Comparison of detrusor pressure at maximum flow (pdet.Qmax) and maximum detrusor pressure during voiding (pdet.max) values did not reveal significant differences, in both obstructed (39.3 +/- 18.4 versus 49.7 +/- 25.5 cm H(2)O, respectively) and unobstructed (16.5 +/- 8.4 versus 20.6 +/- 9.2 cm H(2)O, respectively) patients. Further statistical analysis was carried out to construct bladder outlet obstruction nomogram. The nomogram classifies any pair of values of free Qmax and pdet.max into one of the following four zones: no obstruction, mild obstruction, moderate obstruction, and severe obstruction. Of the 50 obstructed women, 34 (68%) were classified by the nomogram as mildly, 12 (24%) as moderately, and 4 (8%) as severely obstructed. A positive correlation was found between subjective severity of the symptoms (assessed by the AUA Symptom Index score) and the four nomogram zones. In conclusion, the nomogram makes it possible to differentiate between obstructed and unobstructed women and between various degrees of obstruction. We believe the nomogram may also serve as an instrument to assess treatment outcomes.
The aim of our study was to construct a bladder outlet obstruction nomogram for women with lower urinary tract symptoms. A urodynamic database of 600 consecutive women was reviewed. Bladder outlet obstruction, utilizing strict diagnostic criteria, was diagnosed in 50 (8.3%) patients. A comparison of patient characteristics, uroflowmetry, and detrusor pressure-uroflow studies was carried out between the obstructed patients (mean age, 64.4 +/- 17.6 years) and 50 age-matched unobstructed controls (mean age, 64.8 +/- 10.7 years). Maximum flow rates were significantly higher in free uroflow studies (free Qmax) than in pressure-flow studies (Qmax), in both obstructed (9.3 +/- 3.7 versus 5.7 +/- 3.6 mL/s, respectively. P = 2. 6 10(-6)) and unobstructed (25.6 +/- 11.2 versus 11.8 +/- 5.9 mL/s, respectively. P = 8.7 10(-12)) patients. Comparison of detrusor pressure at maximum flow (pdet.Qmax) and maximum detrusor pressure during voiding (pdet.max) values did not reveal significant differences, in both obstructed (39.3 +/- 18.4 versus 49.7 +/- 25.5 cm H(2)O, respectively) and unobstructed (16.5 +/- 8.4 versus 20.6 +/- 9.2 cm H(2)O, respectively) patients. Further statistical analysis was carried out to construct bladder outlet obstruction nomogram. The nomogram classifies any pair of values of free Qmax and pdet.max into one of the following four zones: no obstruction, mild obstruction, moderate obstruction, and severe obstruction. Of the 50 obstructed women, 34 (68%) were classified by the nomogram as mildly, 12 (24%) as moderately, and 4 (8%) as severely obstructed. A positive correlation was found between subjective severity of the symptoms (assessed by the AUA Symptom Index score) and the four nomogram zones. In conclusion, the nomogram makes it possible to differentiate between obstructed and unobstructed women and between various degrees of obstruction. We believe the nomogram may also serve as an instrument to assess treatment outcomes.


Related Concept Videos
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:28
Urinary Tract Calculi V: Nursing Management
 01:19
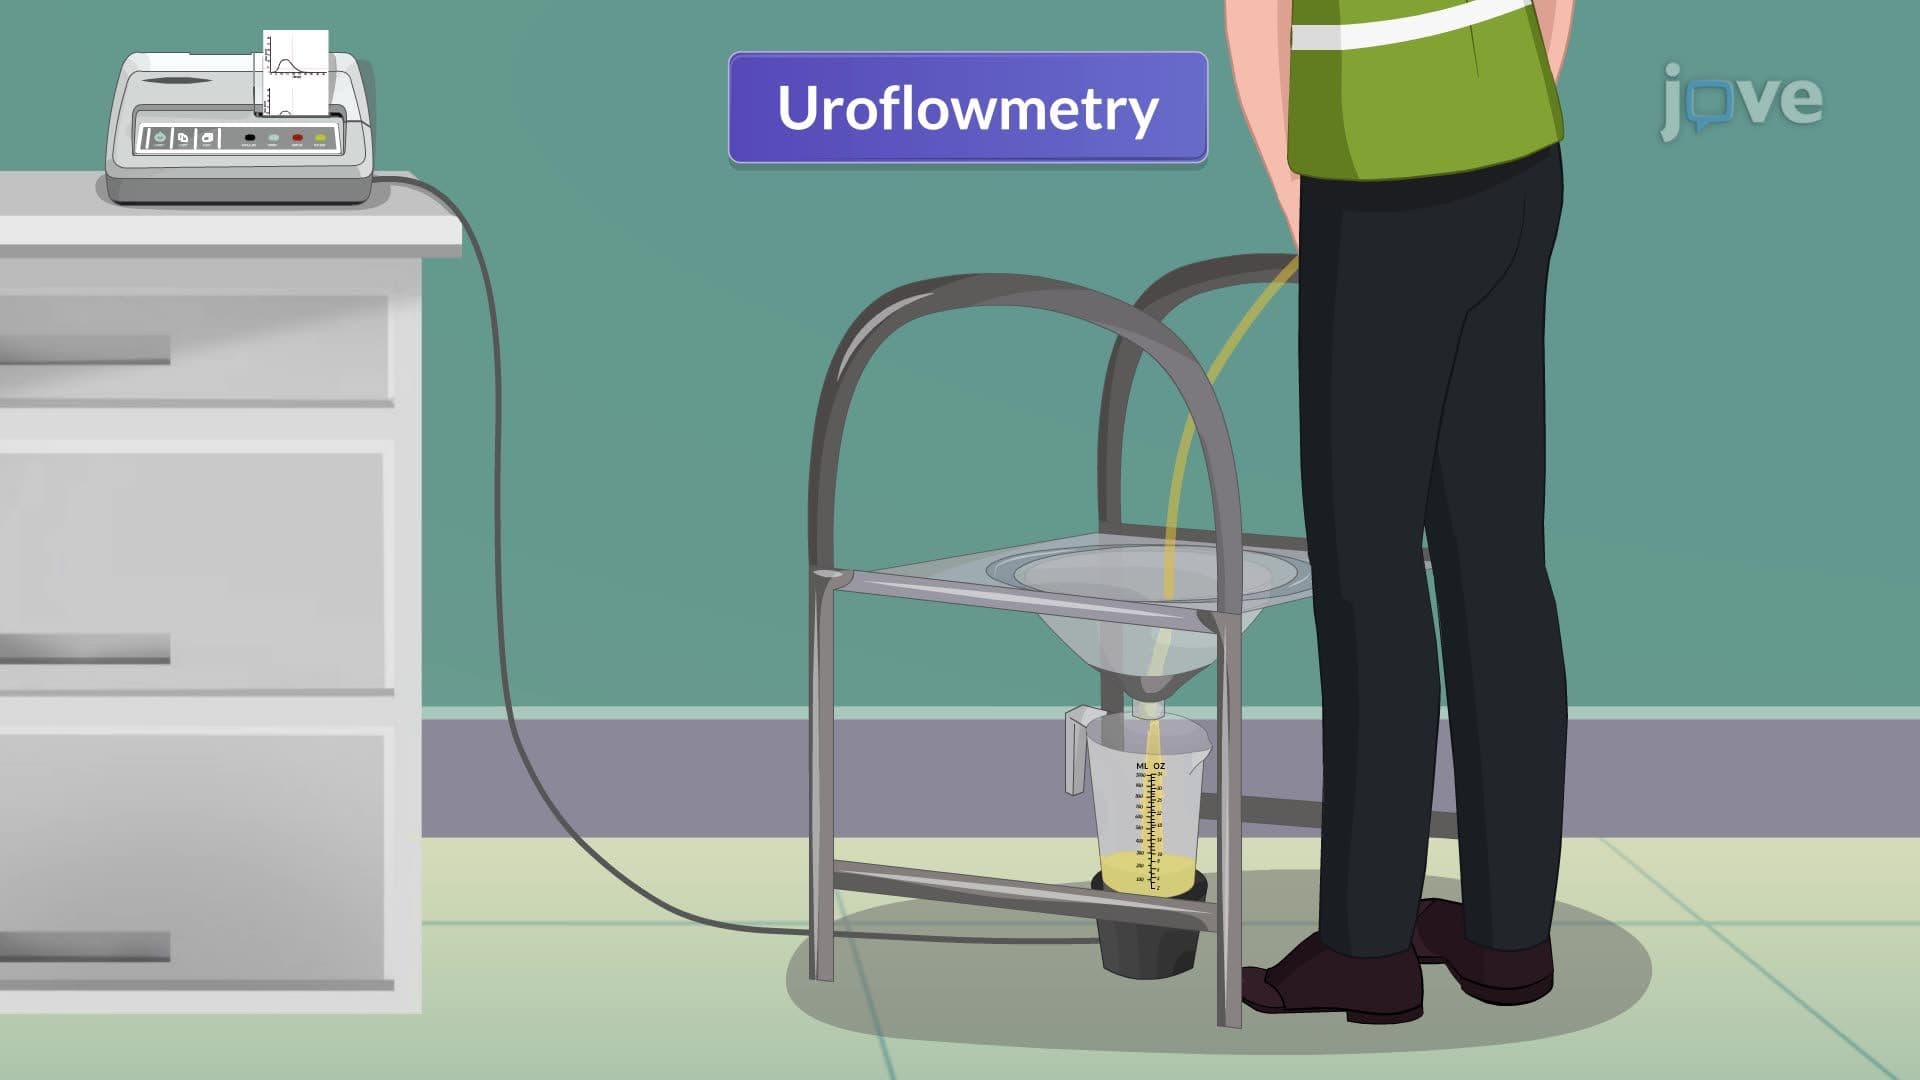
Urodynamic Studies: Uroflowmetry