Related Experiment Video
Updated: Oct 13, 2026
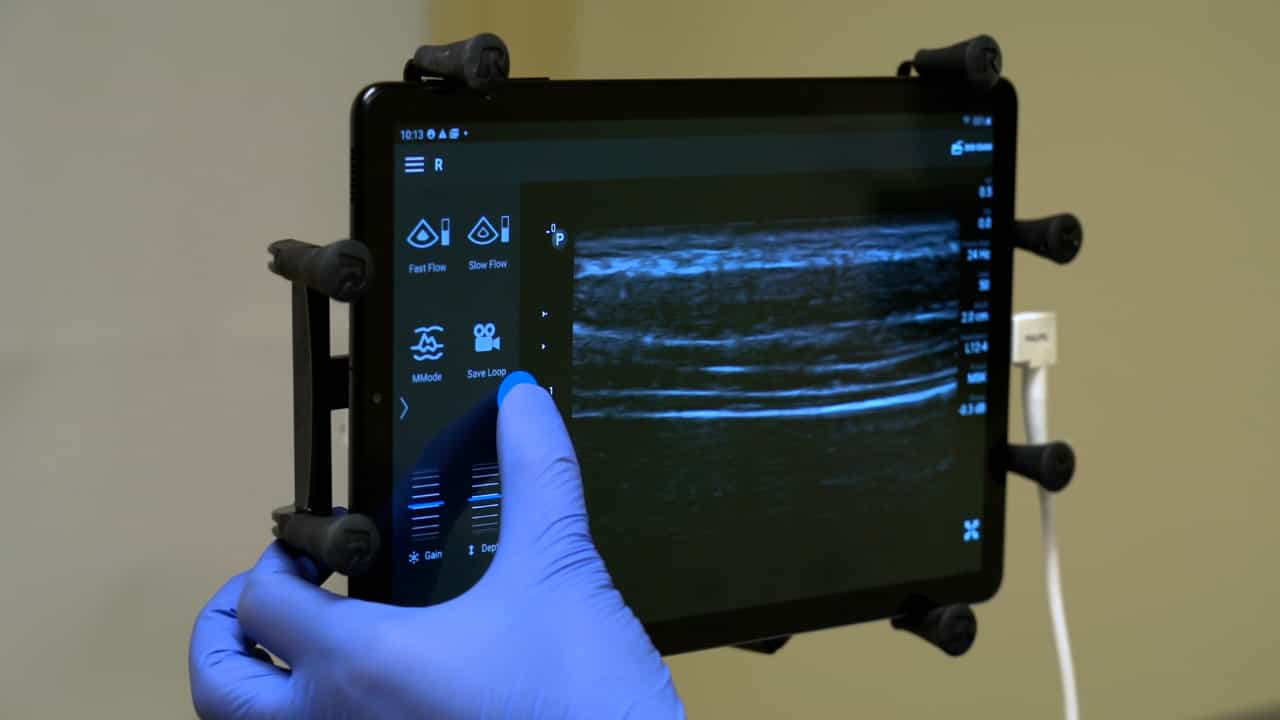
Measuring Diaphragm Thickness and Function Using Point-of-Care Ultrasound
Published on: November 3, 2023
Estimation of diaphragm length in patients with severe chronic obstructive pulmonary disease
D K McKenzie1, R B Gorman, J Tolman
1Department of Respiratory Medicine, Prince of Wales Hospital, Randwick, Sydney 2031, Australia. mckenzied@sesahs.nsw.gov.au

Abstract:
In patients with advanced chronic obstructive pulmonary disease (COPD) diaphragm function may be compromised because of reduced muscle fibre length. Diaphragm length (L(Di)) can be estimated from measurements of transverse diameter of the rib cage (D(Rc)) and the length of the zone of apposition (L(Zapp)) in healthy subjects, but this method has not been validated in patients with COPD. Postero-anterior chest radiographs were obtained at total lung capacity (TLC), functional residual capacity (FRC) and residual volume (RV) in nine male patients with severe COPD (mean [S.D.]; FEV(1), 23 [6] %pred.; FRC, 199 [15] %pred.). Radiographs taken at TLC were used to identify the lateral costal insertions of the diaphragm (L(Zapp) assumed to approach zero at TLC). L(Di) was measured directly and also estimated from measurements of L(Zapp) and D(Rc) using a prediction equation derived from healthy subjects. The estimation of L(Di) was highly accurate with an intraclass correlation coefficient of 0.93 and 95% CI of approximately +/-8% of the true value. L(Di) decreased from 426 (64) mm at RV to 305 (31) mm at TLC. As there were only small and variable changes in D(Rc) across the lung volume range, most of the L(Di) changes occurred in the zone of apposition. Additional studies showed that measurements of L(Di) from PA and lateral radiographs performed at different lung volumes were tightly correlated. These results suggest that non-invasive measurements of L(Zapp) in the coronal plane (e.g. using ultrasonography) and D(Rc) (e.g. using magnetometers) can be used to provide an accurate estimate of L(Di) in COPD patients.

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: