Related Experiment Video
Updated: Oct 13, 2026

A Rat Lung Transplantation Model of Warm Ischemia/Reperfusion Injury: Optimizations to Improve Outcomes
Published on: October 28, 2021
Lung allocation in the United States, 1995-1997: an analysis of equity and utility
R N Pierson1, A P Milstone, J E Loyd
1Cardiac and Thoracic Surgery, Vanderbilt University, Nashville, Tennessee, USA. robin.pierson@mcmail.vanderbilt.edu

Background:
Waiting time for organ transplantation varies widely between programs of different sizes and by geographic regions. The purpose of this study was to determine if the current lung-allocation policy is equitable for candidates waiting at various-sized centers, and to model how national allocation based solely on waiting time might affect patients and programs.
Methods:
UNOS provided data on candidate registrations; transplants and outcomes; waiting times; and deaths while waiting for all U.S. lung-transplant programs during 1995-1997. Transplant centers were categorized based on average yearly volume: small (< or = 10 pounds sterling transplants/year; n = 46), medium (11-30 transplants/year; n = 29), or large (>30 transplants/year; n = 6). This data was used to model national organ allocation based solely on accumulated waiting time for candidates listed at the end of 1997.
Results:
Median waiting time for patients transplanted was longest at large programs (724-848 days) compared to small and medium centers (371-552 days and 337-553 days, respectively) and increased at programs of all sizes during the study period. Wait-time-adjusted risk of death correlated inversely with program size (365 vs 261 vs 148 deaths per 1,000 patient-years-at-risk at small, medium, and large centers, respectively). Mortality as a percentage of new candidate registrations was similar for all program categories, ranging from 21 to 25%. Survival rates following transplantation were equivalent at medium-sized centers vs large centers (p = 0.50), but statistically lower when small centers were compared to either large- or medium-size centers (p < or = 0.05). Using waiting time as the primary criterion lung allocation would acutely shift 10 to 20% of lung-transplant activity from medium to large programs.
Conclusions:
1) Waiting list mortality rates are not higher at large lung-transplant programs with long average waiting times. 2) A lung-allocation algorithm based primarily on waiting-list seniority would probably disadvantage candidates at medium-size centers without improving overall lung-transplant outcomes. 3) If fairness is measured by equal distribution of opportunity and risk, we conclude that the current allocation system is relatively equitable for patients currently entering the lung-transplant system.

Related Concept Videos
 01:26
Respiratory Volumes and Capacities I
 01:47
Lung Capacity
 01:22
Respiratory Volumes and Capacities
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
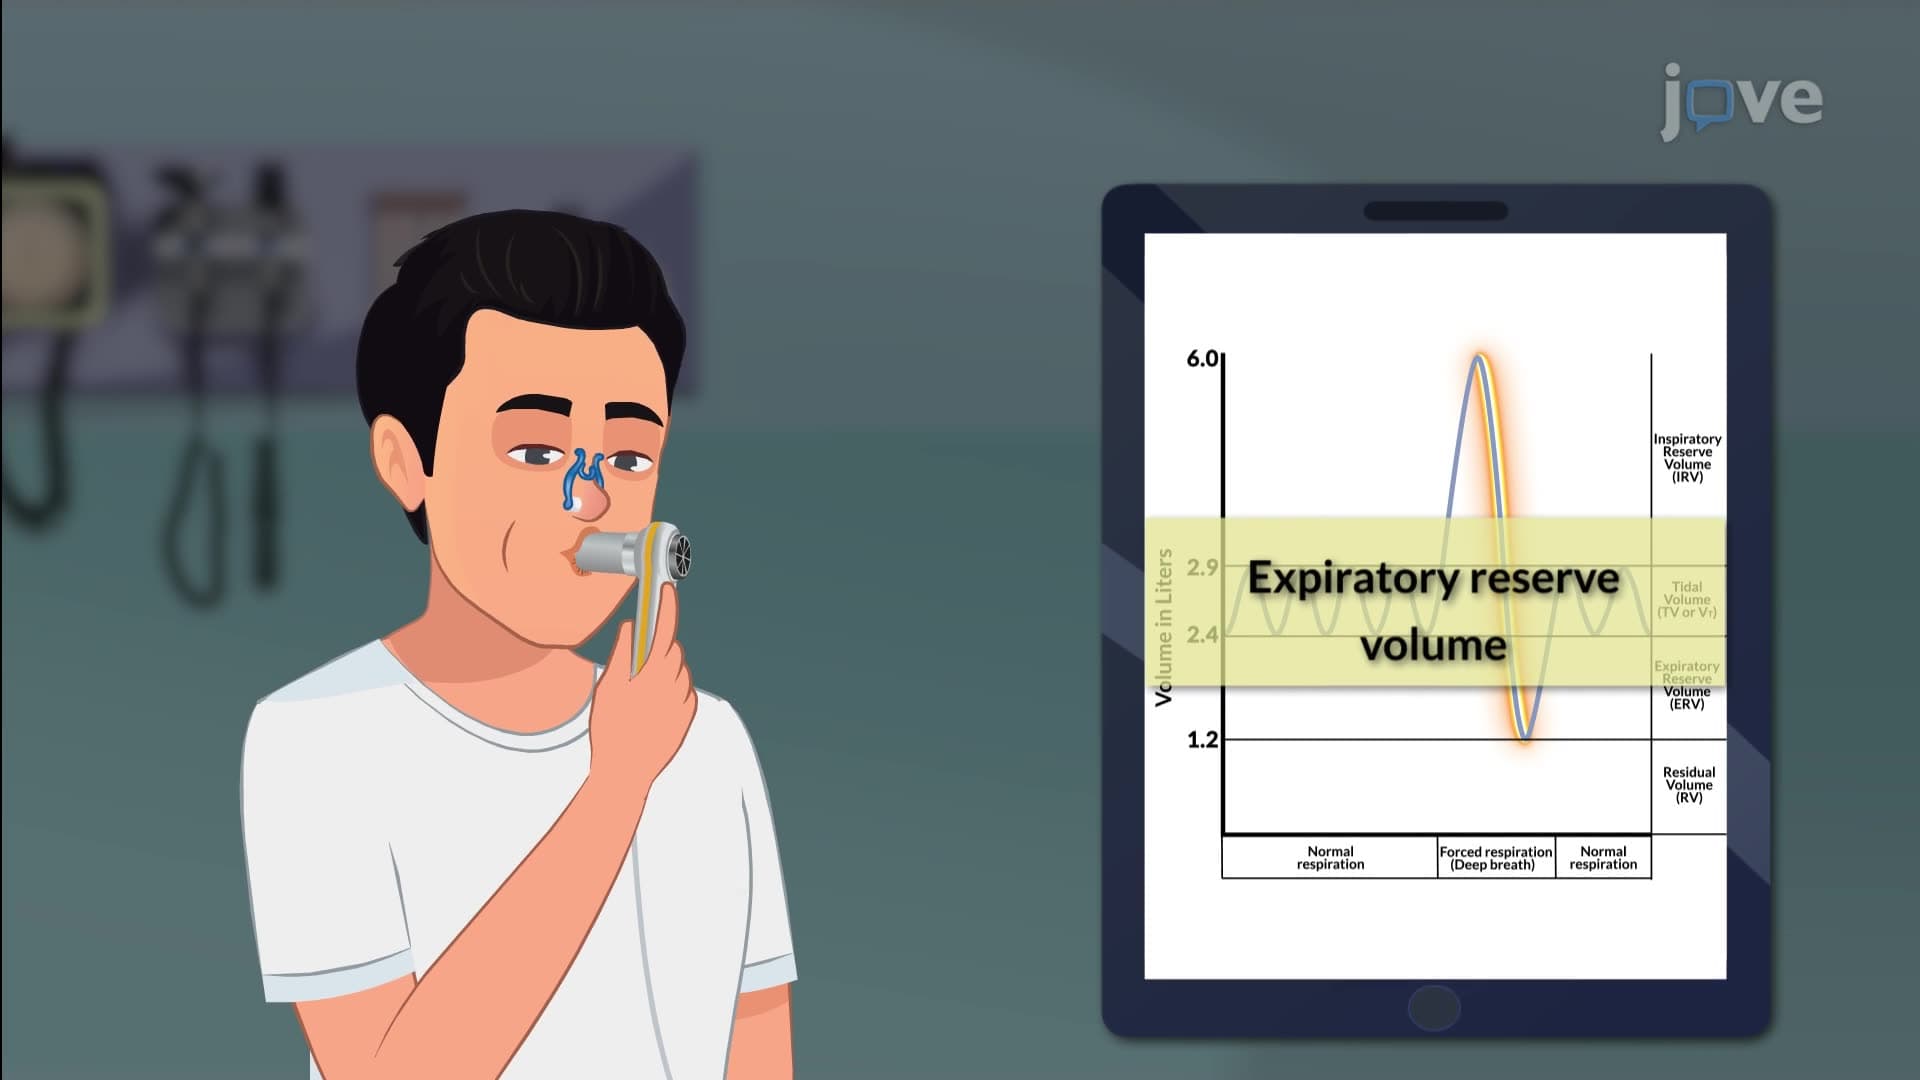 01:15
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...