Related Experiment Video
Updated: Aug 19, 2026
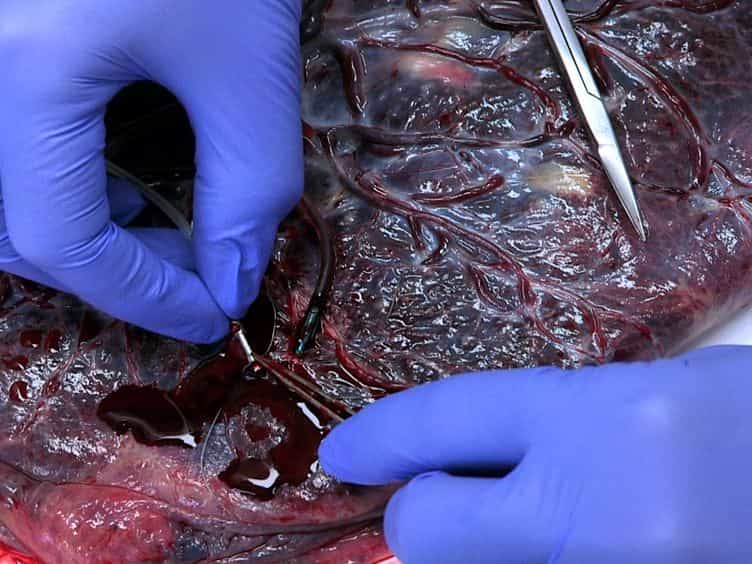

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Digoxin: placental transfer, effects on the fetus, and therapeutic use in the newborn

Digoxin rapidly crosses the placenta and reaches equilibrium, with maternal and fetal sera having equal concentrations. Virtually nothing is known about the effects of transplacentally administered digoxin on the fetus. Toxicity has been reported in the fetus of a woman ingesting a huge overdose of digitoxin; the same result would be anticipated with digoxin poisoning. Serum levels in pregnant women receiving the standard dose of 0.25 mg tend to be subnormal and certain patients may require a small increase in dose during the last trimester. While the full-term neonate appears to tolerate relatively high doses and the resultant high serum levels, there is no compelling evidence that such doses are necessary or even useful. Since toxicity can and does occur in neonates, especially during administration of loading (digitalizing) doses, it is recommended that maintenance doses of 0.01 mg per kg per day be used routinely. If the full inotropic effect is needed immediately, a loading dose of 0.03 mg per kg may be employed. Maintenance therapy is then begun on the following day. Without a loading dose cumulation occurs for about 3 days; after 5 or so days, serum levels will equal those found after use of a loading dose followed by maintenance therapy. Results of a single study suggest that the daily dose should be divided and given every 12 hours. After about 1 week of therapy, the serum level should be determined and the dose modified to maintain a serum level of 1 to 2 ng per ml. If the therapeutic effect is less than desired, a cautions increase in dose to as high as 0.02 mg per kg per day or to that dose which produces serum levels up to 3 ng per ml can be tried. Certain infants appear to tolerate serum levels of 3.5 to 4 ng per ml but such infants must be closely monitored. There are no data which indicate that a greater inotropic response will occur at these high serum levels, though this point has not been definitively investigated, and is the highest priority question for research. The intramuscular route should be researved for the unusual situation. Vomiting should be considered an early sign of toxicity and may act as a "safety valve." When adminstered in solution (as in the elixir or solution for intravenous use), oral digoxin is rapidly absorbed an an inotropic response is found within minutes, reaching a peak within hours, so that little is gained by parenteral administration. If an inotropic effect is urgently needed, intravenous administration of ouabain will give an immediate response.
Digoxin rapidly crosses the placenta and reaches equilibrium, with maternal and fetal sera having equal concentrations. Virtually nothing is known about the effects of transplacentally administered digoxin on the fetus. Toxicity has been reported in the fetus of a woman ingesting a huge overdose of digitoxin; the same result would be anticipated with digoxin poisoning. Serum levels in pregnant women receiving the standard dose of 0.25 mg tend to be subnormal and certain patients may require a small increase in dose during the last trimester. While the full-term neonate appears to tolerate relatively high doses and the resultant high serum levels, there is no compelling evidence that such doses are necessary or even useful. Since toxicity can and does occur in neonates, especially during administration of loading (digitalizing) doses, it is recommended that maintenance doses of 0.01 mg per kg per day be used routinely. If the full inotropic effect is needed immediately, a loading dose of 0.03 mg per kg may be employed. Maintenance therapy is then begun on the following day. Without a loading dose cumulation occurs for about 3 days; after 5 or so days, serum levels will equal those found after use of a loading dose followed by maintenance therapy. Results of a single study suggest that the daily dose should be divided and given every 12 hours. After about 1 week of therapy, the serum level should be determined and the dose modified to maintain a serum level of 1 to 2 ng per ml. If the therapeutic effect is less than desired, a cautions increase in dose to as high as 0.02 mg per kg per day or to that dose which produces serum levels up to 3 ng per ml can be tried. Certain infants appear to tolerate serum levels of 3.5 to 4 ng per ml but such infants must be closely monitored. There are no data which indicate that a greater inotropic response will occur at these high serum levels, though this point has not been definitively investigated, and is the highest priority question for research. The intramuscular route should be researved for the unusual situation. Vomiting should be considered an early sign of toxicity and may act as a "safety valve." When adminstered in solution (as in the elixir or solution for intravenous use), oral digoxin is rapidly absorbed an an inotropic response is found within minutes, reaching a peak within hours, so that little is gained by parenteral administration. If an inotropic effect is urgently needed, intravenous administration of ouabain will give an immediate response.

Related Concept Videos
 01:21
Factors Affecting Drug Response: Overview
 01:07
Teratogenicity
 01:26
Heart Failure Drugs: Inotropic Agents
 01:29
Drug Dosing: Infants and Children
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:21
Intrauterine Drug Delivery Systems