Related Experiment Video
Updated: Oct 11, 2026
Chronic Thromboembolic Pulmonary Hypertension and Assessment of Right Ventricular Function in the Piglet
Published on: November 4, 2015
Pathophysiology of impaired right and left ventricular function in chronic embolic pulmonary hypertension: changes
12nd Medical Clinic, Department of Cardiology, and Clinic for Cardiothoracic and Vascular Surgery, Johannes Gutenberg University, Langenbeckstrasse 1, D-55101 Mainz, Germany. menzel@mail.uni-mainz.de

Study Objectives:
This study sought to evaluate the pathophysiology of left and right heart failure in patients with chronic thromboembolic pulmonary hypertension (CTEPH) who were hospitalized to undergo pulmonary thromboendarterectomy (PTE).
Design:
Thirty-nine patients (16 women and 23 men; mean +/- SD age, 55+/-12 years) with severe CTEPH were examined before and 13+/-8 days after PTE by way of transthoracic echocardiography and right heart catheterization.
Measurements And Results:
Examination results confirmed in all cases that before surgery the right ventricles were enlarged and systolic function was impaired. Moderate to severe tricuspid valve regurgitation was observed. Left ventricular eccentricity indexes reflected a leftward displacement of the interventricular septum. End-diastolic left ventricular size and systolic function had decreased, and the left ventricular filling pattern showed impaired diastolic function. After surgery, mean pulmonary artery pressure was significantly lower (48+/- 10 mm Hg vs. 25+/-7 mm Hg; p<0.05). The calculated end-diastolic and end-systolic right ventricular areas had decreased: 30+/-7 cm(2) vs 21 +/-5 cm(2) (p<0.05) and 24+/-6 cm(2) vs. 14+/-4 cm(2) (p<0.05), respectively. Right ventricular fractional area change had increased (20+/-7% vs. 33+/-8%; p<0.05). Most of the patients exhibited a marked decrease in the severity of tricuspid regurgitation. Septal motion, left ventricular systolic function, and diastolic filling pattern returned to normal values (early to late diastolic left ventricular inflow ratio, 0.70+/-0.33 vs. 1.35+/-0.51; p<0.05). The mean cardiac index also improved (2.7+/-0.6 L/min/m(2) vs. 3.7+/-0.8 L/min/m(2)).
Conclusions:
In CTEPH, functions are impaired in the right as well as the left ventricles of the heart. Improved lung perfusion and the reduction of right ventricular pressure overload are direct results of PTE, which in turn bring a profound reduction of right ventricular size and a recovery of systolic function. Normalization of interventricular septal motion as well as improved venous return to the left atrium lead to a normalization of left ventricular diastolic and systolic function, and the cardiac index improves.
More Related Videos
 07:41
Induction and Phenotyping of Acute Right Heart Failure in a Large Animal Model of Chronic Thromboembolic Pulmonary Hypertension
Published on: March 17, 2022
 07:41
A Model of Reverse Vascular Remodeling in Pulmonary Hypertension Due to Left Heart Disease by Aortic Debanding in Rats
Published on: March 1, 2022
Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
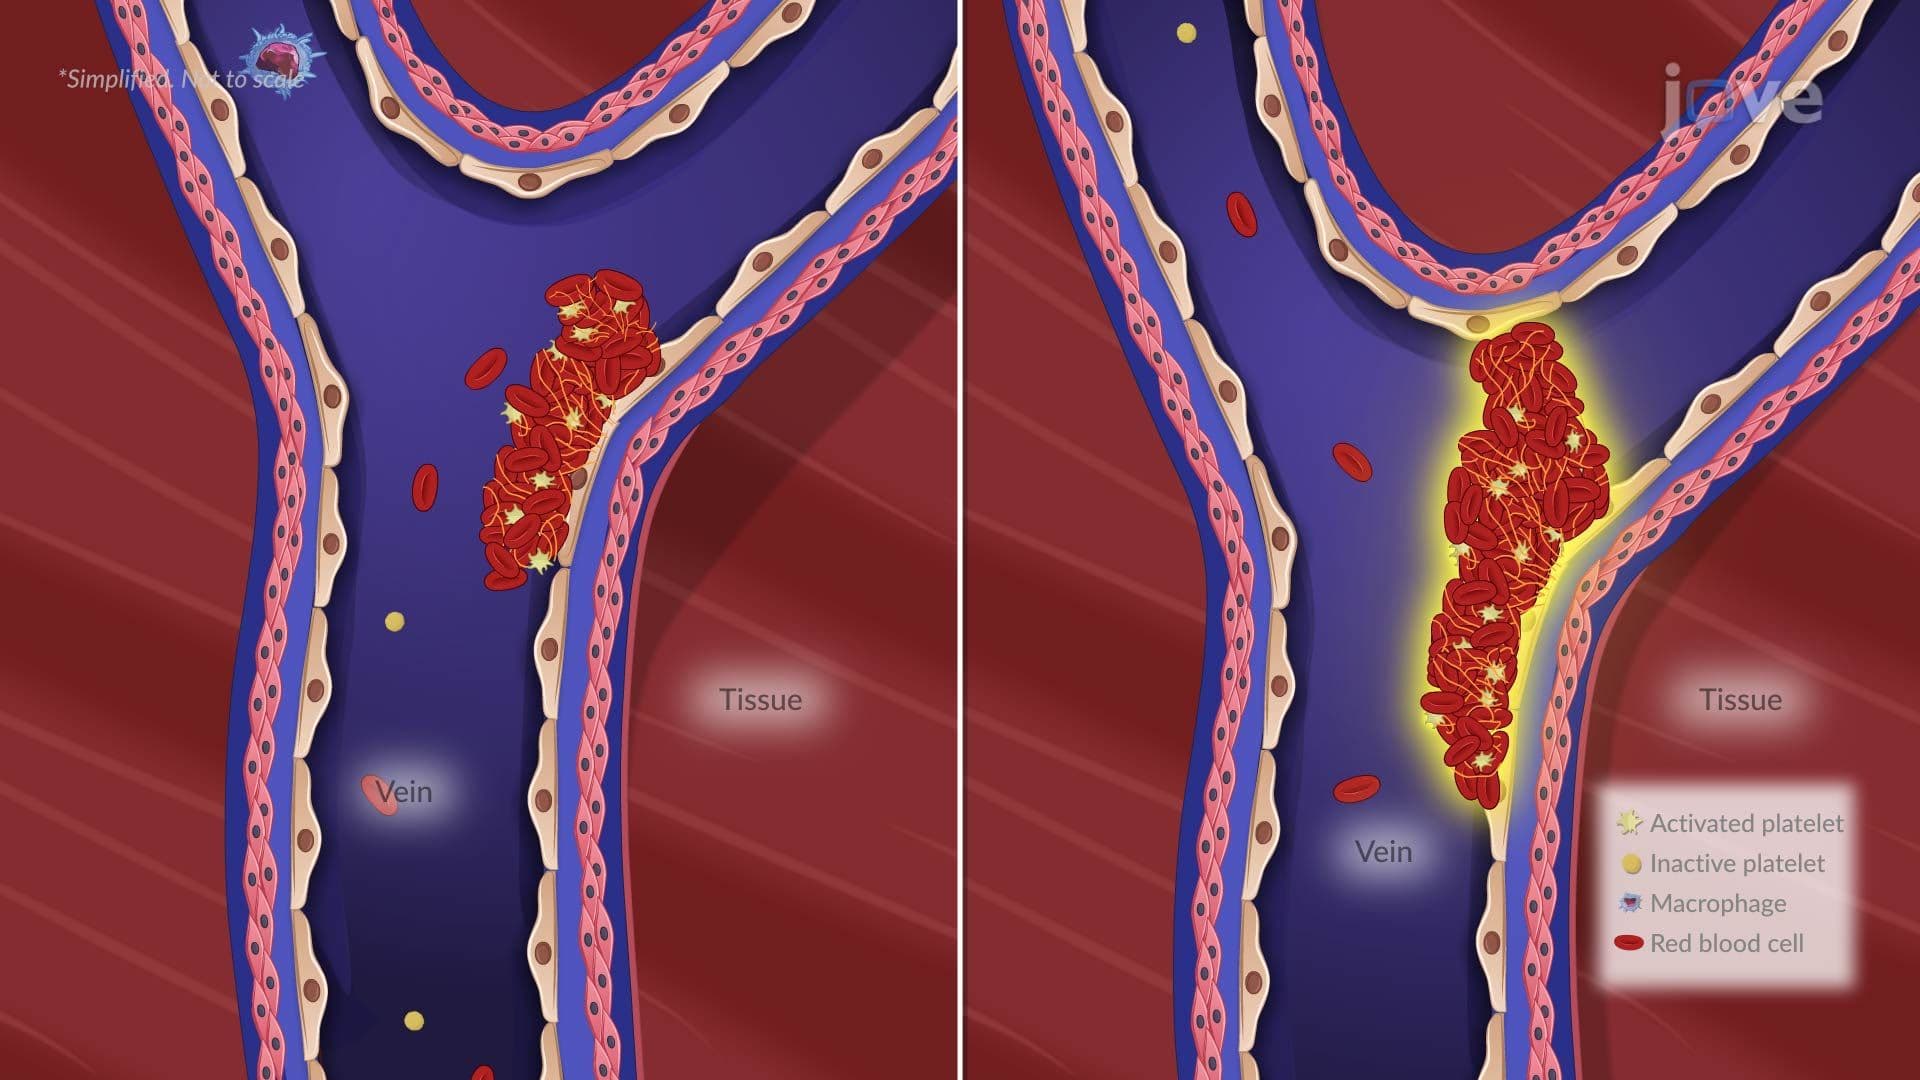
Pulmonary Embolism I: Introduction
 01:19
Pulmonary Embolism I: Introduction
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:22
Mitral Stenosis I: Introduction