[Gastroduodenal hemorrhage]
Related Experiment Video
Updated: Oct 11, 2026
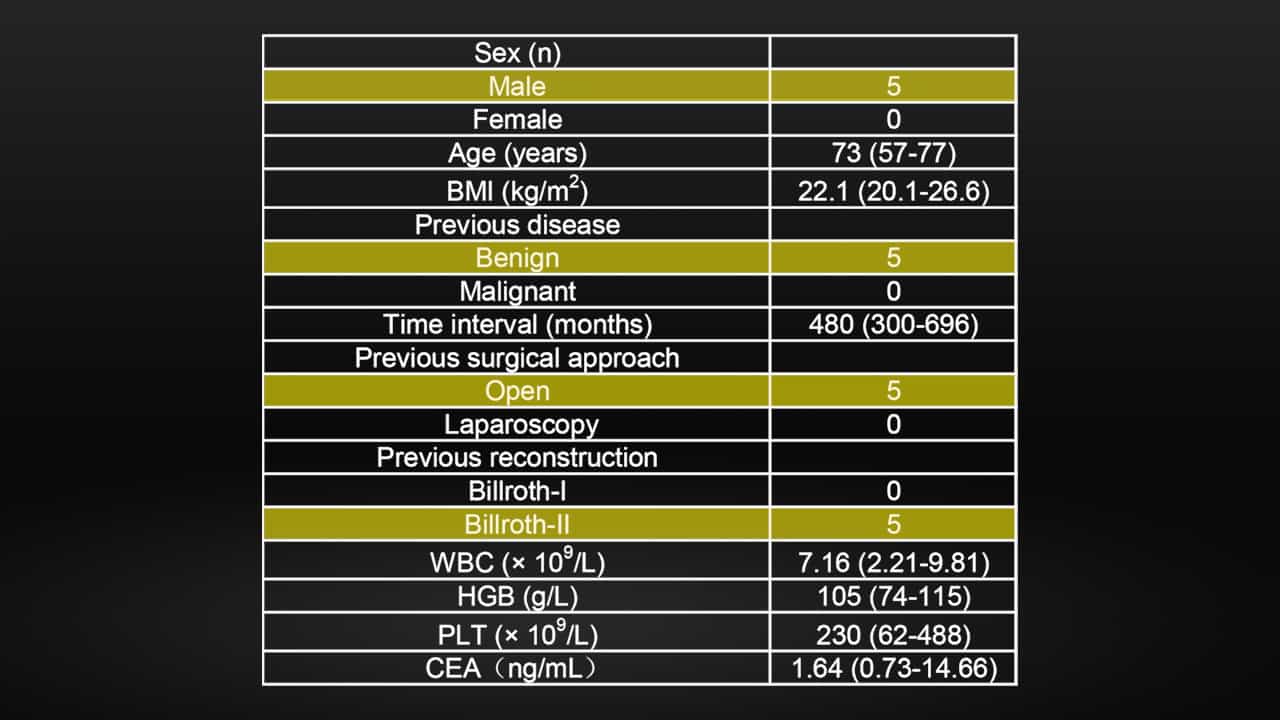
Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025

Insights
Urgent endoscopy is crucial for peptic ulcer bleeding, identifying gastric and duodenal ulcers. Endoscopic hemostasis is effective, but surgery is reserved for refractory or recurrent bleeding cases.
Area of Science:
- Gastroenterology
- Surgical Endoscopy
Context:
- Peptic ulcer disease frequently leads to serious hemorrhage.
- Urgent diagnostic and therapeutic endoscopy is the primary treatment modality.
Purpose:
- To evaluate the outcomes of urgent endoscopy for gastroduodenal peptic ulcer bleeding.
- To analyze patient demographics, ulcer types, bleeding severity, and treatment interventions.
Summary:
- A retrospective study of 291 patients (195 male, 96 female) with peptic ulcer bleeding undergoing urgent endoscopy.
- Gastric ulcers found in 34.7%, duodenal ulcers in 65.3%. Forrest classifications: I (23%), II (25.7%), III (51.3%).
- Endoscopic hemostasis applied in 12.37%; 82.9% experienced a first hemorrhage, 17.1% recurrent. Surgical intervention was required in 6.52% for uncontrolled or recurrent bleeding.
Impact:
- Highlights the efficacy of urgent endoscopy in managing peptic ulcer hemorrhage.
- Provides data on ulcer distribution and bleeding stigmata, guiding clinical decision-making.
- Underscores the role of endoscopic hemostasis and criteria for surgical referral.
Abstract:
Haemorrhage is a serious complication of peptic ulcer disease. It is an indication for urgent diagnostic and therapeutic endoscopy, which is at present the method of first choice. All patients with gastroduodenal peptic ulcer bleeding, who underwent endoscopy in Ist Department of Surgery in Bratislava between January 1995 and December 1999, were considered for retrospective study. A total of 291 patients (195 male and 96 female) underwent urgent endoscopy with a finding in 34.7% of patients with gastric ulcer and in 65.3% patients duodenal ulcer. The finding was Forrest I in 23%, Forrest II in 25.7% and Forrest III in 51.3% patients. Endoscopic hemostasis was used in 12.37% of patients. A first haemorrhage was found in 82.9% patients, a recurrent one in 17.1% patients. 41.5% of patients had positive peptic ulcer history. Surgical treatment was indicated in cases, when bleeding was not controlled by endoscopic means, or in cases of recurrent bleeding within 48 hours in 19 patients (6.52%).
Related Concept Videos
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:27
Peptic Ulcer
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: