Urinary prostaglandin excretion in pregnancy: the effect of dietary sodium restriction

F M Delemarre1, C M Thomas, R J van den Berg

  • 1Department of Obstetrics and Gynecology, University Medical Center Nijmegen, The Netherlands. f.delemarre@obgyn.azn.nl

Abstract

Related Concept Videos

Antihypertensive Drugs: Action of Diuretics01:16

Antihypertensive Drugs: Action of Diuretics
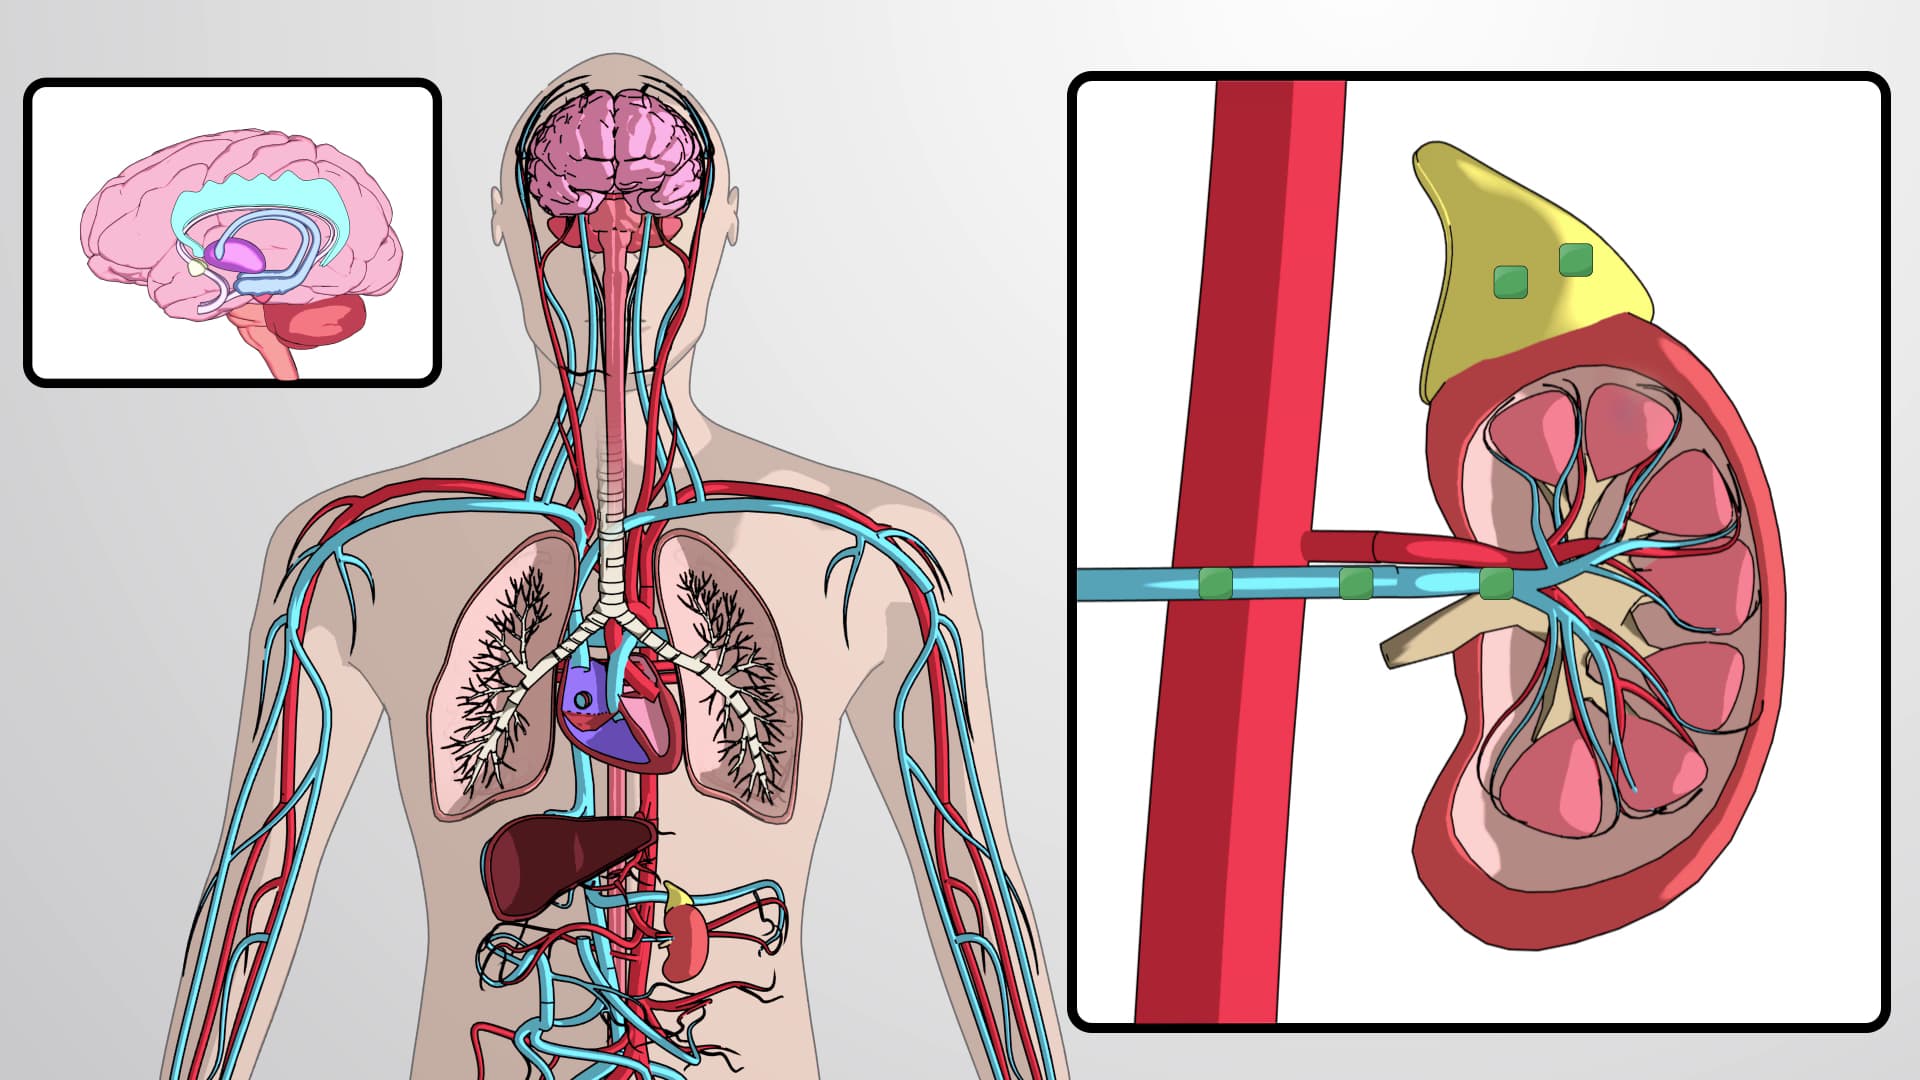
Diuretics are antihypertensive drugs used to treat hypertension resulting from sodium and water retention. Sodium, vital for fluid balance and nerve or muscle function, is regulated by the kidneys through millions of nephrons. Blood enters nephrons via afferent arterioles, which branch into capillaries called glomeruli. These filter blood plasma, allowing water and solutes, like sodium ions, to pass through capillary walls into Bowman's capsule. The filtrate then flows through various tubules...
Hormonal Regulation01:33

Hormonal Regulation

The renin-aldosterone system is an endocrine system which guides the renal absorption of water and electrolytes, thus managing blood pressure and osmoregulation. Activation of the system begins in the kidneys with a small cluster of cells adjacent to the afferent and efferent blood vessels of the renal corpuscle. As the nephrons are filtering blood, juxtaglomerular cells monitor blood pressure. If they detect a decrease in pressure, they release the hormone renin into the bloodstream.
Antihypertensive Drugs: Potassium-Sparing Diuretics01:28

Antihypertensive Drugs: Potassium-Sparing Diuretics

Liddle syndrome is a genetically inherited form of hypertension characterized by the overactivity of epithelial sodium channels in the nephron, the functional unit of the kidney. This heightened activity leads to increased sodium reabsorption and excessive excretion of potassium. To counteract this, potassium-sparing diuretics such as amiloride are used. They function by blocking these sodium channels, thereby reducing the influx of sodium into the epithelial cells and minimizing the loss of...
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents01:20

Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents

The gastric mucosa produces prostaglandins E2 (PGE2) and prostacyclin (PGI2), crucial in maintaining gastric health. They exert cytoprotective effects, including increasing bicarbonate secretion, releasing protective mucin, reducing gastric acid output, and preventing harmful vasoconstriction. These effects are mediated through various receptors, such as EP1, EP2, EP3, and EP4.
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
Nephrotic Syndrome II : Assessment and Medical Management01:26

Nephrotic Syndrome II : Assessment and Medical Management
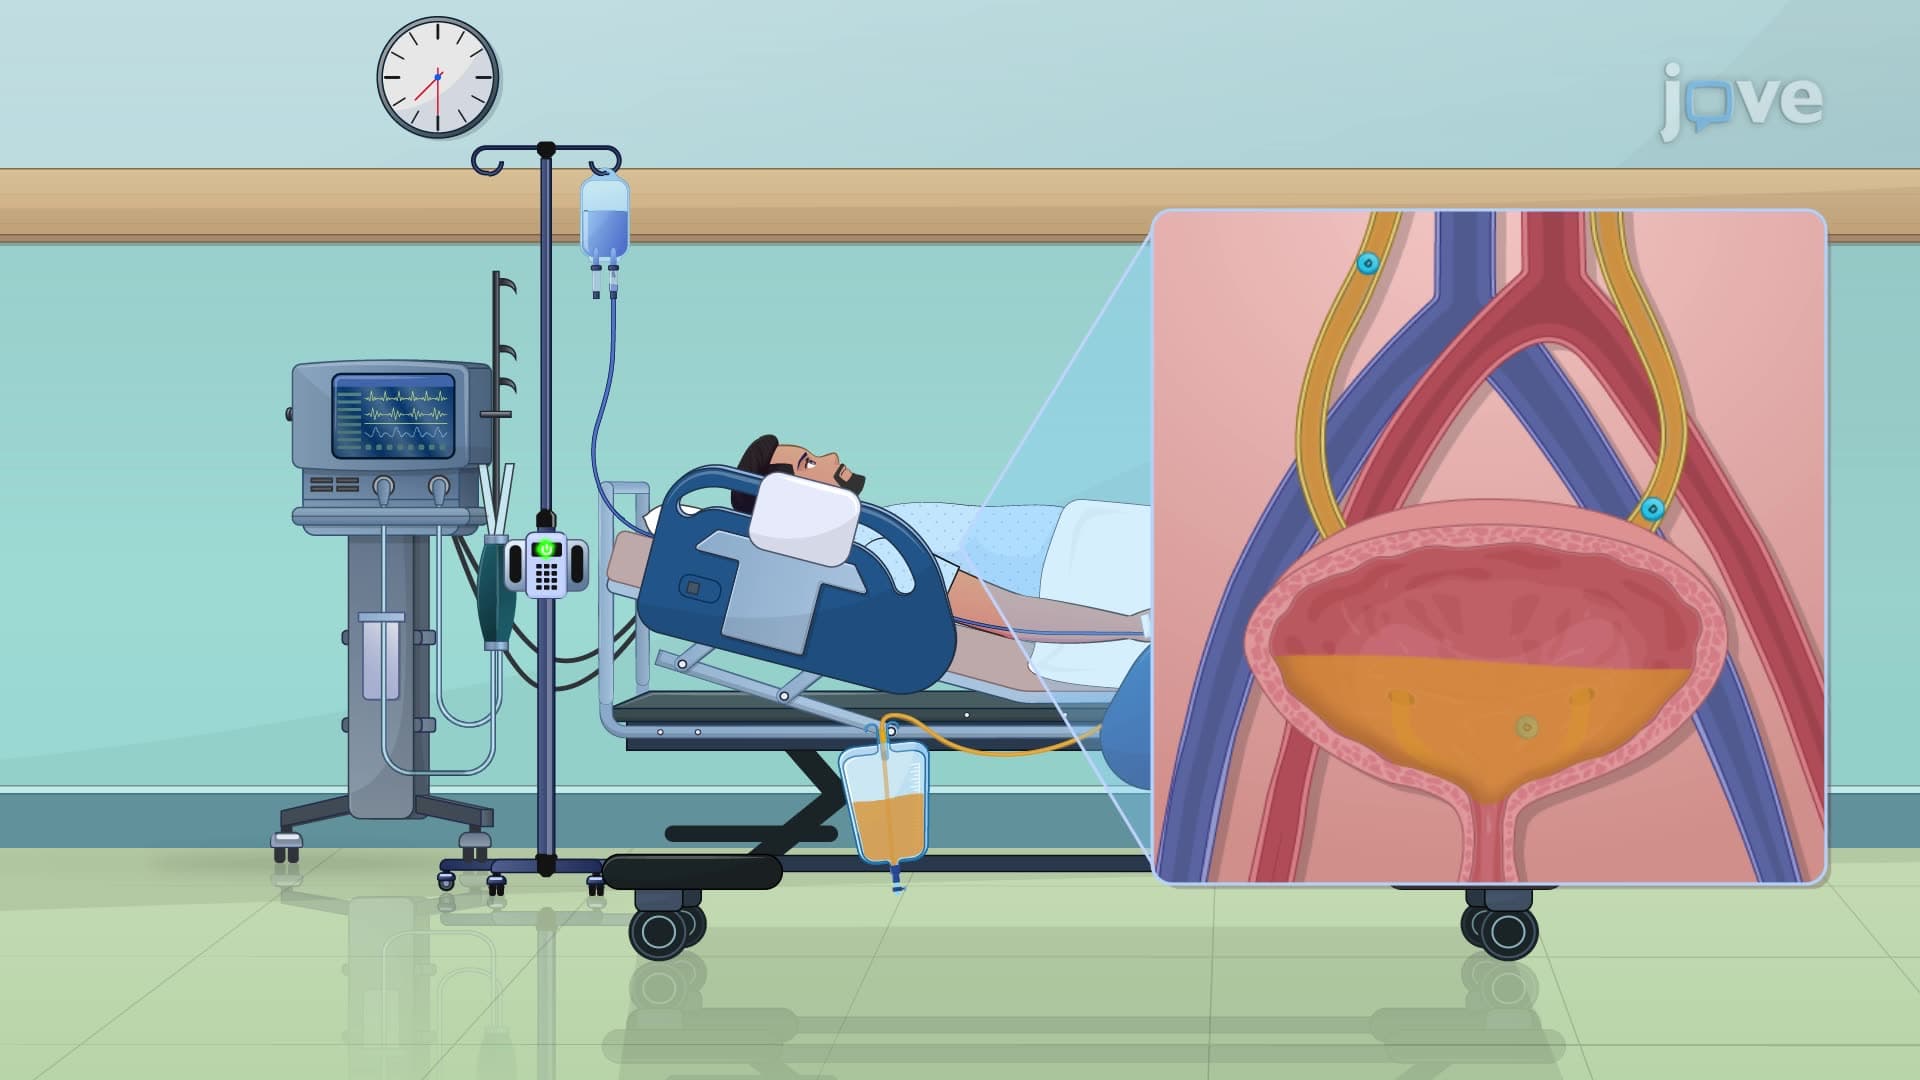
IntroductionNephrotic syndrome is a kidney disorder marked by excessive protein loss in the urine, leading to various systemic complications. This condition often results from damage to the glomeruli—the kidney's filtering units—causing proteinuria, low blood protein levels, and fluid retention. Understanding the assessment, diagnosis, and management of nephrotic syndrome is essential for effective treatment and prevention of further kidney damage.AssessmentPatient History: Document any history...
Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa01:22

Renal Drug Excretion: Effect of Urine pH, Flow Rate, and Drug pKa

The pH of urine, the drug's pKa, and the urine flow rate are vital parameters for drug reabsorption and excretion. Urinary pH varies between 4.6 and 8.0 and is influenced by diet, drug intake, and the patient's pathophysiology. It affects a drug's ionization state and reabsorption. For instance, carbohydrate-rich food produces alkaline urine promoting drug excretion, while proteins and certain medications like ascorbic acid lead to acidic urine enhancing reabsorption.
The pKa of a drug,...
