Acid-base correction and convective dialysis therapies
Related Experiment Videos
1Gambro Research, Lund, Sweden.

Abstract:
Whichever dialysis therapy is used, there is a similar need for correcting the acid base balance. The most important tool for this is the buffer in the dialysis fluid and, when using convective therapies, also in the substitution solution. The buffer source in all modern versions of these therapies should be bicarbonate. The more efficient the dialysis treatment in terms of small solute transport, the more rapid the uptake of buffer. Thus, optimally applied haemodiafiltration has the potential for the largest buffer gain. The target for acid-base correction in dialysis is to maintain patients within or as close to the physiological plasma bicarbonate range as possible. However, cross-sectional studies of acid base status among patients treated with contemporary forms of dialysis often show moderate acidosis. As metabolic acidosis has been found to be an important stimulus for protein catabolism in experimental studies, an association with nutritional problems has been sought in dialysis patients. This has revealed a negative correlation between plasma bicarbonate and nutritional parameters. Acidotic patients were found to have better nutritional status than patients with normalized acid-base balance. However, caution should be exercised when interpreting plasma bicarbonate levels, since acidosis may be a cause as well as an effect of excessive protein catabolism. Although available clinical data suggest that the catabolic effect of mild acidosis can be compensated by adequate nutrition and adequate dialysis, it should be desirable to aim for a normalized acid-base balance in combination with adequate nutritional intake and delivery of dialysis.
Related Concept Videos
 01:30
Continuous Renal Replacement Therapy
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:24
Hemodialysis II: Procedure and Complications
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:15
Dialysis
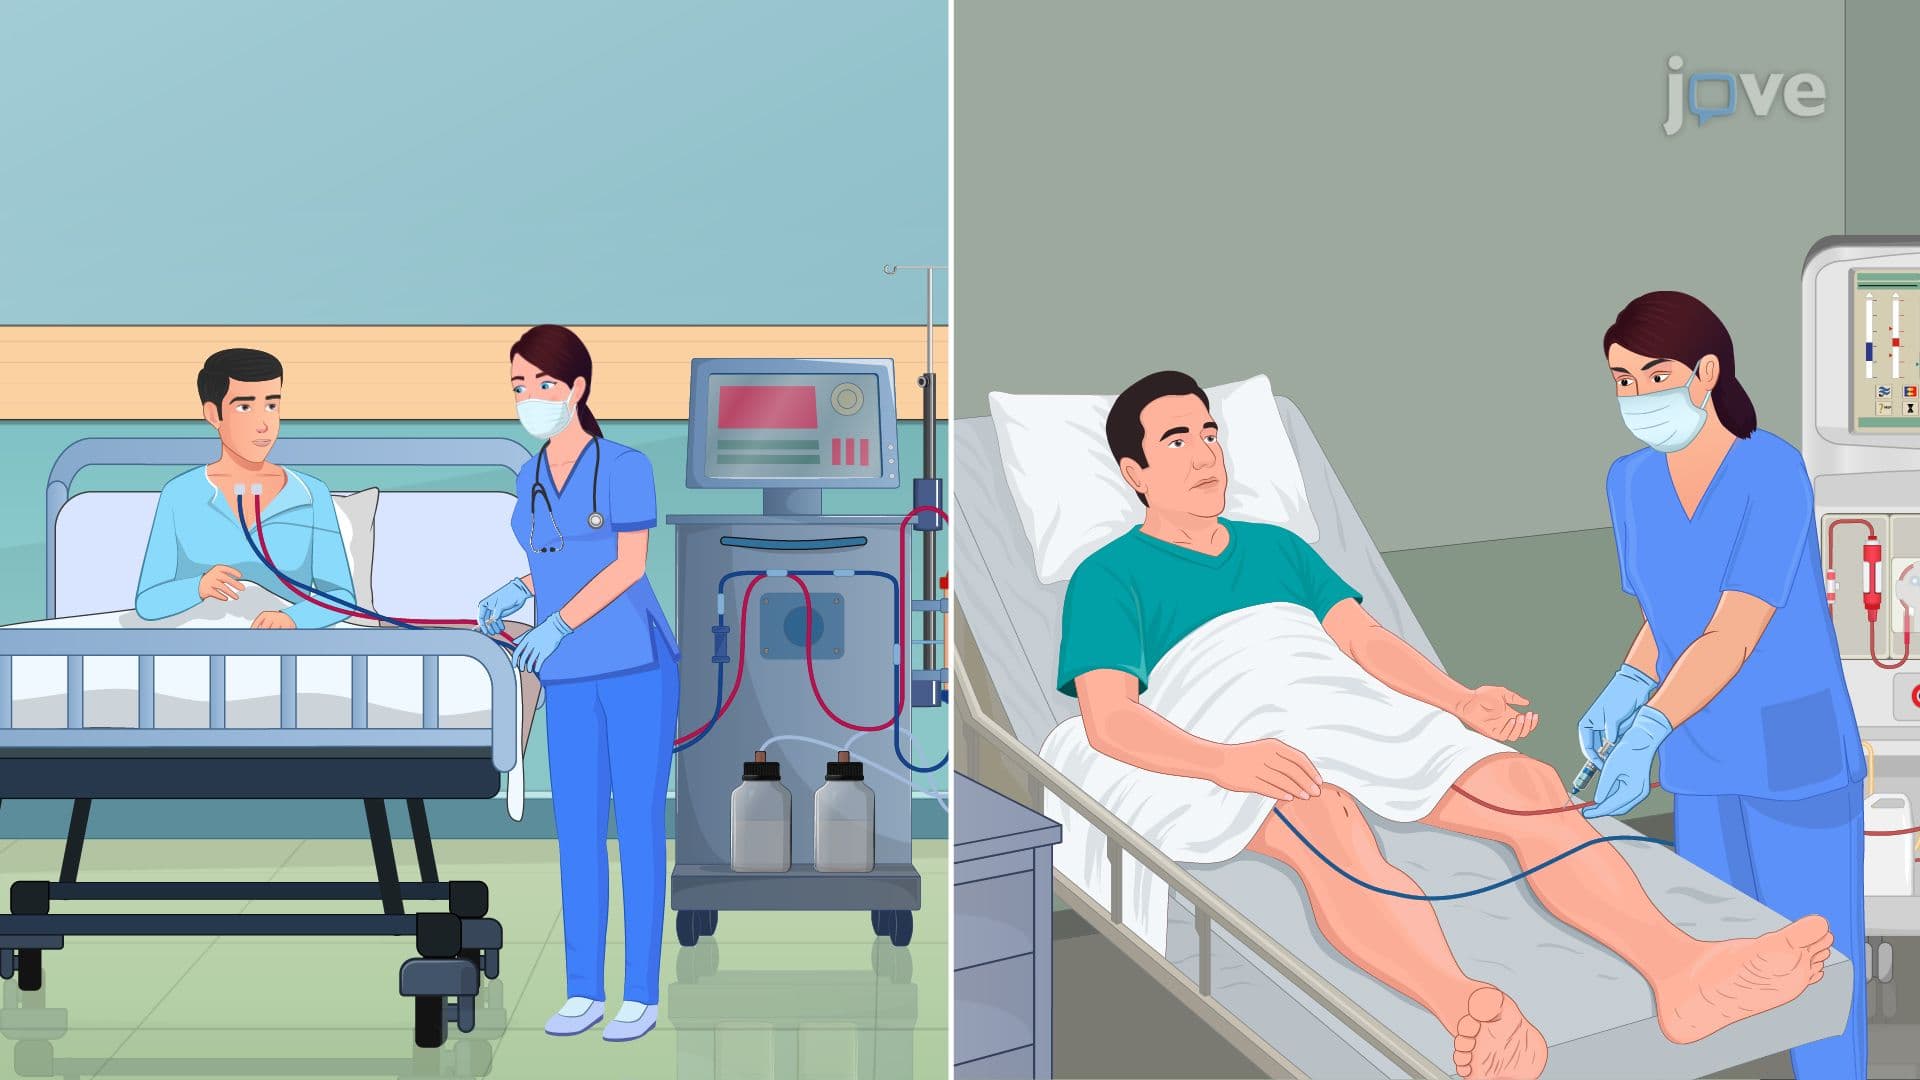 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy